Solution
ID: past-exam-of-the-medicine-course-of-the-university-of-oxford/1864/first-examination/anatomy-and-physiology/1/solution
Past exam of the medicine course of the University of Oxford 1864 First examination Anatomy and physiology 1 Solution by  Codex 0 2026-10-31
The thorax is a mobile osteocartilaginous enclosure with two pleural compartments and a central mediastinum; its visceral boundaries change normally with breathing and posture. The sketch is an anterior projection, with the subject's right on the viewer's left. It distinguishes the lower margin of a lung from the lower reflection of its pleura: those are different boundaries.
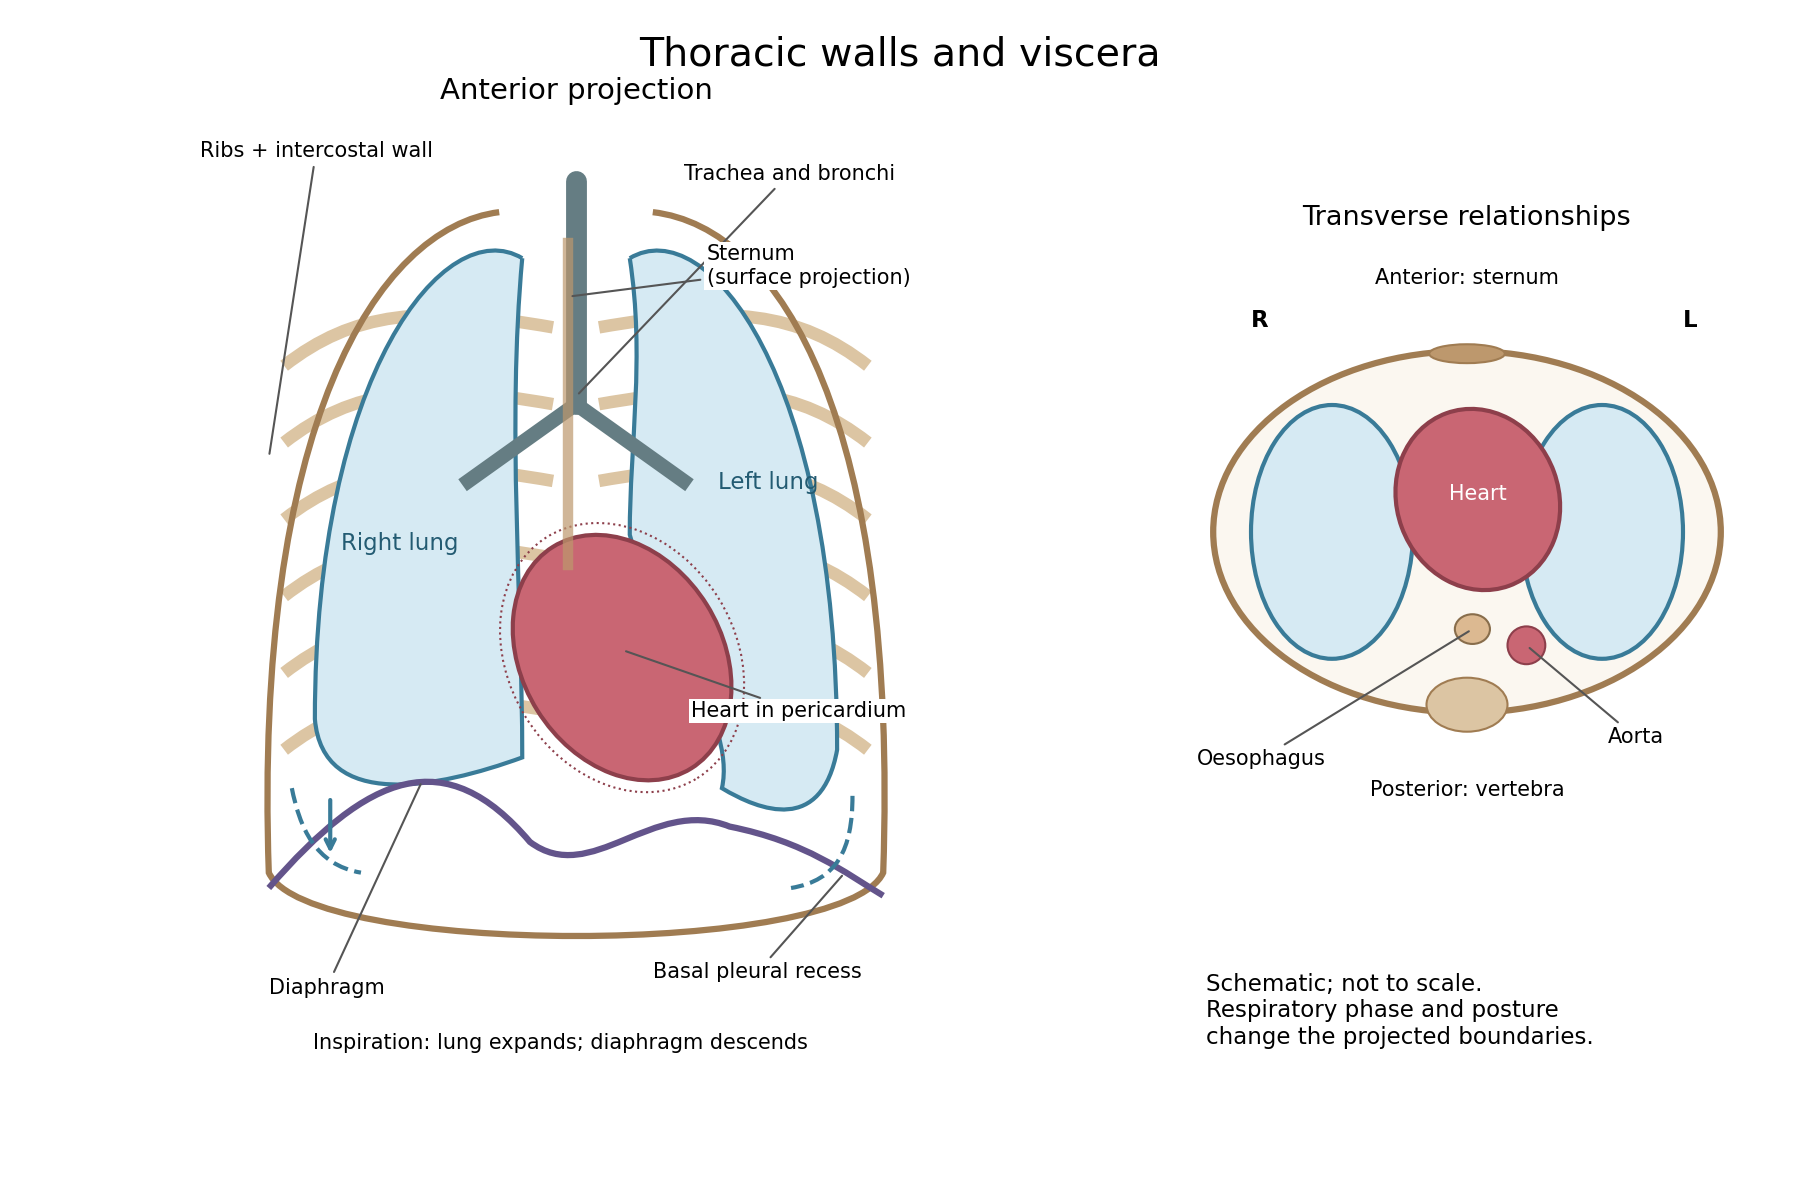

The posterior wall is formed by the twelve thoracic vertebrae and adjacent parts of the ribs; laterally the ribs and intercostal muscles form a flexible wall. Anteriorly lie the sternum, costal cartilages and anterior intercostal structures. The superior aperture communicates with the neck, while the respiratory diaphragm closes the inferior aperture. The lower thoracic wall therefore overlaps upper abdominal organs: not every organ under a lower rib is inside the pleural compartment.
Each lung is covered by visceral pleura. Parietal pleura lines the chest wall, upper surface of the respiratory diaphragm and side of the mediastinum, becoming continuous with visceral pleura at the root. The potential pleural space contains a lubricating fluid film; it is not normally an air-filled gap. The right lung has three lobes, the left two, with the cardiac notch and lingula accommodating the leftward projection of the heart. Each apex projects above the first rib into the root of the neck. The roots carry the bronchi, pulmonary vessels, nerves and lymphatic connections.[ref]
The heart and pericardium occupy chiefly the middle part of the inferior mediastinum, behind the sternum and between the lungs, with most of the cardiac bulk to the left of the median plane. The great vessels approach superiorly. The trachea divides into main bronchi behind the upper central region; the oesophagus descends behind the airway and heart. The descending thoracic aorta lies posteriorly, chiefly left of the vertebral bodies; the azygos venous route lies chiefly on the right. The thoracic duct and sympathetic chains belong to the posterior relations. A frontal projection superposes these structures and must not be mistaken for their order from front to back.
For a conventional quiet-breathing surface description, the lower lung border reaches approximately the sixth rib in the midclavicular line, eighth in the midaxillary line and tenth posteriorly near the scapular line. The pleural reflection descends approximately two ribs farther at corresponding landmarks: eighth, tenth and twelfth. These are orientation points, not immutable lines in every healthy individual. Inferiorly, the extra pleural extent forms the costodiaphragmatic recess. The right diaphragmatic dome usually stands higher, related to the underlying liver; the left is related to the stomach and other abdominal viscera.
In inspiration the respiratory diaphragm descends, the rib cage expands and lower lung margins move into the recesses; in expiration they retreat. The heart also shifts with the diaphragm and changes its surface projection as neighbouring lung expands. Deep inspiration, quiet expiration and forced expiration therefore cannot share a single normal map. The heart's own beat adds smaller cyclic movements.
Posture shifts the diaphragm and mediastinal contents: a supine position generally raises the domes compared with standing, while lateral positioning displaces mobile contents towards the dependent side. Body build, age, abdominal fullness and pregnancy change the available thoracic shape and diaphragmatic level. A distended stomach can raise the left dome and alter the cardiac projection without implying primary cardiac disease. The clinically useful comparison records posture and respiratory phase before judging an apparent difference in organ position.
New to topics? Read the docs here!