The left atrium is the heart chamber receiving blood through the pulmonary veins and delivering it through the mitral valve to the left ventricle. It is the receiving chamber on the oxygenated return side of the pulmonary circulation.[ref]
Its role changes during the cardiac cycle. The chamber can accumulate incoming blood while its outlet is closed, pass blood onward during ventricular filling, and contribute to late filling through atrial contraction. The storage role is called atrial reservoir function.[ref]
Anatomy and Physiology 2e by J. Gordon Betts and others. §19.1, Left Atrium
A volume balance makes this more precise:Here the sum includes the incoming pulmonary vein blood flow rates, and the outlet term is signed net flow through the mitral valve. In a constructed interval with total inflow L/min and zero outlet flow for s, the stored volume increases byThe example describes transient storage, not an indefinitely sustained steady state. Over a repeating cycle with no net accumulation, average inflow must equal average outflow.
The entering streams can also differ in oxygen content. Their mixed content is weighted by their blood flow rates, not by the number of vessels. Thus the same anatomical chamber supports two distinct balance questions: how its volume changes with time, and how transported oxygen combines. Its volume alone determines neither the stroke volume of the left ventricle nor the oxygen content entering the left ventricle.
Atrial flow component analysis classifies blood transport through an atrium by the entry, exit and retention histories of represented fluid parcels. It asks a different question from measuring only maximum and minimum left atrium volumes: which blood passed onward, remained within the chamber, or crossed a boundary in another direction?
A primary study used time-resolved computed tomography to reconstruct moving atrial anatomy, computational fluid dynamics to estimate the flow field, and modeled particle trajectories to classify six components. It distinguished atrial conduit flow component, atrial reservoir flow component, atrial delayed-ejection flow component, atrial retained-inflow component, atrial residual-volume component and pulmonary-vein backflow component.[ref]
Comprehensive left atrial flow component analysis reveals abnormal flow patterns in paroxysmal atrial fibrillation by Sophia Bäck and others. Abstract; Methods, flow-component definitions
These are model-derived transport categories, not six separate anatomical chambers.A typical trajectory calculation followswhere is the modeled fluid velocity. Boundary crossings and their timing within a defined cardiac cycle determine the category. For example, the study's conduit definition requires entry and exit within the same ventricular diastolic phase.[ref]
Comprehensive left atrial flow component analysis reveals abnormal flow patterns in paroxysmal atrial fibrillation by Sophia Bäck and others. Abstract and component definitions
Changing the time window or category definition changes what is counted.An original weighting example shows why counting markers alone can be misleading. Suppose three modeled markers represent 1, 1 and 8 mL, with the first two assigned to one component. That component contains 2 of 10 mL, or , although it contains two-thirds of the markers. The relevant fraction iswith the represented volumes for the chosen analysis. The denominator must be stated; an analysis that includes entering flow is not automatically a partition of one instantaneous chamber volume.
The results depend on reconstructed boundaries, flow assumptions, numerical tracking and phase definitions. Atrial reservoir function and atrial conduit function can be investigated with these categories, but a volumetric proxy and a parcel-based component need not be identical observations.
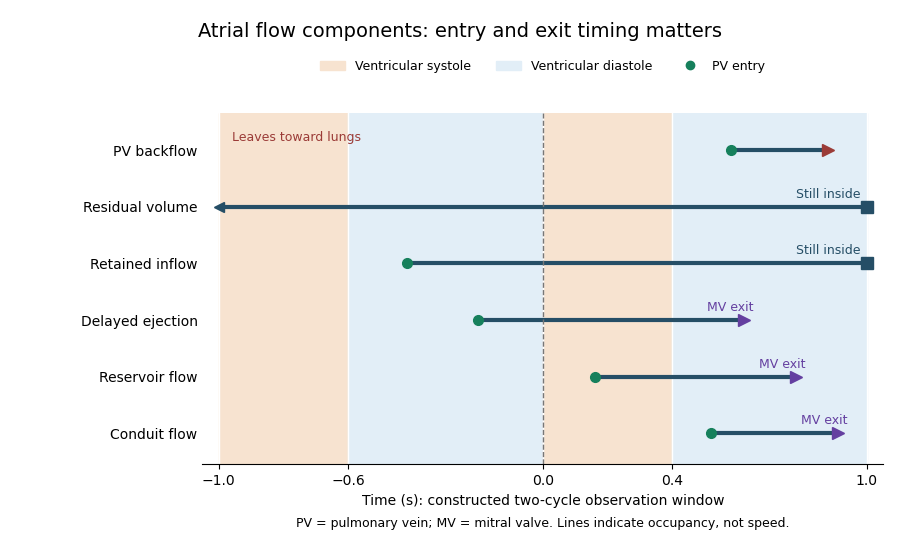
The pulmonary-vein backflow component comprises represented blood that leaves the left atrium through a pulmonary vein, toward the lungs. In atrial flow component analysis, the exit boundary distinguishes it from blood delivered through the mitral valve. The Bäck study includes both newly entering blood that returns to a pulmonary vein and previously resident atrial blood taking that exit.[ref]
An original signed-flow example explains why forward and backward transport should be recorded separately. Orient a pulmonary vein's boundary normal toward the left atrium, so positive volumetric flow rate denotes inflow. Define gross entering and leaving volumes over an observation interval byThe net transferred volume is . Constructed values mL and mL give 55 mL net inflow. Reporting only that net value hides the 5 mL reversal. Summing over all pulmonary veins gives a chamber-level boundary balance.
A boundary integral and a parcel history nevertheless answer different questions. If the same represented parcel crosses outward twice after re-entering, a gross boundary integral counts both crossings. A pathline-based component needs an explicit rule for repeated crossings and its observation window before its volume can be equated with that integral. Similarly, this route is not mitral regurgitation: the latter concerns reverse transport across the mitral valve, a different boundary. An outlet direction alone does not establish a diagnosis or the age of the blood taking that route.
The atrial residual-volume component is the represented blood remaining within the left atrium throughout the two tracked cardiac cycles in the Bäck atrial flow component analysis. It differs from the atrial retained-inflow component, for which an entry during the tracked history is identified.[ref]
The observation window is essential. Write for the moving atrial cavity and for a represented parcel's pathline. A mathematical statement of uninterrupted retention over isIf each qualifying marker represents volume , the component volume is . In a constructed example, 250 qualifying markers representing mL each give 2 mL. This is a weighted volume, not a count of anatomical pockets.
The classification supplies a lower bound on observed uninterrupted residence time, rather than an exact entry date. For a hypothetical two-cycle window lasting 1.6 s, a parcel present throughout has spent at least 1.6 s continuously inside by the window's end; it might have entered much earlier. Extending the window can reveal an entry or exit that a shorter window missed. In an ideal trajectory record, the set remaining throughout a longer interval is a subset of the set remaining throughout any contained shorter interval.
Retention also does not require zero velocity. A circulating parcel can remain inside the cavity while moving rapidly around a closed region. Conversely, briefly slow blood can later leave. The atrial residual-volume component, local velocity and residence time are therefore related transport descriptors with different definitions.
The atrial retained-inflow component is blood that entered the left atrium during the previous cardiac cycle but has not left by the specified endpoint of the Bäck tracking scheme. Its documented entry distinguishes it from the atrial residual-volume component, whose blood remains throughout both tracked cycles.[ref]
A simple parcel ledger makes the distinction concrete. In a constructed one-second cardiac cycle, let a tracked parcel enter through a pulmonary vein at s during the first of two cycles and remain inside until observation ends at s. Its observed residence time at that endpoint is 1.6 s. If that parcel crosses the mitral valve at s, a later observation reveals an exit; the earlier record was still correctly classified for its own endpoint.
Different amounts of retention need not produce different instantaneous chamber volumes. Consider two ideal histories, each with 40 mL inside the left atrium at the endpoint. In the first, 10 mL has an observed entry during the designated earlier cycle and remains, while 30 mL was present throughout the entire tracking window. In the second, the corresponding volumes are 25 and 15 mL. Both chamber totals are 40 mL, but their atrial retained-inflow component and atrial residual-volume component differ. A chamber outline alone cannot distinguish these histories.
The component is consequently useful for asking about replacement of atrial blood, alongside atrial delayed-ejection flow component and atrial conduit flow component. Its measured or modeled fraction must identify both the tracking interval and denominator. Dividing 10 mL by a 40 mL chamber volume gives ; dividing it by a stipulated 80 mL cycle throughput gives . Those percentages express different comparisons.
The atrial delayed-ejection flow component comprises blood leaving the left atrium during ventricular diastole after entering during the preceding diastole or earlier. The Bäck study calls this delayed outflow. In contrast, the atrial reservoir flow component enters during the intervening ventricular systole.[ref]
This is a transport-history definition, not a statement that ventricular electrical activation was delayed. A constructed timeline illustrates it. Number successive one-second cardiac cycles so the current ventricular systole occupies s and its following diastole occupies s. Suppose a parcel entered in the previous diastole at s and crosses the mitral valve at s. Its 0.8 s passage spans a ventricular systole. A second parcel entering at s and leaving at s instead belongs to the atrial conduit flow component.
For represented parcels with exit times , entry times and volume weights , a volume-weighted transit time within a selected exiting category isTwo hypothetical parcels representing 1 and 3 mL and taking 0.8 and 1.2 s give s, rather than the unweighted mean of 1 s. If an entry occurred before the available record, the exact transit time is unknown: an observed exit can establish a category without recovering an exact entry date.
The atrial delayed-ejection flow component thus complements the atrial retained-inflow component: one identifies an observed exit of older atrial blood, while the other identifies entered blood still present at the specified endpoint.
The atrial reservoir flow component is blood entering the left atrium during ventricular systole and leaving through the mitral valve in the following ventricular diastole. This parcel-based category in atrial flow component analysis specifies both arrival and departure phases.[ref]
Its definition explains the storage interpretation of atrial reservoir function. In an idealized closed-outlet interval, the left atrium's volume balance iswhere is total net inflow from the pulmonary veins. A stipulated constant 50 mL/s for 0.3 s increases atrial volume by 15 mL. This balance describes storage during that interval. To label all 15 mL as atrial reservoir flow component, a parcel record must additionally show the prescribed subsequent exit.
For example, imagine that the stored 15 mL comprises 12 mL that leaves in the following ventricular diastole and 3 mL that remains beyond it. The volume increase is still 15 mL, but the qualifying atrial reservoir flow component from those arrivals is 12 mL. Conversely, older blood can leave during the same filling phase without having entered during the immediately preceding ventricular systole.
A maximum-minus-minimum atrial volume is therefore not an automatic census of this category. Chamber volume measures how much is inside at a given time; pathlines identify which represented blood is inside and where it goes. The primary study combined moving anatomy from computed tomography, computational fluid dynamics and numerical pathlines rather than directly measuring each parcel's velocity with the anatomical scanner.[ref]
Comprehensive left atrial flow component analysis reveals abnormal flow patterns in paroxysmal atrial fibrillation by Sophia Bäck and others. Methods, CT Acquisition and Flow Simulation; Flow Component Analysis
These complementary observations connect a visible chamber motion to a specific transport question.The atrial conduit flow component is blood entering the left atrium through the pulmonary veins during ventricular diastole and leaving through the mitral valve within that same ventricular diastole. The same-phase requirement distinguishes it from the atrial reservoir flow component and atrial delayed-ejection flow component.[ref]
An original two-history example shows why a volume curve alone cannot identify it. During a selected interval, suppose 20 mL enters the left atrium and 20 mL leaves through the mitral valve, leaving chamber volume unchanged. In history A, all 20 mL entering during that interval passes straight onward; it can qualify as atrial conduit flow component if the interval lies within one ventricular diastole. In history B, the 20 mL leaving is entirely older atrial blood, while the newly entering 20 mL stays behind. The same inflow, outflow and chamber volume change are compatible with different parcel identities.
The boundary balancecannot distinguish these histories. Here is net inward volumetric flow rate at the pulmonary veins and is net outward volumetric flow rate at the mitral valve. The additional information is the mapping between entry and exit, represented by pathlines.
This distinction also explains why atrial conduit function, a physiological role, and a particular volume-based proxy need not equal the atrial conduit flow component. A parcel volume collected over an interval need not be contained in the chamber simultaneously, so normalization requires an explicitly stated denominator rather than an assumed fraction of maximum atrial volume. The six histories below are constructed examples, not patient measurements.

Atrial booster-pump function is the active contribution of atrial contraction to ventricular filling. In the left atrium, contraction late in ventricular diastole helps drive blood through the open mitral valve. It supplements earlier filling associated with atrial conduit function, rather than accounting for all filling during the cardiac cycle.[ref]
Anatomy and Physiology 2e by J. Gordon Betts and others. §19.3, Cardiac Cycle, atrial systole and passive filling
A volumetric descriptor compares the chamber volume just before contraction, , with the subsequent minimum, . Their difference is the observed active-phase volume loss; the left atrial active emptying fraction usesFor constructed values 50 and 40 mL, the volume loss is 10 mL and this fraction is . Choosing the denominator is part of defining the descriptor.
That loss is not automatically all of the blood flow through the mitral valve during the interval. Integrating the left atrium's balance giveswhere is signed net pulmonary vein inflow over the same interval. If mL in the constructed example, 18 mL leaves through the mitral valve despite a chamber-volume decrease of only 10 mL.
A primary atrial flow component analysis reconstructed flow from time-resolved computed tomography and computational fluid dynamics, distinguishing modeled passage and residence histories.[ref]
Comprehensive left atrial flow component analysis reveals abnormal flow patterns in paroxysmal atrial fibrillation by Sophia Bäck and others. Abstract; Methods; Figure 7
This helps separate a phase-associated volume measurement from the route taken by each parcel. Likewise, an observed contraction-associated volume loss is not itself a controlled measurement of how much less ventricular filling would have occurred without contraction; pressure, timing and continuing inflow can also differ.Left atrial active emptying fraction is a volumetric descriptor of the relative decrease in left atrium volume during its active emptying phase. With volume immediately before atrial contraction and subsequent minimum volume ,The phase choice distinguishes this quantity from a fraction formed using the maximum atrial volume over the entire cardiac cycle. Atrial contraction normally contributes to late ventricular filling after earlier passive filling.[ref]
An original comparison uses mL and mL. Both chambers lose 10 mL, but their fractions are and . The denominator converts an absolute volume decrease into a relative one; it does not add an independent measurement of forward transport.
Timing is part of the measurement. With the first pair, choosing an earlier or later frame that gives mL instead of 50 mL changes the calculated fraction to , even if is unchanged. Consistent boundaries and phase identification therefore matter alongside image segmentation precision.
The fraction describes chamber-volume change, not all concurrent mitral valve flow. Pulmonary vein inflow during the interval contributes to the balance . Nor does the observed volume decrease isolate the causal effect of contraction from every other changing condition. A primary CT-based atrial flow component analysis compared volumetric indices with modeled transport components, illustrating the separation between volume measurements and parcel histories.[ref]
Comprehensive left atrial flow component analysis reveals abnormal flow patterns in paroxysmal atrial fibrillation by Sophia Bäck and others. Methods; Figure 7
Atrial booster-pump function is the physiological contribution; this fraction is one specified descriptor of its associated volume behavior.Atrial conduit function is the passive passage of returning blood through an atrium toward the ventricle, distinguished from temporary storage in atrial reservoir function and active pumping in atrial booster-pump function. For the left atrium, the pathway connects pulmonary vein inflow with mitral valve outflow during ventricular filling.[ref]
Two measurement descriptions need to be distinguished. A volumetric account compares chamber-volume changes with total ventricular filling. A parcel-based account asks when particular modeled blood enters and leaves the left atrium. A primary study defined conduit flow as entry and exit within the same ventricular diastolic phase and compared such components with volumetric indices.[ref]
Comprehensive left atrial flow component analysis reveals abnormal flow patterns in paroxysmal atrial fibrillation by Sophia Bäck and others. Abstract; flow-component definitions; Figure 7
The operational definition determines what is counted.An original bookkeeping model illustrates the volumetric approach. Suppose a periodic system has ventricular stroke volume , and suppose a reservoir release and direct onward passage form a complete, nonoverlapping partition of that delivered volume. ThenIf a further idealization identifies with the atrial excursion , values mL and an excursion of 30 mL give a conduit proxy of 50 mL. The arithmetic is exact for the stipulated partition; the correspondence between that partition and real trajectories is an additional assumption.
For example, simultaneous inflow and outflow can exchange blood while chamber volume remains constant. In the balance , equal 100 mL/s flows give zero volume change even though 20 mL passes in 0.2 s. Thus a flat volume trace does not demonstrate absent transport. Geometry, timing and modeled parcel histories supply information that volume extrema alone cannot provide.
Atrial reservoir function is the temporary storage of returning blood in an atrium during a phase when its inflow exceeds its outflow. For the left atrium, it is especially relevant while the mitral valve is closed during ventricular systole. It differs from passive onward passage, or atrial conduit function, and from the active late-filling contribution of atrial contraction.[ref]
A direct volume measure is the excursion over a specified cardiac cycle. Its denominator matters when it is converted into a ratio. An original example with volumes 70 and 40 mL gives mL, but and . These ratios describe different normalizations of the same excursion, not contradictory measurements.
The governing storage balance isA constant net inflow of 60 mL/s for 0.4 s stores 24 mL in this idealized interval. Neither the peak inflow rate nor a single chamber volume alone supplies the required integral. Over a repeating cycle with no net accumulation, total inflow and outflow must balance even though storage changes within the cycle.
The volume excursion also does not identify how long each parcel remains in the left atrium. A primary study reconstructed atrial flow using time-resolved computed tomography and computational fluid dynamics, then followed modeled particles to distinguish conduit, reservoir and longer-residence components.[ref]
Comprehensive left atrial flow component analysis reveals abnormal flow patterns in paroxysmal atrial fibrillation by Sophia Bäck and others. Abstract; Methods; Figure 7
Two atria can have similar maximum and minimum volumes while differing in which blood passes directly onward or remains through later phases. Storage volume and parcel residence are related questions, but they are different measurements. Articles by others on the same topic
There are currently no matching articles.