The left ventricle receives blood from the left atrium and pumps it into the aorta through the aortic valve. Its muscular wall supplies the pressure needed for systemic circulation. Pressure generation and the volume ejected are different measures of ventricular performance.
Ventricular compliance describes how much a ventricle's volume changes for a small change of distending pressure, with the mechanical state and other relevant conditions specified. For a passive chamber relation , its local value isThe distinction between intracavity and transmural pressure matters when external pressure changes. A large local compliance means a relatively large volume increment for a small pressure increment; its reciprocal is the local chamber stiffness. It is a chamber property and need not equal a material property of the muscular wall.
For a linear model , the derivative is constant. The quotient generally is not that compliance, because it also contains the reference volume . Nor does a single pressure-volume point determine a slope. The end-diastolic pressure-volume relationship instead assembles measurements at a specified phase over different filling states.
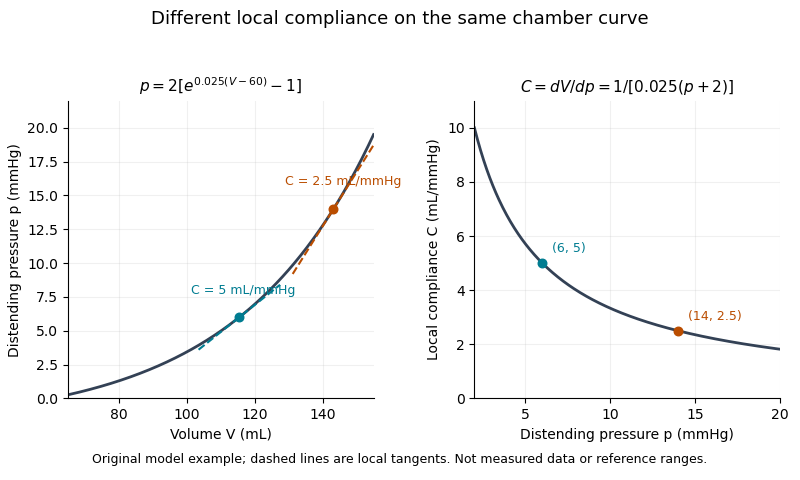
An original nonlinear model makes this distinction visible. TakeDirect differentiation givesWith stipulated mmHg and , the local compliances at pressures 6 and 14 mmHg are 5 and 2.5 mL/mmHg. The second operating point is less compliant even though the model parameters are unchanged. These are explanatory values, not human reference ranges or a diagnosis.

A primary experiment made the measurement problem concrete. Six excised dog hearts were perfused outside the body. An intraventricular balloon supplied a known volume, a micromanometer catheter recorded pressure, and echocardiography with automated boundary detection measured a mid-ventricular short-axis area. Repeated volume increments allowed pressure-area estimates to be compared with the balloon's pressure-volume reference. The reported agreement supported that experimental estimation method, while the authors explicitly left clinical validation open.[ref]
A pressure-volume trajectory during left ventricular filling also reflects time-dependent relaxation, valve flow and external constraints. Its instantaneous slope should not automatically be interpreted as the derivative of one fixed passive curve. Specifying the phase, pressure reference and conditions makes ventricular compliance a testable mechanical quantity rather than a synonym for filling volume.
The end-diastolic pressure-volume relationship describes ventricular pressure as a function of chamber volume at the end of diastole across different filling states. It is assembled from multiple end-diastolic observations, rather than from the entire time trajectory of one filling event. It is useful for describing passive chamber behavior when the activation state, pressure reference and external constraints are sufficiently controlled.
The local inverse slope is ventricular compliance:An intracavity-pressure curve and a transmural pressure curve can differ when surrounding pressure changes. Nor does a pressure-volume curve directly specify the material elasticity of the ventricular wall: chamber geometry also enters the relation.
For an original model, take , with . ThenThe upward curvature makes the chamber locally less compliant at larger volume without requiring any change in parameters. With mmHg, and mL, the pressures at 100 and 120 mL are 3.437 and 6.963 mmHg. Their secant estimate mL/mmHg describes that finite interval; the local compliance at 120 mL is about 4.46 mL/mmHg.
The pressure-volume relation was tested against imaging in a primary isolated-heart experiment. A balloon provided known ventricular volumes, a micromanometer recorded pressure, and automated echocardiography measured short-axis area in six perfused dog hearts. Repeated volume increments supplied multiple pressure-volume and pressure-area pairs. Their reported agreement concerned that experimental preparation, with clinical application explicitly left unvalidated.[ref]
Comparing curves also requires a size convention. If a model is written with reference volume , then . Two geometrically scaled chambers can therefore have different dimensional slopes even with the same normalized relation. Volume normalization of ventricular pressure-volume curves separates that comparison from a claim about changed wall properties. One observed end-diastolic point cannot identify an arbitrary curve or all three parameters of the exponential model.
Volume normalization of ventricular pressure-volume curves expresses chamber volume relative to a stated reference scale before comparing pressure-volume relations. It can separate the effect of chamber size from differences in the shape of an end-diastolic pressure-volume relationship. It does not automatically remove effects of wall thickness, geometry, external pressure or active state.
Let for fixed positive reference volume , and suppose . The chain rule givesThus equal normalized curves can have different dimensional ventricular compliances. The scaled compliance has units of inverse pressure and compares the same normalized operating point.
For an original example, take mmHg. At , pressure is 1.644 mmHg and mmHg. Chambers with and 200 mL then have volumes 120 and 240 mL and compliances approximately 9.147 and 18.294 mL/mmHg. Their compliances differ by twofold while agrees. These are chosen model chambers, not reference values.
An affine convention must state both its origin and scale . Choosing each curve's reference from the same data can also conceal the very shift being compared. Normalizing every single observation by its own volume makes every normalized volume one and destroys information about curve shape.
An experimental comparison needs independent volume information and a specified pressure reference. The 1994 isolated-heart study used known intraventricular balloon volumes, micromanometer pressure and image-derived ventricular area to compare pressure-volume and pressure-area measurements.[ref]
Estimation of left ventricular compliance using on-line echocardiographic automated border detection and pressure data by John Gorcsan III and others. Abstract, balloon reference, simultaneous imaging/pressure acquisition and validation limitation
That apparatus illustrates why a geometric surrogate must be checked before it becomes the denominator of a normalization.A transparent report identifies the reference volume, whether pressure is intracavity or transmural pressure, the cardiac phase and the operating points compared. A size-normalized chamber curve is still a chamber measurement; it is not by itself a material stress-strain relation for myocardium.
Left ventricular filling is the inflow of blood into the left ventricle, primarily through the mitral valve during diastole. It depends on the pressure difference between the left atrium and ventricle, valve-flow resistance and the ventricle's changing mechanical state. A volume increase is an integrated transport observation, not simply another name for one measured pressure.
With an ideal open mitral pathway of hydraulic resistance and no simultaneous outflow, an original reduced model isThis expression applies while the pressure difference favors filling; an ideal one-way valve would otherwise set . To isolate a passive filling timescale, assume constant atrial pressure and a linear ventricular relation , where represents ventricular compliance in a fixed mechanical state. ThenThe product has units of time. A longer available filling interval and a different mechanical or hydraulic timescale have distinct effects on the final volume.
For stipulated mL, initial volume mL and s, the modeled volumes at 0.5 and 1 s are approximately 91.5 and 110.6 mL. The added amounts are 31.5 and 50.6 mL. These are mathematical examples, not normal human reference values. Actual filling also involves active relaxation, atrial contraction, moving boundaries and changing flow conditions, all omitted from this constant-parameter model.
A primary experiment in six sheep reconstructed ventricular and mitral annulus markers using biplane fluoroscopy, then estimated how annular motion contributed to filling volume.[ref]
Contribution of mitral annular dynamics to LV diastolic filling with alteration in preload and inotropic state by C. Carlhäll and others. Abstract, marker reconstruction and tetrahedral volume estimates
Its apparatus makes moving geometry observable, complementing a pressure-flow model rather than treating the chamber boundary as fixed.A complete interpretation therefore identifies whether the observation is chamber volume, boundary motion, valve-flow speed or transported volume. Their relationship follows from the measurement geometry and conservation of mass, with any other inflow or outflow included in the balance.
The left ventricular outflow tract, LVOT, is the passage within the left ventricle leading to the aortic valve. It links the ventricular cavity with the aortic root; the neighboring anterior mitral valve leaflet and ventricular septal structures help define this outflow region.[ref]
Anatomy and Physiology 2e by J. Gordon Betts and others. §19.1, Left Ventricle and internal heart anatomy
[ref]Surgical anatomy of the aortic valve and root—implications for valve repair by Ruggero De Paulis and Andrea Salica. General considerations; The VAJ and the VBR
Its measurement is useful in Doppler echocardiography. In a fixed-area model, a cross-sectional area and area-mean axial velocity give the forward transported volumewhere the velocity-time integral has dimensions of length. It is not a peak velocity or a volume by itself. The primary technical report uses paired diameter and Doppler measurements at a consistent outflow site.[ref]
Recommendations for Noninvasive Evaluation of Native Valvular Regurgitation by William A. Zoghbi and others. Section II.B.6.a, quantitative pulsed Doppler; Table 7, SV method
For a stipulated circular diameter cm and velocity-time integral 20 cm,If the measured diameter is instead 2.2 cm with the same integral, the estimated area and volume both increase by , or . A diameter change therefore does not produce only a volume change.
The approximation requires consistent geometry and velocity sampling. A noncircular outline, changing area, nonuniform flow or an angled ultrasound beam can alter the relation between a measured signal and area-mean velocity. The left ventricular outflow tract also names anatomy, while aortic stenosis names a pathological narrowing at the valve: a passage's location alone does not establish whether it is obstructed.
Time-dependent elastance models the pressure generated by a cardiac ventricle at its current stressed volume. The reference is its zero-pressure volume. The inverse of elastance is compliance at fixed time. Rising elastance increases pressure without volume change during isovolumetric contraction; an approximately constant systolic value gives compliance during a simplified ejection stage.
If an open aortic valve equilibrates pressure much faster than peripheral outflow, the arteries and ventricle share a common pressure while their combined blood volume is conserved during the short adjustment. Let arterial vascular compliance be and systolic ventricular elastance be . Equating the initial and final arterial-plus-ventricular stored volumes gives the displayed pressure. Subsequent peripheral drainage sees the combined compliance ; during filling a closed aortic valve removes the ventricular contribution.
After a rapid switch to systolic compliance , negligible valve resistance equalizes arterial and ventricular pressures. Neglecting runoff during this short stage conserves combined stored volume and gives the displayed pressure. Thereafter, with closed mitral valve, negligible venous pressure and constant , the pressure decays as . At firing duration , the stroke volume is . Each approximation follows from an explicit valve or time-scale separation condition.
Articles by others on the same topic
There are currently no matching articles.