Past exam of the beliefs, behaviours and biology course of the University of Oxford 2022 6 Solution by  Codex 0 2026-10-25
Goffman's claim is illuminating as an account of how stigma can deny full personhood, but it should not be treated as a literal universal belief held by everyone who encounters a psychosis diagnosis. Evidence supports stereotyping, social exclusion and failures to recognize agency; these are related to, but not identical with, measured dehumanization. The important implications concern how labels change relationships, expectations and opportunities, alongside the genuine benefits that assessment and diagnosis can provide.
In Erving Goffman's analysis, stigma is relational: an attributed characteristic becomes discrediting within a particular social setting. Reducing a person to a marked identity can make their other qualities, perspective and ordinary claims to participation seem less important. The quoted passage captures this moral reduction. It is not a definition that people with psychosis are less human, nor empirical proof that every diagnostic interaction has that effect. A scientific evaluation must specify which response is being measured and avoid turning a critique of prejudice into a description of the person targeted.[ref]
Stigma: notes on the management of spoiled identity by Erving Goffman. 1963; Stigma and Social Identity, including the passage identified in this examination
Several constructs need separation. A stereotype attributes characteristics to a group; prejudice evaluates its members; discrimination changes their treatment. Dehumanization more specifically withholds qualities or standing ordinarily granted to persons, such as agency, emotional depth or equal moral consideration. Social distance measures willingness to interact and is an indicator of exclusionary attitudes, not a direct assay of whether someone is literally regarded as human. The distinction matters because evidence for one construct cannot automatically be cited as decisive proof of all the others.
Bernice A. Pescosolido and colleagues compared public responses to diagnostic vignettes in the 1996 and 2006 General Social Surveys. Biological understandings and treatment endorsement increased, but stigma indicators did not show corresponding improvement. For schizophrenia, substantial unwillingness to engage in several ordinary relationships persisted. This challenges the assumption that greater recognition of a biological condition automatically dissolves social exclusion. Repeated population surveys describe change and associations; they cannot isolate the causal effect of a public campaign or a biological explanation from all concurrent social changes.[ref]
A disease like any other? A decade of change in public reactions to schizophrenia, depression, and alcohol dependence by Bernice A. Pescosolido and others. 2010; repeated vignette surveys, biological attributions and social-distance outcomes
The implication is not that biological knowledge is intrinsically stigmatizing. A biological explanation can reduce moral blame yet be heard as evidence of permanent difference or incapacity. Whether it emphasizes change, individual variation and retained agency therefore matters. Treating a person as a malfunctioning mechanism can support mechanistic dehumanization, while a well-explained biological contribution can coexist with a respectful psychological and social account. The relevant empirical question concerns the framing and consequences of an explanation, rather than whether biology or psychology is the morally acceptable level of science.
Matthew S. Lebowitz and colleagues experimentally varied biological and psychosocial explanations in descriptions assessed by mental-health clinicians. Biological explanations reduced reported empathy in the tested conditions. Random allocation strengthens a causal conclusion about the immediate effect of the explanatory framing on that outcome. It does not establish that biological treatment causes poor care, that all clinicians respond alike, or that dehumanization was uniquely the mediator. Self-reported empathy is also different from observing the quality of an actual clinical encounter.[ref]
Effects of biological explanations for mental disorders on clinicians' empathy by Matthew S. Lebowitz and others. 2014; explanation manipulations and clinician-reported empathy
Evidence from people receiving diagnoses is especially important because exclusion is not exhausted by public opinions. Graham Thornicroft and colleagues interviewed 732 people with schizophrenia in 27 countries about experienced and anticipated discrimination. Reports concerned relationships, work and other ordinary domains; many participants also anticipated exclusion and felt a need to conceal their diagnosis. The study establishes the breadth of reported disadvantage and distinguishes anticipation from experience. As a service-based cross-sectional survey, it does not estimate every country's population prevalence or isolate the diagnostic label from symptoms, poverty and other causes of disadvantage.[ref]
Global pattern of experienced and anticipated discrimination against people with schizophrenia: a cross-sectional survey by Graham Thornicroft and others. 2009; face-to-face interviews and separate experienced/anticipated discrimination measures
Anticipation can itself restrict opportunities even before a particular rejection occurs. Concealment may protect against a real threat while making support harder to obtain. Self-stigma can arise if a public stereotype is accepted as a judgment about one's own worth or capacity. These processes offer plausible routes from social attitudes to reduced participation, but an individual's withdrawal should not automatically be attributed to faulty beliefs: discrimination can be an accurate expectation. A formulation that ignores structural constraints risks blaming the person for adapting to an exclusionary environment.
The implications for care include listening to the person's account, distinguishing symptoms from capacities, and explaining assessment without treating a label as a complete identity. Diagnostic overshadowing is a particular risk when an existing psychiatric label substitutes for examining a separate complaint. These are testable practice concerns, not conclusions that every clinician commits those errors. A diagnosis can also validate distress, enable access to effective support and provide a shared vocabulary. Evaluating labeling therefore requires comparing both benefits and harms instead of assuming that abandoning all diagnostic language would remove stigma.
Intervention evidence gives a reason to reject inevitability. Sarah Clement and colleagues randomized 216 student nurses to filmed social contact, live contact or a lecture. The contact conditions involved accounts from service users and carers; combined contact conditions improved some attitude and intended-behavior measures relative to the lecture, with the intended-behavior difference maintained at four months. The study supports contact-based approaches beyond simply adding factual information. Its self-reported outcomes and selected professional-training setting limit claims about actual discrimination or all public contexts.[ref]
Filmed v. live social contact interventions to reduce stigma: randomised controlled trial by Sarah Clement and others. 2012; randomized contact formats, lecture comparison and four-month follow-up
An intervention should consequently be judged on consequential treatment and participation as well as knowledge scores. Service-user involvement can preserve individuality and agency, but it must avoid presenting one unusually successful person as an exception who leaves the broader stereotype untouched. Organizational policies, accountability and access to work or housing may matter even when personal attitudes improve. Conversely, institutional rules alone may leave everyday interactions hostile. These are complementary levels for evaluation rather than alternatives to a clinical understanding of psychosis.
The evidence supports Goffman's warning about the reduction of personhood, while opposing a deterministic reading of it. Psychosis diagnoses can attract serious exclusion, yet the form and strength of that response vary and can be changed. A humane and scientifically adequate response combines effective care with recognition of agency, individual variation and equal social standing, measuring whether those commitments alter people's actual opportunities.
Past exam of the beliefs, behaviours and biology course of the University of Oxford 2022 5 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Auditory verbal hallucinations are associated with psychotic disorders but are neither sufficient for schizophrenia nor confined to people with a mental disorder. Their clinical significance depends on the wider pattern of experience, distress, functioning, context and risk. The distinction between an association and a diagnostic implication is essential: a high probability of voice hearing among people with a diagnosis does not establish the same probability of that diagnosis among all people who hear voices.
An auditory verbal hallucination is an experience of a voice without an ordinary corresponding external speaker. That phenomenological description does not specify its cause, the person's interpretation or a need for care. Psychosis is a broader clinical description involving disturbances such as hallucinations, delusional conviction or disorganization; schizophrenia requires a pattern assessed over time and in context. A single perceptual experience should therefore not be treated as a miniature diagnosis. Equally, locating an experience outside a diagnostic category does not mean that distress or support needs are unreal.
Population research illustrates the importance of context and definition. Maurice M. Ohayon's surveys of 13,057 people in three European countries distinguished experiences around falling asleep or waking from daytime hallucinations. Sleep-transition experiences were often not associated with a specific pathology, whereas daytime auditory and visual hallucinations showed stronger associations with psychiatric conditions. Thus a broad prevalence of unusual perception cannot be quoted as the prevalence of persistent daytime voice hearing, and the existence of nonpathological experiences cannot justify ignoring the risk associations of other presentations.[ref]
Prevalence of hallucinations and their pathological associations in the general population by Maurice M. Ohayon. 2000; representative telephone surveys, timing and pathological associations
More directly, Kirstin Daalman and colleagues compared 118 clinical and 111 otherwise healthy people who reported recurrent auditory verbal hallucinations. Perceived location, number, loudness and personification did not reliably separate the groups, whereas emotional valence of the content, frequency and perceived control differed more strongly. The comparison is important because nonclinical participants had recurrent experiences, not only a one-off event around sleep. It undermines a simple rule that an externally located or vivid voice establishes psychotic disorder.[ref]
The same or different? A phenomenological comparison of auditory verbal hallucinations in healthy and psychotic individuals by Kirstin Daalman and others. 2011; recurrent voice-hearer groups and phenomenological dimensions
The findings do not mean that the groups are identical. Negative content, distress and reduced control can be clinically important even if loudness is shared. Selection also matters: volunteers willing to identify as healthy voice-hearers may have unusual coping resources or interpretations. A cross-sectional contrast cannot show that every currently nonclinical participant will remain well, nor that one dimension has the same predictive value in an unselected population. The in-sample classification performance of a feature should not be treated as a validated universal diagnostic test.
Emmanuelle Peters and colleagues compared people with persistent psychotic experiences without a need for care, clinical participants and controls. The nonclinical group could report marked unusual experiences while differing from the clinical group in functioning, emotional problems, appraisals and social circumstances. Childhood trauma occurred in both experience groups, so its presence did not uniquely identify clinical status. This supports examining protective factors and the consequences of an experience alongside its occurrence. It does not establish that one protective factor causally prevents illness.[ref]
Clinical, socio-demographic and psychological characteristics in individuals with persistent psychotic experiences with and without a need for care by Emmanuelle Peters and others. 2016; clinical, nonclinical persistent-experience and control-group characterization
An appraisal account proposes that the meaning assigned to an experience helps determine distress and action. A voice interpreted as an omnipotent persecutor may have different consequences from an equally vivid experience understood as manageable. That difference should not be reduced to whether an explanation is simply “internal” or “external”: personal threat, perceived power, control and context may be more informative. Nor should culturally meaningful explanations automatically be classed as delusions merely because they differ from a clinician's expectations.
Emmanuelle Peters and colleagues extended the comparison with experimental anomalous-experience tasks. These included computer-based apparent thought interference and manipulated headphone sounds, followed by appraisal measures. Clinical participants made more threatening interpretations than the nonclinical experience group, which was closer to controls on these tasks. Presenting comparable events strengthens the argument that interpretation contributes beyond naturally different experiences. However, the groups were not randomly assigned clinical status and the tasks were analogues; the study does not prove that appraisal alone caused later illness.[ref]
Clinical relevance of appraisals of persistent psychotic experiences in people with and without a need for care: an experimental study by Emmanuelle Peters and others. 2017; three induced-experience tasks, interviews and appraisal comparisons
Biological observations do not restore a one-to-one diagnostic mapping. Kelly M. J. Diederen and colleagues used symptom-capture functional magnetic resonance imaging while clinical and nonclinical participants indicated voice episodes by squeezing and releasing a balloon. The study found substantial similarities in hallucination-associated activity. A process can therefore have a neural correlate without being specific to a disorder. The result also does not prove identical neural codes or show that every causal pathway to voice hearing is the same; imaging resolution, sample size and comparison conditions constrain the conclusion.[ref]
Auditory hallucinations elicit similar brain activation in psychotic and nonpsychotic individuals by Kelly M. J. Diederen and others. 2012; symptom-capture imaging, balloon-squeeze/release episode indication and group comparison
This distinction between experience and disorder has two-sided implications. Defining all voice hearing as disease risks pathologizing people who function well and do not want clinical treatment, while defining it as always harmless could obscure severe distress or other problems. Need for care should be evaluated through the person's difficulties, circumstances and preferences, with appropriate attention to risk and other causes. Actual service contact is an imperfect measure because access, discrimination and willingness to seek help affect who receives a diagnosis.
A stronger evidence base would follow representative voice-hearers over time, measure multiple dimensions separately and record changes in functioning as well as diagnostic outcomes. It would test whether appraisal predicts later distress beyond baseline severity and whether changing a proposed process improves meaningful outcomes. Cultural comparison also requires equivalent questions rather than assuming that the same word for a voice has the same interpretation everywhere. These designs could distinguish a broad continuum of experience from the more specific processes that lead to disabling difficulties.
Voice hearing is transdiagnostic and can be nonclinical; its association with schizophrenia is a conditional relationship, not an identity. The appropriate scientific task is to explain which dimensions, contexts and interacting processes make an experience distressing or disabling. This retains the value of diagnostic assessment while avoiding the inference that one unusual experience determines a person's mental health or humanity.
Past exam of the beliefs, behaviours and biology course of the University of Oxford 2022 4 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Valuing health does not entail interpreting every sensation as evidence of grave disease. Intense health anxiety depends on how probability, consequences, coping and uncertainty are appraised, and on whether attention and safety behavior create a self-confirming cycle. Understanding ordinary calibration suggests treatment targets that preserve sensible health care while reducing disabling certainty seeking. The contrast is between ways of responding to uncertainty, not between caring about health and being indifferent to it.
Bodily signals are ambiguous. A change may have several explanations, and a very serious possible outcome can still be unlikely given a particular cue. The severity of a consequence and the conditional probability of its occurrence are distinct quantities. In a simple Bayesian illustration, let be an imaginary illness and an ambiguous signal. ThenIf, purely for illustration, , and , the posterior probability is about . These invented values are not estimates for any actual symptom or illness. They show why knowing that a disease can produce a signal does not establish that the signal probably means that disease.
Ordinary calibration also involves alternatives, changing information and coping. People can judge a symptom worth evaluating without assuming that only a guarantee of safety would permit normal activity. They may interpret a sensation in the context of recent activity, retain a distinction between possibility and probability, and revise their belief when appropriate evidence arrives. These are functional contrasts, not an assertion that everyone without severe health anxiety performs explicit Bayesian calculations or is always accurate. Neither realistic risk nor a prior medical experience automatically produces disabling anxiety.
The cognitive model of health anxiety identifies a different pattern: an illness interpretation increases anxiety and somatic hypervigilance; those responses increase the salience of sensations; further sensations are treated as corroboration. Reassurance seeking, repeated checking or avoidance can provide immediate relief while leaving the underlying interpretation untested. Hilary Warwick and colleagues proposed this maintenance account as an alternative to conceptualizing the difficulty merely as insufficient medical information. It explains why adding another statement of reassurance may not have the same effect as changing how evidence is interpreted.[ref]
Hypochondriasis by Hilary Warwick and others. 1990; proposed attentional, interpretive and behavioral maintenance processes
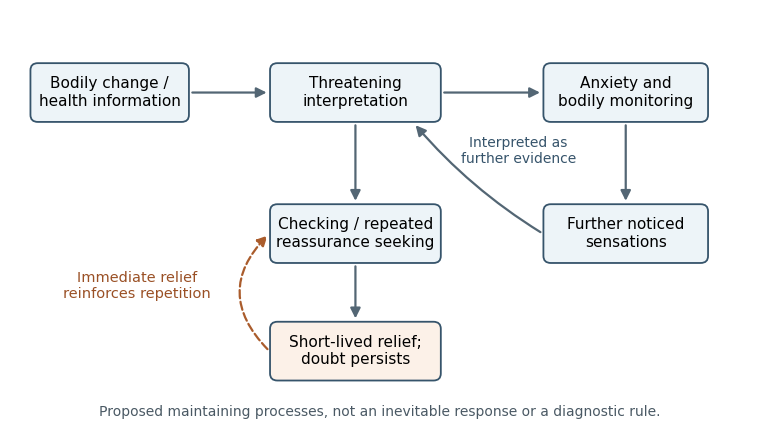
A proposed maintenance cycle for health anxiety; arrows represent testable processes, not inevitable responses to bodily changes
. Details. 
Intolerance of uncertainty can raise the required standard of evidence beyond what medical investigation can supply. If every residual possibility demands another check, a negative result can be reinterpreted as the wrong test, the wrong time or a missed condition. This account predicts repeated doubt despite short-term relief, rather than the absence of genuine concern or comprehension. It also explains a possible paradox: a response chosen to reduce anxiety can maintain the demand for certainty. The person's reason for the behavior must be established; the same observable action could be proportionate care in another context.
An appropriate formulation therefore distinguishes the presence of physical illness, the degree of concern and the pattern of maintaining responses. These are not mutually exclusive categories. Paul Salkovskis and colleagues developed the Health Anxiety Inventory to measure health anxiety across relevant clinical and medical samples rather than simply counting bodily symptoms. The validation studies compared several anxiety presentations, examined sensitivity to change and included people seeking help for physical illness. This supports measuring the psychological response separately from a conclusion about whether a disease exists. A questionnaire still does not replace clinical assessment.[ref]
The Health Anxiety Inventory: development and validation of scales for the measurement of health anxiety and hypochondriasis by Paul Salkovskis and others. 2002; clinical comparisons, treatment sensitivity and physical-illness samples
Treatment implications follow as hypotheses about learning. Collaborative cognitive behavioral therapy can identify the feared interpretation, the alternative account and what would distinguish them. A behavioral experiment should test a specified prediction about attention or a safety behavior, rather than require the person to prove that future illness is impossible. Attention can be examined as a process that changes experience, not as a declaration that every sensation is caused by attention. Likewise, reducing a repetitive reassurance cycle is different from withholding a needed explanation or discouraging appropriate medical evaluation.
The therapeutic stance is consequently important. Dismissing a symptom can reinforce the belief that the danger has not been understood. A shared formulation can instead acknowledge the sensation, explain how anxiety may amplify it and leave room to revise the account. Appropriate information may be useful, but the aim is a more flexible standard for updating and coping. This also makes the account falsifiable: if the predicted relationship between a response and the difficulty is not observed, the formulation should be reconsidered rather than blaming the person for failing to improve.
Erik Hedman and colleagues randomized 81 people with severe health anxiety to therapist-guided internet cognitive behavioral therapy or an attention-control condition over 12 weeks. The treatment produced a substantially greater reduction in health anxiety on the study measures. This gives evidence beyond the intuitive plausibility of the model and suggests that extensive face-to-face contact is not necessary for every effective delivery format. The trial does not isolate every treatment component or show that internet delivery suits every patient, and a selected trial sample limits generalization.[ref]
Internet-based cognitive-behavioural therapy for severe health anxiety: randomised controlled trial by Erik Hedman and others. 2011; masked-assessment randomized comparison, attention control and Health Anxiety Inventory outcome
The CHAMP medical-outpatient trial provides a complementary setting in which physical illness was permitted. Its health anxiety benefit reinforces the distinction between addressing an anxious maintenance cycle and denying medical disease. However, symptom improvement, functioning, costs and quality of life are different outcomes and should not be collapsed into one claim of success. The model should also accommodate social circumstances and access to care: repeated concern in a setting where appropriate assessment is unavailable cannot simply be assumed to reflect an internal cognitive bias.[ref]
Cognitive-behaviour therapy for health anxiety in medical patients (CHAMP): a randomised controlled trial with outcomes to 5 years by Peter Tyrer and others. 2017; medical eligibility, symptom follow-up and distinct economic endpoints
The useful clue from ordinary responding is the ability to combine concern with proportionate interpretation, evidence updating and tolerable uncertainty. A mechanistic treatment account aims to restore those functions by testing interpretations and changing maintaining responses, with appropriate medical collaboration. It does not promise certainty, identify all bodily symptoms as benign, or treat anxiety as evidence that a person's health concern is invalid.
Past exam of the beliefs, behaviours and biology course of the University of Oxford 2022 3 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Panic disorder and social anxiety disorder illustrate a shared feedback architecture with different feared outcomes and sources of apparent evidence. Treatment can share collaborative cognitive behavioral methods while changing the experiments, attentional targets and safety behaviors according to the formulation. In both, an anxiety response can become part of the perceived proof of danger. A diagnosis indicates a pattern of difficulty; it does not establish that all cases have an identical maintaining process.
In panic disorder, recurrent unexpected panic attacks are followed by concern or behavioral change related to further attacks. The cognitive account emphasizes catastrophic misinterpretation of bodily sensations: an acceleration of heart rate, dizziness or altered breathing may be interpreted as imminent collapse, loss of control or another catastrophe. The interpretation increases anxiety, which generates further sensations, reinforcing the threat interpretation. Avoidance and safety behaviors can prevent learning that the sensations would have changed without the precaution. Appropriate assessment remains necessary because a cognitive formulation does not determine the medical origin of any individual symptom.
David M. Clark's original account specifies this feedback process rather than equating panic with generally high stress. It predicts that the meaning assigned to a sensation should matter more than its physical presence alone. The same sensation could be frightening in one interpretive context and relatively unremarkable in another. This explanatory distinction is useful because it suggests testable comparisons between predictions, rather than relying solely on relaxation or a verbal assurance that nothing dangerous will occur. The original paper is a model, not itself a randomized demonstration of every link.[ref]
A cognitive approach to panic by David M. Clark. 1986; proposed catastrophic-interpretation feedback account
Social anxiety disorder instead centers on feared scrutiny and negative evaluation. In an interaction, self-focused attention can shift processing from the actual conversation to sensations and an imagined view of oneself. A negative self-image may be treated as if it were an observer's report. Safety behaviors such as mentally rehearsing every sentence or restricting engagement can reduce spontaneity, obscure the evidence needed to test a prediction and sometimes change how the interaction develops. Post-event processing can then select apparent failures and preserve the threatening impression for the next encounter.
The disorders therefore share an interpretive loop but differ in what would count as disconfirming evidence. In panic, the feared event may concern the immediate meaning of a bodily sensation. In social anxiety, it may concern another person's appraisal, an uncertain social consequence or the belief that anxiety is visibly unacceptable. Simply remaining in a situation is not an adequate experimental description: someone may remain while attributing safety to a precaution, directing attention inward or interpreting an ambiguous response as rejection.
Experimental evidence tests this functional argument. Paul Salkovskis and colleagues manipulated safety-seeking behavior during exposure in panic disorder with agoraphobia. The study supports examining what the person does during exposure rather than treating exposure duration as its only relevant feature. It does not imply that every protective behavior is unnecessary, nor that an effect in a short task demonstrates the complete mechanism of long-term recovery. The prediction being tested and the person's explanation of the outcome remain important.[ref]
An experimental investigation of the role of safety-seeking behaviours in the maintenance of panic disorder with agoraphobia by Paul Salkovskis and others. 1999; experimental manipulation of safety-seeking behavior during exposure
For social anxiety, Freda McManus and colleagues first assessed safety behaviors by interview and then manipulated safety behaviors and self-focus experimentally. Greater safety behavior use characterized high social anxiety, and the manipulation supported adverse effects of the combined maintaining processes. The interview association alone would allow reverse causation; the experimental contrast provides stronger evidence of an immediate influence. Because attention and behavior were manipulated together, it is less decisive about their independent effects. Brief arranged interactions also cannot establish the magnitude of lasting treatment benefit.[ref]
Why social anxiety persists by Freda McManus and others. 2008; interview study and experimental safety behavior/self-focus manipulation
Both treatments can begin with a shared clinical formulation, specified predictions and behavioral experiments. In panic, interoceptive exposure can make relevant sensations available for testing while changing the safety behavior that would otherwise be credited with preventing catastrophe. The learning question concerns the predicted consequence and the meaning of the sensation, not merely whether anxiety eventually declines. In social anxiety, experiments can redirect attention to the interaction and test predicted evaluations while reducing relevant safety behaviors. The content is matched to social interpretation rather than transferred mechanically from a bodily-sensation exercise.
Video feedback is particularly pertinent when a person treats a negative self-image as an accurate external view. Preparing a clear prediction about appearance and then comparing it with the recording creates a more interpretable test than simply asking the person to watch themselves. A recording is still a limited sample, and the person's selective interpretation of it needs examination. Social experiments may also test how others respond to ordinary imperfections rather than making perfect performance the criterion for safety. These principles follow from the proposed maintaining process and should remain open to outcome evaluation.
Treatment comparisons provide evidence at a broader level. David M. Clark and colleagues' panic trial compared cognitive therapy, applied relaxation and imipramine, with self-exposure homework shared across conditions. The cognitive therapy findings support the package, but common homework means that differences cannot be attributed to exposure being present in one arm and absent in all others. Therapist effects, credibility, dose and follow-up are also relevant when interpreting comparative outcomes.[ref]
A comparison of cognitive therapy, applied relaxation and imipramine in the treatment of panic disorder by David M. Clark and others. 1994; treatment conditions, shared self-exposure homework and follow-up
In social phobia, David M. Clark and colleagues randomized participants to cognitive therapy, exposure with applied relaxation or a waiting condition. Cognitive therapy showed a stronger outcome than the exposure/relaxation package on the principal comparisons. This is evidence against treating all interventions that contain exposure as interchangeable. It does not establish that a single feature, such as video feedback, explains the difference, because the packages differ on multiple dimensions. A dismantling study or a carefully specified mediation design would be needed for that narrower causal claim.[ref]
Cognitive therapy versus exposure and applied relaxation in social phobia: a randomized controlled trial by David M. Clark and others. 2006; randomized package comparison and follow-up
Treatment planning also needs the person's goals, comorbidity and constraints. A ritualized breathing strategy, inward monitoring or avoidance can serve different functions in different cases; its name does not determine its effect. Outcomes should include functioning and flexibility alongside symptom scores, and tests of maintenance should examine whether feared situations can be approached without recreating the same safety rules. This is why a transdiagnostic process can justify shared principles without requiring a single standardized sequence for everyone.
The shared targets are threatening interpretation, self-confirming attention and safety behavior that obstructs updating; the specific targets depend on whether bodily catastrophe or social evaluation organizes the difficulty. Evidence for package efficacy and evidence for a proposed mechanism answer different questions. Effective comparison requires both, with the limits of the experimental manipulation kept distinct from those of the clinical trial.
Past exam of the beliefs, behaviours and biology course of the University of Oxford 2022 2 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25A recognizable hoarding syndrome can coexist with more than one causal route. Research must test whether there is a stable, informative pattern of mechanisms and predictions beyond the visible accumulation, rather than treating either a diagnostic label or heterogeneity alone as decisive. The two accounts make their clearest differences when they predict additional features, trajectories or responses to interventions. A classification can be useful without asserting one necessary biological lesion in every affected person.
Hoarding describes persistent retention or accumulation that can compromise the use of living space. A clinical account additionally considers difficulty discarding, distress, impairment, acquisition and the reasons for retaining objects. Mere ownership of many objects is not enough: restricted space, poverty, collecting, the preferences of other household members and access to practical support affect clutter. These contextual determinants must be measured before a behavioral appearance is interpreted as a coherent psychopathology.
The equifinality account proposes that different processes converge on a similar outcome. Retention might express feared consequences of discarding, unusually strong attachment, difficulty making decisions or a loss of the capacity to organize possessions. These are candidate routes to examine, not diagnoses that can be inferred from a photograph of a room. A more coherent-disorder account predicts that a characteristic cluster of processes covaries, persists and explains incremental impairment beyond other conditions. It need not predict that every participant has every proposed process.
Randy O. Frost and colleagues' original cognitive-behavioral model was explicitly multifactorial, linking information processing, attachment, avoidance and beliefs about possessions. The model therefore supplies hypotheses about processes rather than identifying one defining defect. It also shows why a simple contrast between “one disorder” and “many processes” can be misleading: a coherent account can include interacting mechanisms. The discriminating question is whether their joint structure has explanatory and predictive value.[ref]
A cognitive-behavioral model of compulsive hoarding by Randy O. Frost and others. 1996; original four-part theoretical model
An initial study should recruit from community, medical and specialist services, not only an obsessive-compulsive disorder clinic. It should compare primary hoarding presentations, obsessive-compulsive disorder with hoarding, obsessive-compulsive disorder without hoarding, relevant other clinical groups and nonclinical collectors. Blinded interviews, home observations and multiple informants would distinguish distress from household impairment and establish why objects are retained. Sampling across the severity range would help avoid making a diagnostic boundary look categorical merely because the study excluded intermediate cases.
Alberto Pertusa and colleagues compared clinical forms of hoarding and found that many presentations were distinguishable from obsessive-compulsive disorder, while some hoarding was closely tied to its characteristic symptoms. Apparent overlap with another diagnostic category could also arise from shared item content. This supports careful differential characterization and warns against assuming that all retention has the same function. Cross-sectional clinical separation, however, cannot by itself identify the developmental cause of either subgroup.[ref]
Compulsive hoarding: OCD symptom, distinct clinical syndrome, or both? by Alberto Pertusa and others. 2008; clinical comparisons, OCD-related presentations and overlapping diagnostic items
Measurement should distinguish accumulation, discarding difficulty, acquiring, emotional attachment and organizational problems. Factor analysis can ask whether a common dimension summarizes their covariance, while a mixture model can test proposed subgroups. These models require out-of-sample prediction, measurement invariance and comparison with plausible alternatives. A factor is not automatically a common cause: correlated indicators may arise because clutter itself increases avoidance and further impairs organization. Equally, identifying several factors does not refute a coherent syndrome. Statistical structure must be connected to mechanisms through additional evidence.
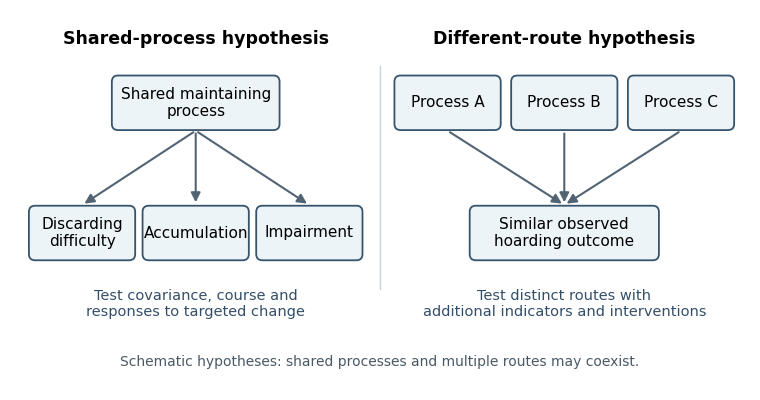
Alternative hypotheses about a shared hoarding outcome; schematic possibilities rather than established subtypes
. Details. 
There is a basic identifiability limit. Suppose records a symptom and a hidden pathway label is . If both pathways generate , then every mixture proportion gives . A symptom-only sample has likelihood and cannot identify which pathway produced it. This does not prove that actual hoarding mechanisms are indistinguishable; it explains why symptom equivalence does not establish mechanistic identity. Additional indicators, longitudinal observations or targeted perturbations are required to distinguish the proposed accounts.
An experimental approach can vary the ownership and emotional significance of possessions while holding perceptual features as similar as practicable. David F. Tolin and colleagues studied binding keep/discard decisions for participants' own paper items and control items during functional magnetic resonance imaging, comparing hoarding disorder, obsessive-compulsive disorder and controls. Ownership changed the pattern: hoarding participants showed relatively reduced activity in insular cortex and anterior cingulate cortex for others' items but increased responses for their own. The actual possibility of shredding made the decision consequential.[ref]
Neural mechanisms of decision making in hoarding disorder by David F. Tolin and others. 2012; task instructions, binding decisions and ownership-dependent group differences
This is more informative than comparing undifferentiated resting activity, but the result does not establish a unique hoarding mechanism. Ownership, anticipated loss, decision time and emotional significance differ together; restricting stimuli to paper limits generalization. Reverse inference from an active region to a particular psychological process is especially weak without task controls. A stronger extension would independently vary ownership and experimentally established beliefs about usefulness, then test whether the predicted response generalizes to everyday decisions and alternative objects.
Longitudinal studies should measure proposed mechanisms before changes in accumulation and impairment. A coherent-mechanism account predicts that those measures explain subsequent change beyond baseline severity and other difficulties; a multiple-route account predicts reproducible pathways with different sequences. Repeated measurements could distinguish a vulnerability from a consequence of years of clutter. Family or biological associations might contribute, but shared liability is neither proof of one process nor a requirement that every case have the same origin.
Treatment studies offer a further test if they manipulate theoretically distinct components. Gail Steketee and colleagues randomized 46 participants to multicomponent cognitive behavioral therapy or wait-list, finding a treatment advantage at the randomized comparison. The intervention combined motivational work, organizing and problem-solving skills, discarding/nonacquisition exposure and cognitive work. That combination supports clinical benefit but does not reveal which component was necessary or which causal route it changed. Later improvement among completers must also be separated from the original randomized contrast.[ref]
Waitlist-controlled trial of cognitive behavior therapy for hoarding disorder by Gail Steketee and others. 2010; 12-week randomized comparison and subsequent 26-session treatment
A dismantling study could compare matched packages with and without a hypothesized component, measuring its proposed mediator before the outcome. Prespecified treatment-by-mechanism interactions would test whether people with different retention functions require different components. Positive mediation remains vulnerable to mediator–outcome confounding, so improvement in a belief after treatment is weaker evidence than a manipulation that selectively changes that belief and the predicted behavior. Practical barriers and opportunity to discard must also be distinguished from psychological inability.
The best resolution is comparative and predictive: test whether syndrome-level measures add reliable information and whether distinct mechanisms produce reproducible differential predictions. Existing clinical, experimental and treatment evidence supports more specificity than an undifferentiated “clutter” endpoint, while leaving room for multiple routes. A useful diagnosis and an equifinal behavior are compatible; what needs testing is the scope and precision of the mechanism claimed.
Past exam of the beliefs, behaviours and biology course of the University of Oxford 2022 1 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Obsessive-compulsive disorder and severe health anxiety can share a cycle of threatening interpretation, distress and short-lived relief from safety behavior, while differing in the feared meaning and the function of the response. Effective treatment therefore needs both a shared learning framework and an individualized clinical formulation. Similar-looking checking is insufficient to distinguish the problems: checking whether one has an illness and checking to prevent oneself causing harm can involve different predictions, even when both concern health.
In obsessive-compulsive disorder, obsessions are recurrent intrusive thoughts, images or urges, and compulsions are repeated actions or mental acts intended to neutralize distress or avert a feared outcome. Paul Salkovskis's cognitive analysis located a maintaining problem in the appraisal of intrusive material, particularly inflated responsibility, rather than in the mere occurrence of an unwanted thought. An intrusion can become significant because the person treats having it as evidence of danger or an obligation to act. Covert neutralization matters as well as visible washing or checking. This is a psychological account to test, not a claim that responsibility explains every presentation.[ref]
Obsessional-compulsive problems: A cognitive-behavioural analysis by Paul Salkovskis. 1985; proposed responsibility appraisal and neutralization cycle
Health anxiety centers on perceived illness and the interpretation of bodily changes or health information. The cognitive account proposed by Hilary Warwick and colleagues links threatening illness interpretations to selective attention, anxiety and attempts to obtain certainty. A real sensation can be amplified by monitoring, and the resulting experience can seem to confirm the original interpretation. Medical reassurance may produce temporary relief without changing the underlying rule that uncertainty is intolerable. The target is the meaning and maintaining process, not an assertion that symptoms are imaginary.[ref]
Hypochondriasis by Hilary Warwick and others. 1990; proposed cognitive-behavioral account of development and maintenance
Both formulations predict negative reinforcement. If a ritual or request for reassurance reduces distress immediately, repetition becomes more likely even when the long-term inference is unhelpful. Avoiding a situation can also prevent learning what would happen without the precaution. The functional question is whether the person attributes safety to the behavior and therefore fails to update the feared prediction. Objectively useful precautions and proportionate medical care are different: their function and evidence must be assessed rather than classifying every precaution as pathological.
The differences are clinically consequential. Obsessive-compulsive disorder can involve contamination, accidental harm, morality, symmetry or incompleteness, not just illness. The central concern may be causing harm through responsibility, whereas health anxiety may involve already having a disease that others have missed. Insight varies in both, so an apparently strongly held conviction does not alone establish the distinction. Likewise, unwanted thoughts can occur in health anxiety and reassurance seeking can be a compulsion. Assessment needs the sequence of trigger, interpretation, response and consequence, with comorbidity considered rather than forcing every person into a mutually exclusive category.
For obsessive-compulsive disorder, exposure and response prevention makes the feared cue available while reducing the ritual that prevents informative learning. The aim is to test predictions and develop a different relationship to uncertainty, not simply to maximize distress or demand certainty that harm is impossible. Cognitive work can clarify responsibility assumptions and identify mental rituals that would otherwise remain unnoticed. Outcome measures should assess time, interference and distress as well as the number of visible acts; suppressing one ritual while replacing it with covert neutralization would be an inadequate success criterion.
Edna B. Foa and colleagues' adult randomized trial compared exposure and response prevention, clomipramine, their combination and pill placebo. The exposure-containing conditions provided strong evidence of benefit, with the combination not establishing a clear advantage over exposure and response prevention alone. This supports a treatment package, not proof that one proposed cognitive change is its exclusive active mechanism. Medication effects also need not establish that the disorder is caused by a simple neurotransmitter deficiency.[ref]
Randomized, placebo-controlled trial of exposure and ritual prevention, clomipramine, and their combination in the treatment of obsessive-compulsive disorder by Edna B. Foa and others. 2005; randomized exposure/ritual prevention, clomipramine, combined and placebo conditions
For health anxiety, cognitive behavioral therapy examines competing explanations of symptoms, patterns of attention and the consequences of checking, avoidance and repeated reassurance. Behavioral experiments can compare a threat interpretation with an alternative maintenance explanation. A coordinated medical plan matters because genuine illness and health anxiety can coexist; reducing repetitive certainty seeking does not imply disregarding new clinically relevant information. A collaborative explanation respects the reality of the distress while making the maintenance account open to revision.
Peter Tyrer and colleagues' CHAMP study randomized 444 medical outpatients to adapted cognitive behavioral therapy or standard care. Concurrent physical illness was not an exclusion, and the follow-up report found an advantage in health anxiety symptoms sustained over five years. This strengthens applicability beyond a purely psychiatric clinic. Nevertheless, improvement in the health anxiety outcome did not imply cost-effectiveness on every economic or quality-of-life endpoint, and comparison with standard care does not isolate each treatment component.[ref]
Cognitive-behaviour therapy for health anxiety in medical patients (CHAMP): a randomised controlled trial with outcomes to 5 years by Peter Tyrer and others. 2017; Abstract, eligibility, health anxiety follow-up and economic outcomes
Medication evidence further discourages an absolute psychological-versus-biological division. Brian A. Fallon and colleagues randomized 195 people with hypochondriasis to fluoxetine, cognitive behavioral therapy, both or placebo. Individual active-treatment contrasts against placebo were not significant on the primary responder definition, although secondary continuous analyses favored fluoxetine. Thus it would be misleading either to omit the medication signal or to describe every endpoint as proving superiority. This pattern also illustrates why a positive trial abstract needs to be read alongside its prespecified outcome.[ref]
A randomized controlled trial of medication and cognitive-behavioral therapy for hypochondriasis by Brian A. Fallon and others. 2017; primary responder analysis versus secondary continuous outcomes at 24 weeks
The shared components are collaborative formulation, clarification of predictions, modification of maintaining safety behaviors and evaluation of learning in daily life. Their content differs with the feared catastrophe, timescale and interpretation of responsibility or illness. Treating the functional cycle is more useful than treating checking as a uniform symptom, while diagnosis still helps organize assessment and select evidence-supported options. Neither the overlap nor the treatment response establishes that the two problems are identical, and neither diagnosis removes the need for appropriate assessment of physical health and individual circumstances.
Past exam of the behavioural neuroscience course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 5 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25The hippocampus and perirhinal cortex contribute to an interacting cognitive system with different representational emphases: relations and context for the hippocampus, and integrated object representations and familiarity for perirhinal cortex. This distinction is supported by converging task dissociations, but neither “all memory” nor “memory versus perception” maps neatly onto one anatomical boundary.
Both belong to the medial temporal lobe and interact through entorhinal cortex and other cortical routes. Both participate in experience-dependent changes and recognition performance. Their common location and involvement in declarative memory do not imply identical computations. Conversely, different predominant functions do not require independence: recognizing an object in its prior location requires information about the object and its relations to context.
The hippocampus binds or represents relations among items, places and episodes. Hippocampal place cells provide one spatially selective population code, while episodic remembering requires more than a location signal. A comparison of a familiar object in an unfamiliar setting with the same object in its original setting can place demands on contextual relations even though the item's individual familiarity is unchanged. This makes relational complexity a better prediction than assuming every recognition response is equally hippocampal.
The perirhinal cortex integrates information about objects, including combinations of features, and contributes strongly to item familiarity. A familiar-versus-new distinction can therefore survive some hippocampal damage if a task does not require retrieving the accompanying episode. However, an old/new response can also be solved through recollection, so preserved or impaired recognition memory cannot be assigned to one process solely from the response label. Familiarity is not equivalent to weak confidence, nor recollection simply to a strong familiarity signal; tests need assumptions capable of distinguishing those accounts.
An informative lesion comparison tested rats on a radial maze and a spontaneous object recognition task. Bilateral hippocampal lesions impaired spatial memory, whereas peri-postrhinal lesions impaired object recognition and spared the spatial comparison more effectively. The object task used a restricted Y-shaped apparatus to reduce spatial and contextual information: after inspecting two identical objects, the animal later encountered familiar and novel alternatives. This double dissociation argues against treating the two structures as interchangeable components of a homogeneous store. Importantly, the cortical lesions included postrhinal cortex, so the experiment cannot attribute every effect uniquely to perirhinal cortex.[ref]
Double dissociation between the effects of peri-postrhinal cortex and hippocampal lesions on tests of object recognition and spatial memory by Boyer D. Winters and others. pp. 5901–5908; Methods and Figures 1, 5–6: modified recognition apparatus, radial maze and lesion extent
The interpretation depends on controls. A novel-object exploration preference requires adequate sampling, intact discrimination and motivation, not a verbal report of remembering. Position changes and environmental cues can make an apparently simple object task relational. Conversely, radial-maze performance can use nonspatial cues or learned response strategies unless these are controlled. A double dissociation is stronger than finding one impaired group on a difficult task, but different lesion sizes, task sensitivities and compensatory strategies still matter. Comparing a range of delays and feature overlaps is more informative than claiming an absolute boundary from one condition.
Clinical cases also constrain the comparison. Carefully characterized CA1 damage has produced marked anterograde amnesia, demonstrating an important hippocampal role in human new learning. The original report included minor pathology elsewhere, so its strength comes from the combined behavioural and neuropathological analysis rather than a claim of a perfectly isolated experimental lesion. Broader temporal resections cannot establish hippocampal specificity because they also affect nearby tissue. The severity and breadth of a patient's deficit should therefore be related to the full lesion and functional network, rather than assigned automatically to the most familiar structure.[ref]
A pure memory-system classification also faces perceptual evidence. In trial-unique human object-oddity tasks, all alternatives were displayed together and subjects selected the different object. Patients with broader medial temporal damage including perirhinal cortex were impaired when objects shared many features, but could perform conditions solvable from simple features. Patients with more selective hippocampal damage were relatively spared. This supports a feature-conjunction account of perirhinal cortex: representing complex objects can matter during perception as well as retention. Yet the broader patient lesions prevent assigning every deficit uniquely to one cortical region, and simultaneous display minimizes rather than logically abolishes all memory or attentional demands.[ref]
The human medial temporal lobe processes online representations of complex objects by Morgan D. Barense and others. Abstract and pp. 2963–2974: trial-unique object oddity, feature overlap and patient groups
Representational and process accounts can be complementary. Item familiarity may emerge from experience-dependent changes in integrated object representations; binding an object to its location or temporal setting may require hippocampal relational processing. This predicts dependence on what information a task needs, rather than delay alone. At high feature interference, even immediate object discrimination can require perirhinal cortex; when context is essential, even recognizing a familiar item can require hippocampal participation. These are testable predictions, not a claim that every perceptual difficulty is already explained by one model.
The extended-system account makes an additional comparison: hippocampal interactions with the fornix and anterior thalamic nuclei support event-related remembering, whereas a perirhinal–mediodorsal thalamic system can contribute to familiarity judgments. This is a theoretical synthesis of lesion, recording and related evidence, not itself a new experiment proving strict process purity. Anatomical interaction remains compatible with functional specialization, and the proposed two-process mapping should be challenged by tasks that equate strength while changing contextual demands.[ref]
Episodic memory, amnesia, and the hippocampal-anterior thalamic axis by John P. Aggleton and others. Abstract and pp. 425–444: proposed hippocampal–anterior thalamic and perirhinal–mediodorsal systems
The most useful contrast is consequently relational/contextual representation versus integrated item representation, with corresponding differences in recollection and familiarity. The evidence available in April 2022 supports specialization within an interacting network, while leaving the exact relationship between representations, memory processes and perception open to experimental refinement. Neither structure is a universal memory centre, and neither can be understood adequately from a single task label.
Past exam of the behavioural neuroscience course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 4 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Disruption of an extended hippocampal–diencephalic network explains important forms of amnesia, but a single indispensable serial loop is too strong an account. The distinction is between a useful anatomical network hypothesis and a claim that every connection is equivalent or that all memory failures have the same cause.
The Delay-Brion circuit links temporal-lobe and diencephalic amnesia. Its conventional route runs from the hippocampus through the fornix, mammillary bodies and mammillothalamic tract to the anterior thalamic nuclei, with cingulate and parahippocampal return routes. It overlaps the Papez circuit, originally proposed for emotion, but the historical explanations are not identical. The important question is whether connected structures form a single serial relay or make differentiated contributions within a larger network.
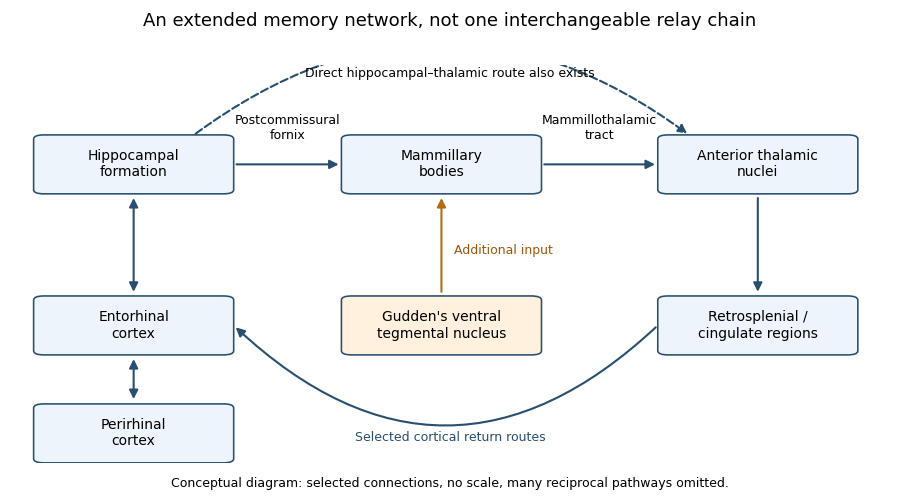
Selected routes in the extended hippocampal memory network
. An original conceptual schematic, not an anatomical atlas or a source figure. The upper chain shows the commonly emphasized mammillary route; the lower arrows show selected additional interactions and an extra-hippocampal input. Arrow presence does not assert equal necessity, and many reciprocal connections are omitted. Details.
The network proposal solves a genuine localization problem. Severe new-learning deficits follow damage in anatomically separated sites, so a theory confined to one small storage centre is inadequate. Clinical surgical cases showed marked anterograde amnesia after bilateral medial temporal resections, despite comparatively preserved intellect and some older knowledge. However, the original operations included neighbouring structures, so those observations cannot isolate the hippocampus from surrounding tissue. A subsequent extensively assessed patient, R.B., had marked new-learning impairment and a bilateral lesion largely confined to hippocampal CA1 at postmortem examination, with minor pathology elsewhere. The case strengthens the hippocampal contribution while illustrating why detailed anatomical verification matters.[ref]
Loss of recent memory after bilateral hippocampal lesions by William Beecher Scoville and Brenda Milner. pp. 11–21: clinical cases and anatomical limitations of the resections
[ref]Human amnesia and the medial temporal region: enduring memory impairment following a bilateral lesion limited to field CA1 of the hippocampus by Stuart Zola-Morgan and others. Abstract and pp. 2950–2967: longitudinal testing, CA1 pathology and minor extra-hippocampal abnormalities
Diencephalic pathology supplies convergent evidence. In a comparative postmortem study of alcohol-related disease, mammillary and mediodorsal thalamic neuronal loss occurred in both amnesic and non-amnesic cases with relevant pathology. Consistent anterior thalamic neuronal loss differentiated the cases with Korsakoff syndrome. Such pathological controls are more informative than observing a damaged mammillary body in one amnesic patient. The findings support an anterior thalamic contribution and caution against identifying mammillary damage alone as a sufficient explanation. They remain observational: co-occurring damage, uncertain premorbid abilities and incomplete measures of connectivity constrain causal localization.[ref]
Degeneration of anterior thalamic nuclei differentiates alcoholics with amnesia by A. Harding and others. Abstract and pp. 141–154: stereological comparisons and differentiating anterior thalamic loss
The strong serial version makes a sharper prediction: interrupting hippocampal input to the mammillary bodies should disrupt the same memory functions as interrupting mammillary output. A direct rat comparison challenged that prediction. Selective interruption of descending postcommissural fornix input had much less effect on the tested spatial tasks than lesions of the mammillothalamic tract or Gudden's ventral tegmental nucleus. The latter two also produced remote activity changes. The mammillary contribution therefore cannot be explained simply as passive transmission of hippocampal output. Additional brainstem inputs are functionally important. These comparisons concern particular spatial tasks and selective pathways, not proof that an intact fornix is irrelevant to all memory.[ref]
Dismantling the Papez circuit for memory in rats by Seralynne D. Vann. Abstract; Results and Discussion: postcommissural-fornix, mammillothalamic and tegmental comparisons
This result favours an interacting network over a chain of interchangeable relays. There are direct hippocampal–thalamic connections, multiple return routes and inputs from outside the traditional loop. A lesion can deprive another region of useful input or coordination without destroying it. Conversely, residual pathways may preserve a task after one disconnection. Therefore structural preservation of a node does not guarantee functional preservation, and a lesion effect does not show that the lost tissue was the final storage site. Reversible perturbations, pathway-specific comparisons and remote physiological measurements can complement permanent-lesion evidence.
The outcome to be explained must also be specified. Anterograde amnesia differs from retrograde amnesia, and impaired episodic memory is not equivalent to losing every skill, immediate span or familiar item. Recognition memory can draw on recollection or familiarity; a task allowing a strong familiarity judgment can be performed without recovery of contextual detail. Broader medial temporal lobe damage can affect both processes, while more selective damage can yield a different profile. Thus the circuit is most plausible as an explanation of particular relational and event-memory impairments, rather than all failures loosely called amnesia.
There are methodological traps on both sides. Human cases give direct clinical relevance but rarely offer randomized, anatomically pure lesions. Animal interventions improve causal control, yet spatial working-memory tasks do not demonstrate the entire human experience of remembering an event. Failure on a task can reflect sensory, motivational or strategic changes, so spared comparison tasks are necessary. Recovery and compensation can obscure an original contribution, while damage to fibres passing through a region can exaggerate the apparent role of its local cells. A convincing account predicts both impaired and spared functions, not merely a lesion location.
By the examination date, the defensible theory was therefore an extended, functionally differentiated hippocampal–diencephalic network. The Delay-Brion circuit remains valuable because it unifies important temporal and diencephalic causes of amnesia. Its explanatory power increases when it accommodates additional inputs, parallel routes and memory-process distinctions, rather than claims that all amnesia follows the breaking of one serial loop.
Past exam of the behavioural neuroscience course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 3 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Learned helplessness links uncontrollability to later failure to act; instrumental learning makes that proposal testable by separating outcome value, action–outcome control and the ability to perform an action. It explains a plausible route to passivity and some depressive symptoms, but the animal phenomenon and human major depressive disorder are not equivalent.
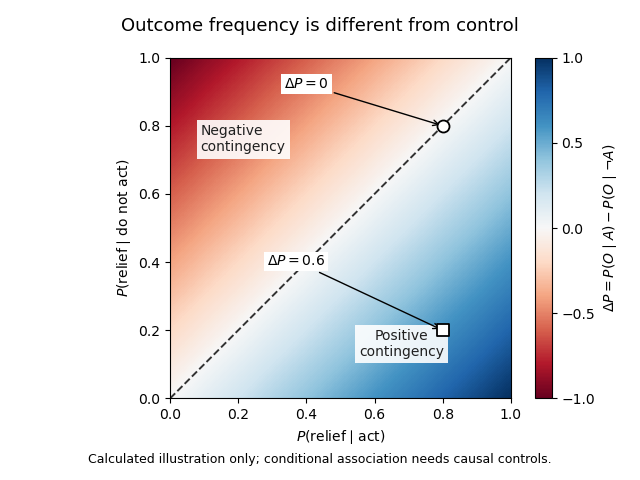
In operant conditioning, an action changes the probability or timing of an outcome. Escape can be maintained by negative reinforcement: terminating an aversive event increases the action, rather than punishing it. A simple description of control is the action-outcome contingencywhere can denote relief and an attempted action. Under genuine controllability this difference can be positive. In an uncontrollable setting it may be zero even when relief sometimes occurs. Outcome frequency and controllability are therefore different. Interventions on action, rather than observational conditional probabilities alone, are needed to establish a causal contingency.
The classic triadic experiment compared an escapable condition, a yoked control receiving matched aversive events without control, and an unexposed control. Initially, a panel response in a harness could terminate the event only for the escapable subject. Later, all groups encountered a shuttle-box task in which crossing a barrier permitted escape. The uncontrollable group subsequently showed greater escape failure, whereas the escapable and unexposed groups learned more normally. Matching the physical events made control, rather than exposure alone, the crucial contrast. The historical experiment used harmful procedures; its conceptual importance is the matched-outcome design, not a protocol to repeat.[ref]
Failure to escape traumatic shock by Martin Seligman and others. Experiment I, pp. 1–4: triadic design, panel control and transfer to shuttle-box escape
The original learned helplessness hypothesis proposed that subjects learn that outcomes are independent of their responses. Generalizing that expectation reduces response initiation, impairs learning of a new contingency, and produces emotional disturbance. The motivational and cognitive effects can reinforce each other: fewer attempts provide less evidence that the new environment is controllable. That feedback offers an explanation for persistent inactivity even when opportunities improve. It does not require assuming that an animal represents a verbal proposition about its future.
For human depression, merely observing uncontrollability cannot explain who develops persistent symptoms or why self-esteem falls. An attributional reformulation distinguishes causes viewed as internal or external, stable or unstable, and global or specific. An internal explanation can undermine self-esteem; a stable explanation extends expectations into the future; a global one extends them across situations. Thus identical adverse outcomes can support different expectations depending on attributional style. These are hypotheses about generalization and vulnerability, not proof that a patient's interpretations caused every symptom or that circumstances are actually controllable.[ref]
Learned helplessness in humans: critique and reformulation by Lyn Y. Abramson and others. pp. 49–74, especially the abstract and reformulation: personal/universal helplessness and attribution dimensions
Subsequent circuit evidence also revises the original learning story. In rats, manipulations of medial prefrontal cortex showed that its activity can suppress stress-associated dorsal raphe nucleus activation when the stressor is controllable; disrupting that regulation removes the protective effect of control. This supports a model in which learning and expressing control actively regulates a stress response. It does not require passivity itself always to be learned as an association. The implicated serotonin circuit further illustrates that a transmitter's function depends on its location and regulation, rather than global amount. Translating these rodent pathways directly into human depressive beliefs would go beyond the evidence.[ref]
Medial prefrontal cortex determines how stressor controllability affects behavior and dorsal raphe nucleus by Jose Amat and others. Abstract and Results, pp. 365–371: prefrontal interventions, controllability and raphe activity
Operant conditioning also distinguishes reduced reward sensitivity from a reduced expectation of control. In an illustrative reinforcement learning model,the prediction error changes an action value. Smaller subjective reward , a different update rate , a pessimistic initial value, or less exploratory choice can each reduce rewarded responding. Increased perceived effort can reduce action even when the expected reward is learned correctly. These are distinguishable candidate mechanisms, not fitted patient results. A low response rate alone cannot identify which parameter changed, and standard chosen-action value learning does not automatically represent causal contingency or attribution.

A human probabilistic reward task supplies a concrete example. Participants discriminated subtly different visual stimuli, with correct responses for one stimulus rewarded more often. Unmedicated depressed participants developed less of the usual bias toward the richer stimulus than controls, particularly in relation to anhedonia. Trial-history analyses indicated a problem integrating reinforcement over time rather than complete insensitivity to a single reward. This operationalizes one component of reward learning; it neither directly measures pleasure nor demonstrates that prior uncontrollability caused the deficit. Sensory discriminability, response bias and learning history must be distinguished.[ref]
Reduced hedonic capacity in major depressive disorder: evidence from a probabilistic reward task by Diego A. Pizzagalli and others. Abstract; Methods 2.2–2.3 and Results: asymmetric reinforcement, signal detection and trial-history analyses
The experimental programme can therefore vary controllability, reward frequency, effort and feedback independently, while measuring acquisition and transfer to new actions. It should include motor and attentional controls and distinguish failure to learn from failure to express learned knowledge. Prospective human data are needed to establish vulnerability rather than consequences of an episode; cross-sectional group differences cannot settle that direction. More opportunities to act are not automatically sufficient when fatigue, threat, external constraints or other symptoms remain.
Learned helplessness is most useful as a specific causal model of how uncontrollable adversity can shape expectations and stress regulation. Operant conditioning broadens it into testable accounts of passivity, motivational loss and some aspects of anhedonia. Neither a single animal task nor one computational parameter explains the entire depressive syndrome.
Past exam of the behavioural neuroscience course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 2 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Monoamine signalling contributes to mood regulation and to the actions of several antidepressants, but a universal “low transmitter causes depression” account is not established. Three propositions must be separated: a drug changes a molecular target; that change helps produce improvement; and the untreated disorder was caused by an opposite abnormality. Evidence for one proposition does not logically establish the next.
The monoamine hypothesis of depression developed from pharmacology. Monoamine oxidase inhibition reduces transmitter metabolism, while some tricyclic antidepressants inhibit transmitter reuptake; SSRI principally inhibit serotonin reuptake. Norepinephrine, serotonin and dopamine are distinct monoamines, acting through different receptors and pathways. The historical catecholamine proposal emphasized norepinephrine and already acknowledged the limitations of extrapolating from drug effects to disease mechanisms. Treating every low affective state as depletion of a single interchangeable brain substance is a substantially stronger claim.[ref]
The catecholamine hypothesis of affective disorders: a review of supporting evidence by Joseph J. Schildkraut. 1965 abstract and pp. 509–522: proposed catecholamine account and explicit limits on pharmacological extrapolation
Drug efficacy supplies evidence that manipulating these systems can matter. A 2018 network meta-analysis synthesized 522 double-blind trials in adults with major depressive disorder and found each included antidepressant more efficacious than placebo on its response outcome. This is evidence synthesis, not a direct assay of patients' transmitter levels. Average effects, trial selection, publication bias, blinding and symptom-scale outcomes limit interpretation, and not every patient benefits. Even a perfectly demonstrated effect would show that an intervention can change a pathological state, not that it reverses its original cause. A downstream compensatory mechanism can be therapeutically useful without being the initiating lesion.[ref]
Comparative efficacy and acceptability of 21 antidepressant drugs for the acute treatment of adults with major depressive disorder by Andrea Cipriani and others. Methods, Findings and Discussion: acute adult trials, response outcome and limitations
Measuring the proposed deficiency is itself difficult. Peripheral serotonin is not a direct measurement of release at a particular central synapse. Metabolites combine synthesis, release, reuptake and degradation; receptor or transporter imaging is not simply a concentration gauge. A difference observed after illness onset might be causal, compensatory, treatment-related or associated with physiological stress. Establishing a general deficiency would require convergent measures in appropriate untreated populations, temporal precedence and a relationship to well-defined symptoms, not merely one group-average biomarker.
Precursor depletion supplies a more informative intervention. In a double-blind crossover study, patients in antidepressant-induced remission underwent acute tryptophan depletion and a control condition. Fourteen of 21 experienced a transient depressive relapse after depletion, whereas control testing did not produce significant behavioural effects. This supports dependence of some maintained remissions on serotonin precursor availability. It does not show that all untreated depressed patients began with low serotonin, that depletion is sufficient to generate the full syndrome in everyone, or that norepinephrine and dopamine are irrelevant. The selected, previously treated sample is central to the causal question actually tested.[ref]
Serotonin function and the mechanism of antidepressant action by Pedro L. Delgado and others. Abstract and pp. 411–418: remitted sample, crossover control and 14/21 transient relapses
Time course also challenges a simple replenishment story. Initial transporter inhibition can occur before substantial clinical improvement. That discrepancy motivates slower receptor, circuit, learning and plasticity changes; it does not imply that early drug effects are absent. In a randomized placebo-controlled experiment, an acute dose of a norepinephrine reuptake inhibitor changed positive emotional processing in depressed participants before subjective mood or anxiety changed. Facial-expression judgments and emotionally valenced categorization and recall supplied behavioural readouts. These observations support an affective processing bias account: altered experience processing could accumulate into mood change. They do not establish that the measured early shift mediates every later clinical response.[ref]
Effect of acute antidepressant administration on negative affective bias in depressed patients by Catherine J. Harmer and others. Abstract; Methods and Results, pp. 1178–1184: randomized emotional-processing battery before mood change
Plasticity offers another candidate bridge between early pharmacology and delayed behaviour. In mice, preventing antidepressant-associated adult hippocampal neurogenesis blocked behavioural effects in particular experimental assays. The evidence included genetic and localized irradiation approaches. It supplies a mechanistic dependency within that model, rather than merely a correlation between a drug and cell proliferation. However, the assays are not human major depressive disorder, the interventions can have additional effects, and necessity for one behavioural endpoint does not establish either sufficiency or a universal human mechanism.[ref]
Requirement of hippocampal neurogenesis for the behavioral effects of antidepressants by Luca Santarelli and others. Abstract and pp. 805–809: interference with neurogenesis and model-specific behavioural effects
These alternatives refine rather than simply discard monoaminergic pharmacology. Serotonin or norepinephrine could regulate plasticity and learning within distributed neural circuits; baseline concentrations need not be uniformly low. Receptor sensitivity, pathway-specific activity and environmental experience could determine the effect of an intervention. Conversely, observing altered dopamine-related motivation would not prove that all anhedonia, cognitive slowing and sadness have one cause. Major depressive disorder groups multiple symptom patterns, so a mechanism associated with one dimension can be diluted or misleading when treated as a universal disease explanation.
The strongest conclusion available at the examination date is therefore conditional. Particular monoamine manipulations can alter affective processing and symptoms, and some treatment responses depend on monoaminergic function. The evidence does not identify a single brain-wide deficit that is necessary and sufficient for human depression. A useful successor account specifies transmitter, receptor, circuit, time scale and symptom, and tests how biological changes interact with learning and environment. This evaluation concerns explanatory evidence, not a recommendation to start, stop or choose a medication.
Past exam of the behavioural neuroscience course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 1 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Sleep can protect newly acquired information, actively reorganize it, and restore the capacity for subsequent learning. These are distinct claims. Memory consolidation concerns changes after acquisition; better learning the next morning concerns encoding capacity; less interference during an unoccupied interval need not imply an active sleep mechanism. The strongest explanation therefore combines behavioural comparisons with recordings and selective interventions.
A basic retention experiment compares later performance after sleep and waking, ideally relative to an immediate baseline. Yet a night-versus-day comparison also changes circadian phase, interference and alertness at testing. Sleep deprivation adds physiological stress and attentional impairment. Matching acquisition, testing at comparable times, measuring vigilance, and comparing sleep with quiet waking make the inference sharper. A retention advantage after sleep remains compatible with both passive protection and active processing; distinguishing them requires manipulating what happens during the interval.
The active systems consolidation hypothesis provides an active mechanism. Rapid relational encoding by the hippocampus permits later memory reactivation to modify distributed cerebral cortex representations. During NREM sleep, cortical sleep slow oscillations can organize sleep spindles and hippocampal sharp-wave ripples, creating coordinated windows for synaptic plasticity. This is a timing hypothesis about communication, not proof that a complete memory is copied from one anatomical container to another. Systems consolidation and synaptic consolidation can proceed together, and some detailed episodic memories may continue to require hippocampal contributions.
An important recording experiment monitored ensembles of hippocampal place cells in rats during spatial behaviour and during sleep before and after it. Cells active together at particular locations became more likely to fire together in subsequent slow-wave sleep; the pre-experience recording supplied a valuable baseline. This demonstrates experience-related memory reactivation. Pairwise coactivation alone does not establish ordered neural replay, nor does a correlation show that the events improve retention. An apparently memory-related pattern might otherwise be an incidental consequence of prior activity.[ref]
Reactivation of hippocampal ensemble memories during sleep by Matthew A. Wilson and others. Abstract and pp. 676–679: simultaneous ensemble recordings and pre-/post-experience comparison
A stronger causal test interrupted hippocampal sharp-wave ripples during post-training sleep in rats learning a spatial task. An online electrical recording system detected ripple events and triggered brief disruption; a delayed-stimulation comparison helped control stimulation without abolishing the same events. Spatial performance was impaired, while gross sleep architecture was not detectably changed. This supports a functional role for ripple-associated activity beyond simply obtaining sleep. Nevertheless, disruption affects an event and its associated activity, not an experimentally isolated memory message; it does not identify the exact information transferred or establish that all memory consolidation requires the same mechanism.[ref]
Selective suppression of hippocampal ripples impairs spatial memory by Gabrielle Girardeau and others. pp. 1222–1223; Figures 1–2: event-triggered disruption, delayed control and behaviour
Human targeted memory reactivation offers complementary evidence. Participants learned object locations with an odour present, then received that odour again during polysomnographically identified slow-wave sleep. Retention improved compared with an odourless condition. Crucially, the benefit did not appear when the odour had been absent during learning, or when it was presented during waking or REM sleep; procedural finger-tapping did not show the same benefit. The cue–learning relationship and sleep state therefore mattered. The associated hippocampal activation is consistent with memory reactivation, although activation does not reveal all the represented content. This is stronger evidence for selective processing than an undifferentiated sleep/wake advantage.[ref]
Odor cues during slow-wave sleep prompt declarative memory consolidation by Björn Rasch and others. pp. 1426–1429; experiments I–IV: object-location learning, unpaired odour and sleep-state controls
Sleep could also benefit memory by regulating the substrate for learning. The synaptic homeostasis hypothesis proposes that predominantly waking-associated strengthening requires compensatory renormalization, limiting saturation, energy costs and interference. Selective preservation can improve the contrast of important connections even if average strength of synapses falls. Serial electron-microscopy reconstructions of mouse cortical synapses found smaller axon–spine interfaces after sleep, with an average decrease of roughly 18%; the largest synapses were relatively spared. The comparison included spontaneous and enforced waking. These are structural measurements consistent with selective scaling, not a direct measurement of every synapse's efficacy or proof that the measured changes caused a particular memory benefit.[ref]
Synaptic scaling across waking and sleep by Luisa de Vivo and others. pp. 507–510; Figures 1–3: three-dimensional reconstructions and size-dependent changes
Renormalization and selective strengthening are not mutually exclusive. A learning-related ensemble could be selectively stabilized while less useful background connections weaken. Memory reactivation could help select what survives, and improved capacity after sleep could support the next episode rather than merely preserve the last one. An adequate theory must explain both specificity and restoration, rather than equate more firing or larger synapses with better memory everywhere.
The interpretation must remain task-specific. A cueing effect for declarative memory does not assign every procedural memory to REM sleep, and a null cueing result in one stage does not show that stage has no mnemonic function. Sleep-stage manipulations can alter other stages or awaken subjects. Rodent spatial performance provides mechanistic access but does not by itself establish human autobiographical experience. Replicated behavioural effects, adequate controls and selective circuit perturbations are most persuasive when they converge.
Thus sleep is important because it provides a state in which information can be selectively re-expressed and reorganized while conditions at synapses are regulated. Evidence available by April 2022 supports active contributions in addition to passive protection; it does not establish a universal sleep-only route for every kind of learning.
There are unlisted articles, also show them or only show them.