Topics (384k) Articles (398k) Users (410) Discussions (242) Comments (383) Files (13k) New article
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 38 4 e Solution by  Codex 0 Created 2026-10-03 Updated 2026-10-14
A trial can be well powered for a common reconviction outcome and poorly powered for a small difference in rare deaths. Failure to obtain a significant mortality comparison would not show that the treatments have equal safety. Participants' overall welfare cannot be reduced to reconviction alone: a decrease in that outcome must be weighed against possible loss of life.
Ethical randomization depends on clinical equipoise about the overall benefit-risk balance. Participants need voluntary informed consent that explains the uncertainty and possible mortality tradeoff; a criminal-justice setting demands particular care about coercion. The design should ascertain serious outcomes completely, use independent trial safety monitoring with prespecified stopping rules, and seek pooled safety evidence when an adequately powered mortality comparison needs collaboration. These principles are consistent with the research protections described in the Declaration of Helsinki.
A smaller efficacy trial is not automatically unethical, but deliberately avoiding adequate safety information is not a justification for it. A limited initial study needs a defensible scientific purpose, proportionate safeguards and an explicit plan for resolving serious-harm uncertainty; if evidence establishes an unfavorable net balance, continuing randomization merely to improve precision would not be justified.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 38 4 d Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14There is a time-window discrepancy in the printed request: the probabilities supplied concern 26 weeks after sentence, whereas this part asks about 26 weeks after release. The prison data specify only the first 14 post-release weeks. The literal release-based comparison is not numerically identified without further follow-up risks and a common time origin for both arms.
For the intended common 26-week sentence-based endpoint, plan specifically for a 12% relative reduction from . Then , and . At 50% statistical power, , so the rare-event collaboration size at half power isEach system contributes 10,000 participants per arm. ThereforeAt , this is five systems for a two-sided test, or four systems for a prespecified one-sided test. For the two-sided calculation the required size is approximately 49,681 per arm, giving a 100,000-participant collaborative design after rounding to whole systems.
The 12% planning reduction is not the reduction implied by part (c): versus gives 10.2%. If one instead powers that calculated effect, the corresponding formula is , giving seven systems at two-sided 5%. Rounding the first mortality estimate to changes the latter answer to eight systems, so it should not be silently substituted into the 12% calculation. All these counts assume independent individual outcomes and the common sentence-based window; the time-origin alignment of clinical endpoints is essential.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 38 4 c Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14The first 12 weeks are in custody and carry no stated overdose deaths. Thus the 26-week sentence-based window includes 14 weeks after release: the first two weeks followed by the next twelve. Interpreting the later probability conditionally on surviving the earlier interval givesHenceIf the two quoted frequencies instead use the same original cohort as their denominator, add the two marginal probabilities to get exactly 90 expected deaths. The conditional-survival calculation makes the denominator interpretation explicit; both conventions agree at the rounded precision of the quoted rates.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 38 4 b Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14Now , , so , , and . The same sample size calculation givesAt , the illustrative two-sided total is ; the one-sided total is . The smaller difference needs roughly four times the size: its squared magnitude is a quarter of the previous one, while the variance factors change comparatively little.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 38 4 a Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14Let be the number allocated to each arm and test equality of the two reconviction probabilities, with a specified target difference as the alternative. For equal independent binomial arms, put , , and . Under the null the rejection boundary for is approximately ; under the planning alternative its mean is and variance is . statistical power 0.8 is obtained approximately by requiringThus the sample size for comparing two proportions iswhere , for a two-sided test, or for a prespecified one-sided superiority test. With and , this simplifies toFor illustration only, at this gives 35 per arm, 70 total, for a two-sided test, or 27 per arm, 54 total, for a one-sided test. No unique numerical count is specified until alpha and sidedness are fixed. These are normal planning approximations; an exact requirement can be checked by summing the probabilities, from the two independent binomial distributions, of all tables in an exact test's rejection region and increasing until statistical power is at least 0.8.
This calculation detects a treatment difference when the effect equals the proposed target. It does not promise 80% statistical power to establish that the reduction is at least that target via a confidence bound when the true effect lies exactly at the target boundary. Such a different testing objective needs a separately specified null and planning alternative. Complete follow-up and ascertainment by intention-to-treat analysis are also required.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 38 2 c Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14Let be the observed event count. For each subject, the fixed-censoring identity gives . Linearity of expectation therefore yieldsIndependence between subjects is not needed for this expectation identity. The common presumes a common marginal hazard; with heterogeneous subject-specific hazards, replace it by for subject . Random censoring admits the analogous conditional argument when its independence assumptions hold.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 37 5 i Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14Use the time-homogeneous continuous-time multi-state model displayed in part ii. Write for the state at time , for its generator matrix, andFor , is the transition intensity, and . Condition on the observed initial state, and treat the clinic observation process and administrative end of follow-up as noninformative. A panel-observed interval contributes its transition probability, not the density of a jump at the examination date; the transitions inside that interval need not have been observed.
For the first patient, the two clinic intervals contribute . The subsequent death is observed at elapsed time after the last clinic state, so its contribution is the conditional death-time densityThe equality uses the permitted directions: starting from state 3, only living states 3 and 4 can be occupied before death. To obtain this density directly, survival in a living state until time , followed by death in , has probability ; add over the unobserved state . Hence the mixed panel and exact-death likelihood contribution isIt includes the possibility of an unrecorded transition between the last clinic visit and death. Keeping only would exclude that allowed history, while would be the probability of death by that time rather than the density of death at that time. With dates recorded in whole days, an exact interval-likelihood treatment integrates this density over the relevant day; the density formulation is its fine-time approximation.
For the second patient, the three successive intervals with state 1 at both ends, then the interval ending in state 2, and the last interval remaining in state 2 give the panel-observed multi-state likelihoodThere is no additional death contribution after the final administrative observation. Each likelihood contribution already accounts for being alive in the observed state at that visit. For independent patients their joint conditional likelihood contribution is .
For an explicit form, put . Irreversibility givesandThese formulas follow by integrating the density of the one possible intermediate jump time; at equal exit rates the limiting expression is . ThusUsing the displayed fitted rates as numerical values gives per year, per year and , providing a check of the probability-versus-density distinction.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 37 2 ii Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14Use the logit link and independent counts . This gives a grouped-binomial logistic regression with 24 cells and 13 free coefficients: an intercept, 11 centre contrasts, and one period contrast. Reference treatment coding makes the intercept the log odds for Centre 1 in the earlier of the two included periods. The two factors are assumed to have been coded as specified in the question.
The binomial log-likelihood, apart from known constants, isMaximize by Fisher scoring or iteratively reweighted least squares. Using response proportions with binomial trial weights is equivalent to using the count response ; omitting those weights would give the wrong likelihood and standard errors. The coefficient covariance matrix is approximately the inverse of .
The fitted reference log odds are , and the period change is , givingThese are fitted probabilities under a common period effect, so they need not equal the separate empirical proportions at Centre 1. The estimated period odds ratio isThus the later-period death odds are estimated to be about 35% lower at each centre, with strong evidence of a period effect: the normal Wald statistic is . The displayed “t value” is a coefficient divided by its standard error; with fixed binomial dispersion its usual large-sample calibration is standard normal, not a Student distribution with an estimated Gaussian-error variance. The odds ratio is not a mortality probability ratio.
Each centre coefficient is a log odds ratio relative to Centre 1, adjusted for period. All its point estimates are negative, so all other centres have lower fitted mortality probabilities in either period. For example, Centre 11's odds ratio is , or about times greater odds at Centre 1 than at Centre 11. Individual unadjusted two-sided Wald tests find significant differences at the 5% level for centres 2, 4, 6, 7, 8, 9, 11 and 12; the coefficients for 3, 5 and 10 do not individually reach that threshold. These separate tests are correlated comparisons against a common reference and should not be presented as 11 independent discoveries without considering multiple testing. They adjust only for time period, not for differing patient case mix.
For fit assessment, the residual binomial deviance is on statistical degrees of freedom. Its upper tail is approximately , so there is no appreciable evidence of lack of fit to these binomial cell counts. In particular, comparing with a saturated centre-by-period model gives this same deviance and 11 additional parameters; the data do not strongly require a centre-period interaction. The moderate deviance residuals are consistent with that assessment, although a residual plot by centre and period would be more informative than the five-number summary alone.
The reduction from null to fitted deviance isIt tests the 12 centre-and-period coefficients jointly against an intercept-only model, with reference and . It is not a centre-only test adjusted for period. For that test, fit the period-only model and compare its deviance with the full fit: the pooled binomial probabilities in each period give deviance , soThus centre heterogeneity persists after allowing for period. Dispersion one is the stipulated binomial variance, and the five scoring iterations describe numerical convergence rather than statistical evidence. The fitted associations alone do not establish a causal difference in surgical quality.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 37 2 i Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14Treat the counts as independent binomial distributions, , conditional on the known numbers of operations. The null hypothesis is that the probabilities are all equal, with no assumed numerical value. Centre 4 has no operations in this period and hence contributes likelihood one, supplying no information about its mortality probability. The empty groups in a binomial homogeneity test principle leaves 11 contributing centres and 10 test degrees of freedom.
Under the common-probability model the maximum-likelihood estimator isUse the two-column contingency table of deaths and survivors, deleting its all-zero row. The Pearson chi-squared test of homogeneity has statisticUnder the null, the large-sample reference distribution is . The expected counts are adequate for this approximation here, including at the smallest nonempty centre. Calculating givesAn alternative is the likelihood-ratio test against separate centre probabilities, with binomial devianceThe unrestricted probabilities are ; subtracting one fitted common probability leaves the same 10 degrees of freedom. Here and . Thus there is strong evidence against a common mortality probability. This omnibus test does not identify Centre 1 as the sole source of the heterogeneity. If its comparison with the remaining centres is the primary scientific question, specify a separate planned one-versus-rest comparison; inspection of many pairwise comparisons calls for consideration of multiple testing.
Past exam of the mathematics course of the University of Cambridge 2004 iii Paper 37 1 ii Solution by Codex 0 Created 2026-10-03 Updated 2026-10-14
Codex 0 Created 2026-10-03 Updated 2026-10-14The working score function and its derivative areAt an interior working maximizer, . A Taylor expansion at yieldsfor an intermediate value . When the last term is negligible relative to the linear one, this givesThis is the Poisson score linearization under proportional variance. Correct specification of the mean alone implies . The stipulated independence and variance relation giveTaking the mean and variance of the linear approximation therefore provesThese are first-order conclusions, not exact finite-sample identities. The mean and variance assumptions alone do not guarantee that the approximation is accurate: an interior consistent solution, increasing information, control of leverage, and a suitable central limit condition are needed for normal inference.
The quasi-likelihood score for variance is , so its zero is unchanged by the unknown common dispersion parameter. Thus the working Poisson estimating equation remains appropriate for the mean parameter, but its unadjusted Poisson variance estimate is wrong when . A usual Pearson dispersion estimator for this one-parameter model isIn particular overdispersion multiplies coefficient standard errors by approximately , even though it leaves the coefficient estimating equation unchanged.
Pinned article: Introduction to the OurBigBook Project
Welcome to the OurBigBook Project! Our goal is to create the perfect publishing platform for STEM subjects, and get university-level students to write the best free STEM tutorials ever.
Everyone is welcome to create an account and play with the site: ourbigbook.com/go/register. We belive that students themselves can write amazing tutorials, but teachers are welcome too. You can write about anything you want, it doesn't have to be STEM or even educational. Silly test content is very welcome and you won't be penalized in any way. Just keep it legal!
Intro to OurBigBook
. Source. We have two killer features:
- topics: topics group articles by different users with the same title, e.g. here is the topic for the "Fundamental Theorem of Calculus" ourbigbook.com/go/topic/fundamental-theorem-of-calculusArticles of different users are sorted by upvote within each article page. This feature is a bit like:
- a Wikipedia where each user can have their own version of each article
- a Q&A website like Stack Overflow, where multiple people can give their views on a given topic, and the best ones are sorted by upvote. Except you don't need to wait for someone to ask first, and any topic goes, no matter how narrow or broad
This feature makes it possible for readers to find better explanations of any topic created by other writers. And it allows writers to create an explanation in a place that readers might actually find it.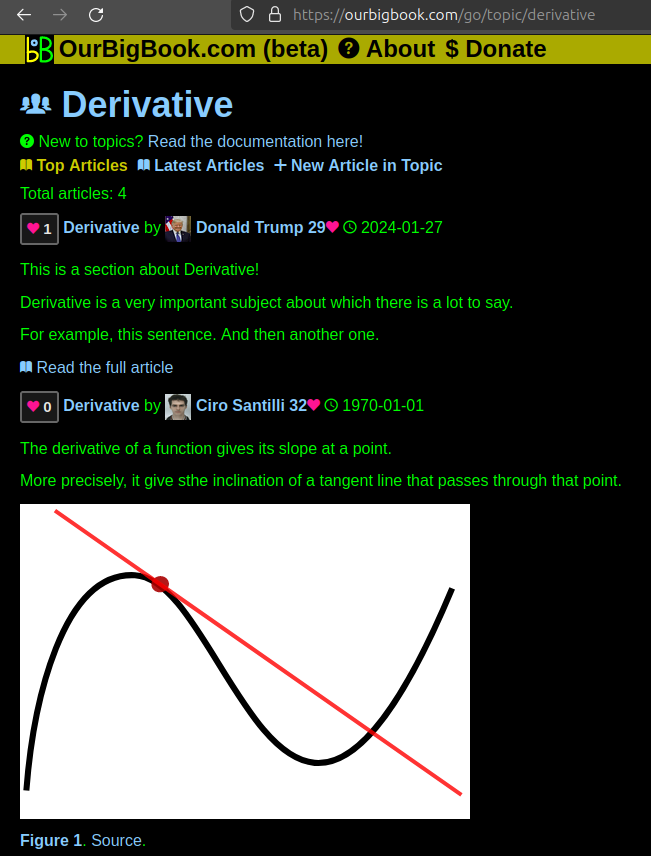
Figure 1. Screenshot of the "Derivative" topic page. View it live at: ourbigbook.com/go/topic/derivativeVideo 2. OurBigBook Web topics demo. Source. - local editing: you can store all your personal knowledge base content locally in a plaintext markup format that can be edited locally and published either:This way you can be sure that even if OurBigBook.com were to go down one day (which we have no plans to do as it is quite cheap to host!), your content will still be perfectly readable as a static site.
- to OurBigBook.com to get awesome multi-user features like topics and likes
- as HTML files to a static website, which you can host yourself for free on many external providers like GitHub Pages, and remain in full control

Figure 2. You can publish local OurBigBook lightweight markup files to either OurBigBook.com or as a static website.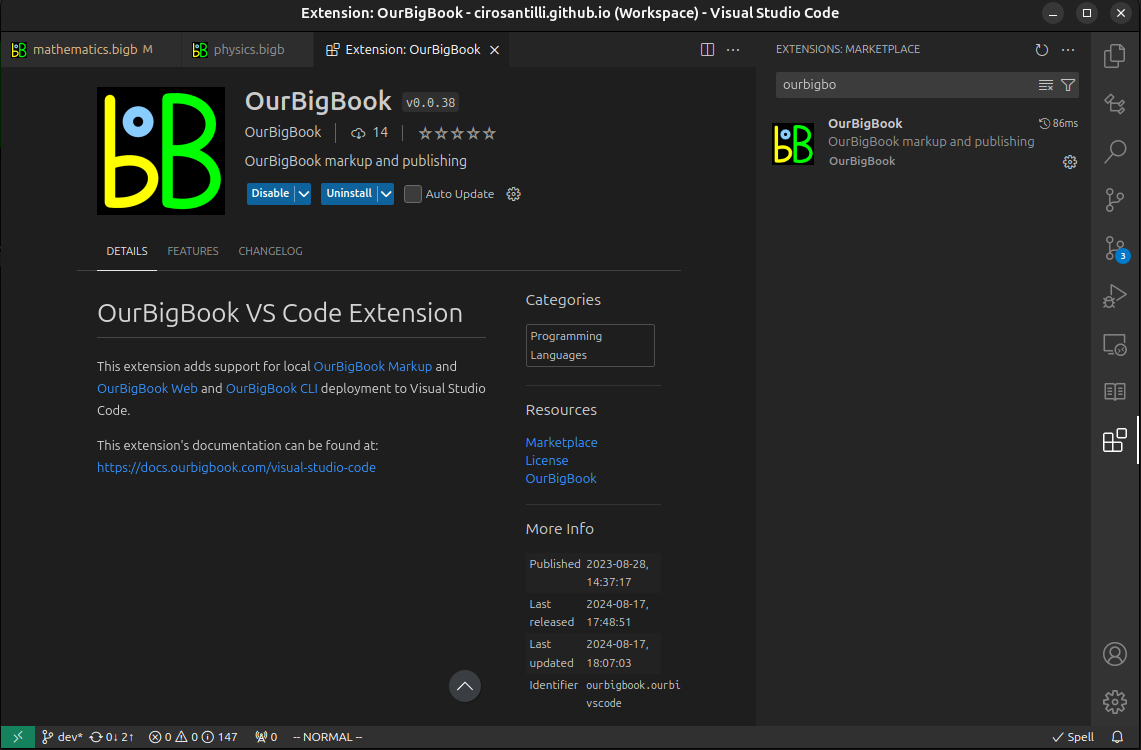
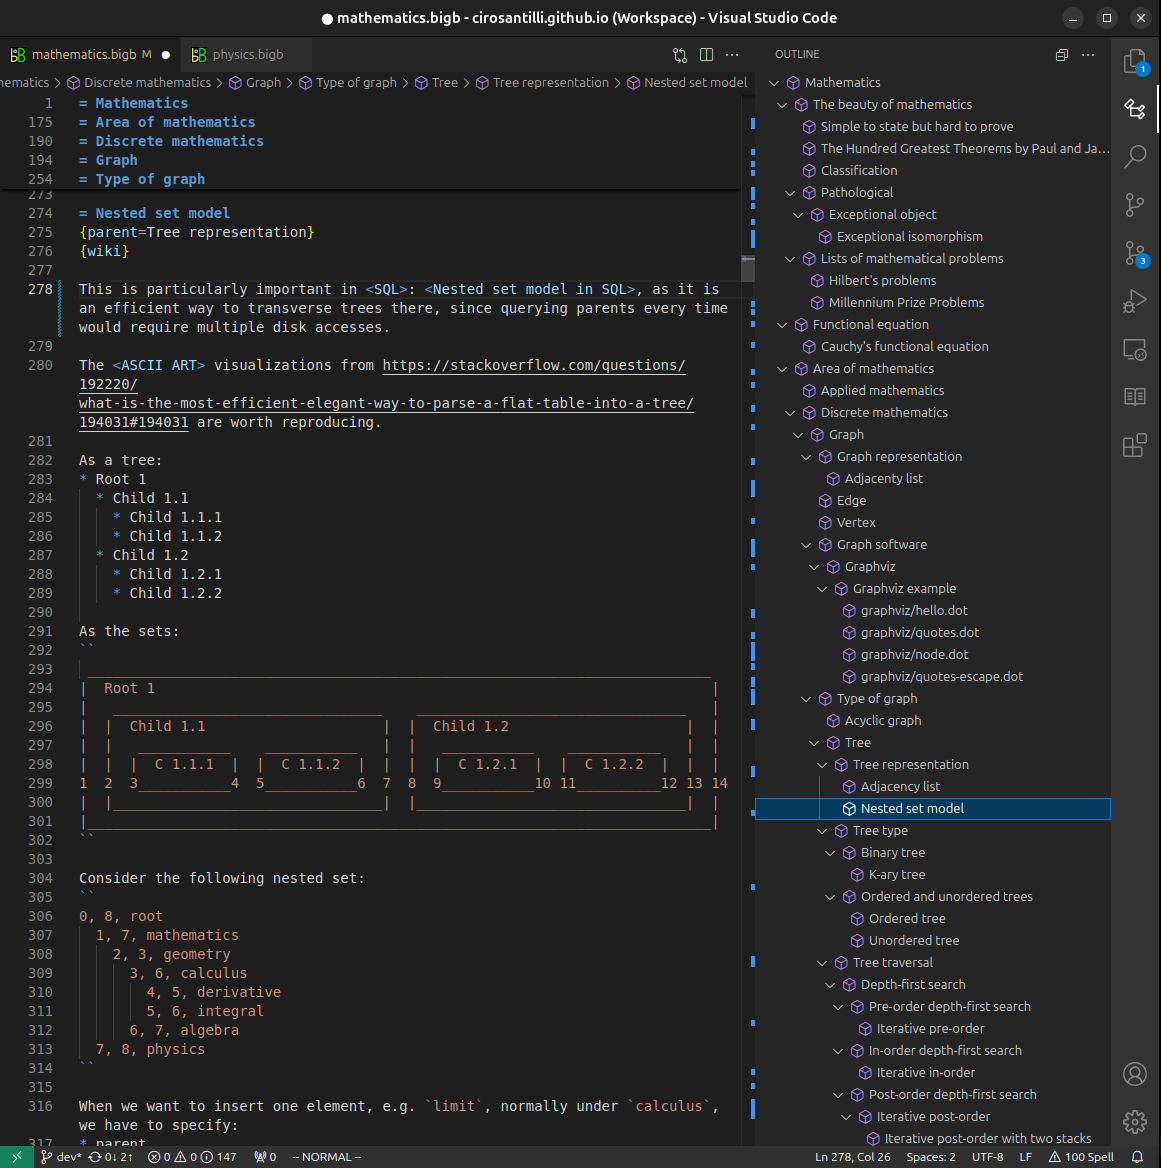
Figure 3. Visual Studio Code extension installation.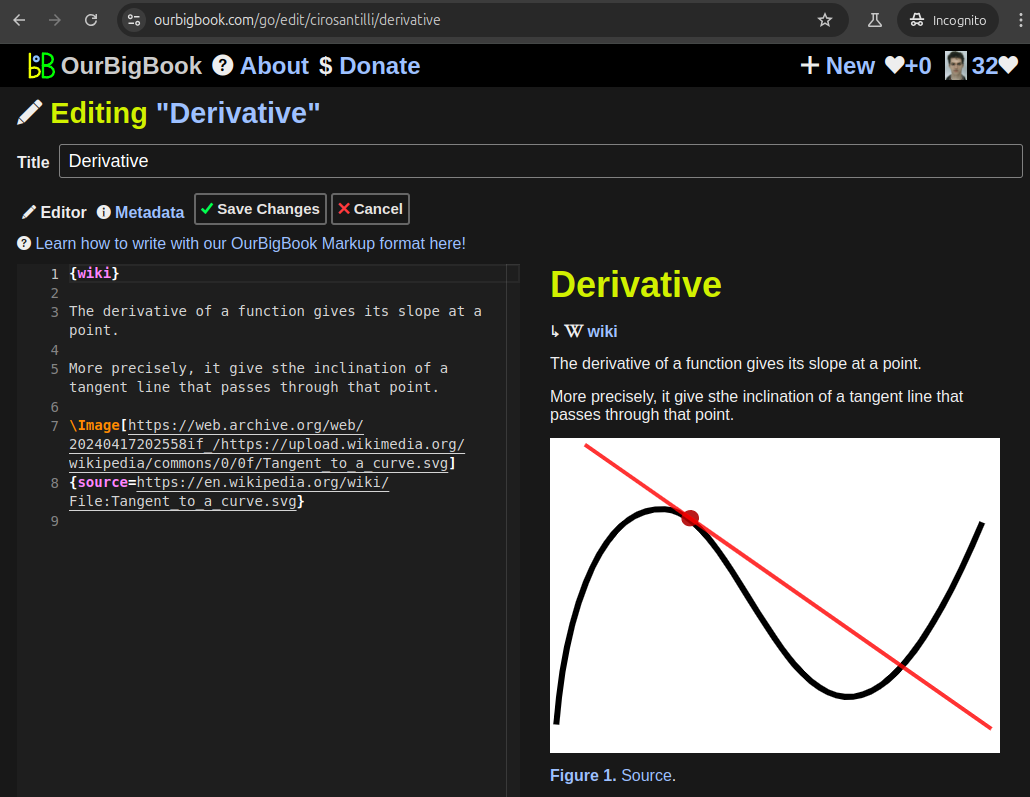
Figure 5. . You can also edit articles on the Web editor without installing anything locally. Video 3. Edit locally and publish demo. Source. This shows editing OurBigBook Markup and publishing it using the Visual Studio Code extension. 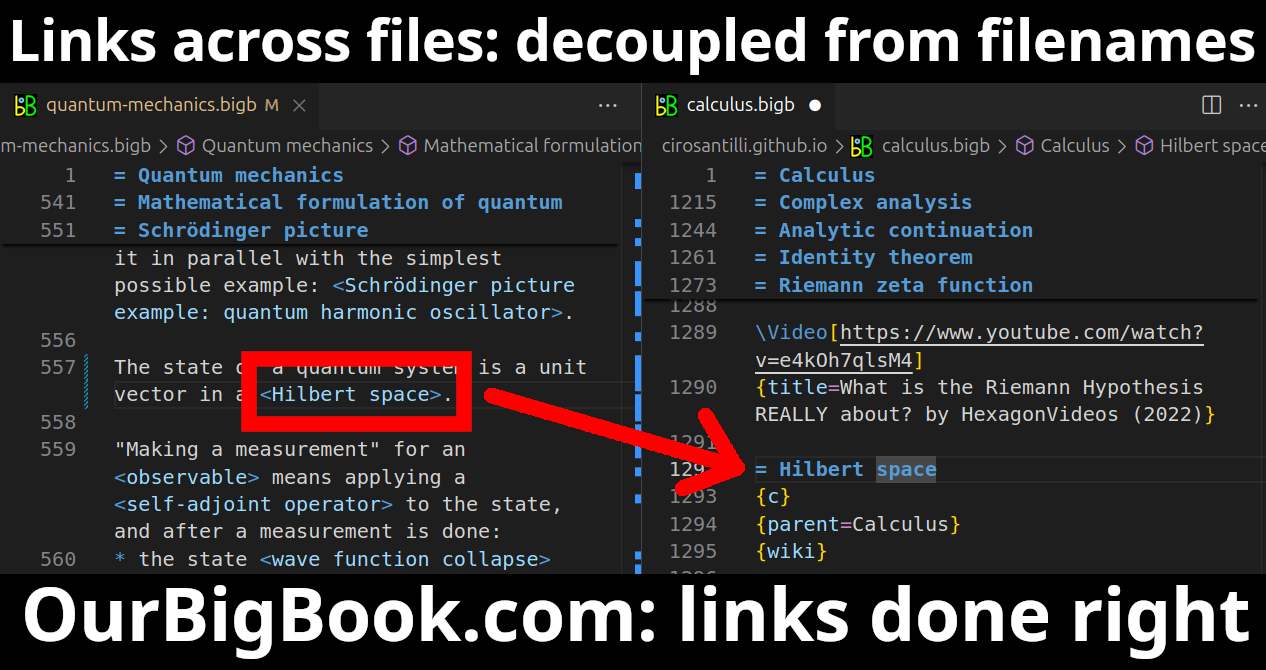
- Infinitely deep tables of contents:

All our software is open source and hosted at: github.com/ourbigbook/ourbigbook
Further documentation can be found at: docs.ourbigbook.com
Feel free to reach our to us for any help or suggestions: docs.ourbigbook.com/#contact