Past exam of the developmental science course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 3 Solution by  Codex 0 2026-10-25
Greater transparency and reproducibility have changed developmental psychology's estimates, measurement practices and theoretical confidence, but have not simply replaced a collection of “true” findings with “false” ones. Computational reproducibility asks whether the same data and documented analysis yield the same result. Scientific replication asks what happens with new observations. Preregistration makes planned tests distinguishable from exploratory choices; open materials permit checking whether ostensibly similar studies actually use the same procedure. None of these, by itself, guarantees construct validity or representative sampling.
The marshmallow task illustrates a substantive change in interpretation. Walter Mischel's early experiments offered preschoolers a smaller immediate reward or a preferred delayed reward and manipulated how attention was directed during waiting. Distraction increased delay. The original experimental programme therefore already showed sensitivity to cognitive strategy and setting, rather than a fixed quantity of virtue revealed by a treat. Later predictive associations are a different claim from those immediate experimental effects.[ref]
Cognitive and attentional mechanisms in delay of gratification by Walter Mischel and others. Journal of Personality and Social Psychology 21, 204–218; experimental manipulations of attention during waiting
Tyler W. Watts and colleagues revisited long-term prediction in a larger and more diverse cohort. Their 2018 conceptual replication used a waiting task at fifty-four months and adolescent achievement outcomes. Associations were substantially reduced after adjustment for family background, early cognitive abilities and the home environment; much of the achievement difference was concentrated at the lowest waiting times. An important measurement difference was the seven-minute ceiling, rather than treating all waiting tasks as interchangeable. These results weaken a simple causal story in which training a preschooler to wait longer should, by itself, transform later attainment. They do not show that self-regulation never matters, because adjustment can remove both confounding and potentially meaningful pathways.[ref]
Revisiting the marshmallow test by Tyler W. Watts and others. Psychological Science 29, 1159–1177; Delay of gratification measure, adjusted models and measurement limitations
Celeste Kidd and colleagues supplied experimental evidence for one alternative mechanism: environmental reliability. Before the waiting task, children encountered an adult who either fulfilled or failed promises about appealing materials. Children subsequently waited longer after reliable experiences. The observation matters because apparent “poor self-control” can be an understandable response to expecting that a promised reward will not arrive. This small experiment supports contextual causation under its own conditions, not a claim that all socioeconomic differences in waiting are caused by trust. Together, the studies shift the target from an isolated child trait to the interaction between control, expectations and circumstances.[ref]
Rational snacking by Celeste Kidd and others. Cognition 126, 109–114; reliable versus unreliable experimenter manipulation
Neonatal imitation illustrates why replicability also depends on the inferential contrast. Andrew N. Meltzoff and M. Keith Moore's 1977 report described very young infants matching facial and manual gestures. In this paradigm an adult models an action and infant responses are recorded and coded; the crucial question is whether the infant produces a given action preferentially after its matching model, not merely whether the action occurs. An increase in tongue protrusion after interesting stimulation is insufficient unless appropriate nonmatching controls exclude general arousal or exploration.[ref]
Imitation of facial and manual gestures by human neonates by Andrew N. Meltzoff and M. Keith Moore. Science 198, 75–78; modelled facial/manual actions and coded infant responses
Janine Oostenbroek and colleagues tested 106 infants longitudinally with nine social and two nonsocial models at one, three, six and nine weeks. Their broad comparisons did not support model-specific imitation, although restricted cross-sections could resemble earlier positive findings. This challenged a general innate-imitation account and highlighted the consequences of selecting particular gestures, ages and contrasts after observing results. Yet the study's breadth also created substantive questions about fatigue, presentation and how each action was scored.[ref]
Comprehensive longitudinal study challenges the existence of neonatal imitation in humans by Janine Oostenbroek and others. Current Biology 26, 1334–1338; nine social and two nonsocial models across four ages
The subsequent requested-data reanalysis by Meltzoff and colleagues reported tongue-protrusion matching under pooled-control contrasts and criticised features of the elicitation and scoring procedures. That was not an independent replication: it reused the same observations. It nevertheless shows the scientific value of access to raw data. The disagreement became one about estimands, comparison sets and measurement sensitivity that another preregistered experiment could adjudicate, rather than an unsupported declaration that one team must be wrong. Evidence for one gesture would also not automatically vindicate a broad, domain-specific imitation mechanism.[ref]
Re-examination of Oostenbroek et al. (2016): evidence for neonatal imitation of tongue protrusion by Andrew N. Meltzoff and others. Developmental Science 21, e12609; requested raw data, pooled-control tongue-protrusion analyses and design criticisms
ManyBabies 1 provides a constructive counterexample to the notion that open developmental research only dismantles effects. In a Registered report, an international collaboration used common speech stimuli and prespecified analyses to test infant-directed versus adult-directed speech preferences. The final sample included 2,329 infants from 67 laboratories. A preference for infant-directed speech survived, while its magnitude varied with age, language experience and measurement method. Laboratories used central fixation, head-turn preference or eye tracking procedures, making methodological variability an object of analysis. The result supports a reproducible average preference without treating the same effect size as universal for every infant or cultural setting.[ref]
Quantifying sources of variability in infancy research using the infant-directed-speech preference by The ManyBabies Consortium. Advances in Methods and Practices in Psychological Science 3, 24–52; Participants, preregistered analyses and Discussion
Several changes to our understanding follow. First, an established group-level tendency can coexist with weak prediction for an individual child. Secondly, stimulus choice, stopping rules, exclusions and coding decisions can change what has actually been measured. Thirdly, heterogeneous outcomes can identify theoretically useful boundary conditions, but a moderator discovered after a failure needs a new test rather than serving as an unlimited excuse. Finally, openly available null results reduce selective visibility of successful studies, improving the evidential base used to build developmental accounts.
The causal claim about reform itself should remain modest. Larger samples, broader recruitment and better controls often accompany transparency, so a change in an estimate cannot be attributed uniquely to preregistration. A perfectly reproducible analysis can reproduce a biased model, and an underpowered replication may be inconclusive. Reliability and measurement equivalence are especially important for looking-time and single-trial child tasks; independent coding and predefined exclusion rules help, but do not establish the intended psychological construct. Open child data also require appropriate consent and controlled access where identification is possible; useful transparency need not mean publishing recognisable videos.
By 2022, these developments justified a more conditional developmental science: waiting reflects more than a decontextualised trait; claims of newborn action matching require precise controls; and an infant speech preference can be robust while method-sensitive. The main advance is a tighter connection between a theoretical claim, an explicitly defined measure and evidence that others can inspect or independently test. Transparency changes what can be learned from disagreement, while replication establishes how far a finding travels.
Past exam of the developmental science course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 2 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Calling childhood amnesia a myth is defensible only if the supposed myth is that infants cannot form lasting memories, or that adults' earliest reported age is an exact biological boundary. Neither proposition is warranted. It does not follow that the relative scarcity of accessible autobiographical memories from early childhood is imaginary. The central distinction is between forming a memory, retaining information, retrieving it with particular cues, reporting it verbally and assigning it a date. Evidence about one stage cannot automatically settle the others.
An important methodological change was the development of tests that do not ask infants to narrate an event. Carolyn Rovee-Collier and colleagues trained three-month-olds to move a crib mobile through footkicking. A ribbon-linked mobile provides a visible consequence of the infant's action; retention can then be assessed with the mobile present but no longer moving contingently. Elevated kicking relative to a pretraining baseline indicates retention of the learned relation, rather than a verbal report. In their 1980 study, a brief reminder exposure twenty-four hours before testing reinstated performance after delays of two or four weeks, despite the usual loss of the trained response after a much shorter interval. This directly challenges an account equating an initial failure to perform with complete erasure of the earlier experience.[ref]
Reactivation of infant memory by Carolyn Rovee-Collier and others. Science 208, 1159–1161; mobile conditioning, reminder and retention experiments
The inference has limits. Reminder controls must show that the exposure does not simply teach an untrained infant the response, and changes in general activity must be separated from memory-specific kicking. More fundamentally, memory for an action–outcome contingency is not equivalent to an adult's consciously recollected autobiographical episode. A demonstration of infant learning refutes global incapacity to remember; it does not prove that the adult can later re-experience that mobile episode as part of a personal life history. Reactivation under a matching cue also need not imply spontaneous retrieval without that cue.
Gabrielle Simcock and Harlene Hayne brought the verbal-report problem into a more naturalistic event. Young children experienced a novel “Magic Shrinking Machine”: interacting with an apparatus produced apparently smaller versions of toys. Vocabulary was measured when the event occurred and again after a delay; later tests included verbal recall, photograph recognition and behavioural reenactment. Children could retain event information nonverbally while failing to describe aspects for which they had lacked productive vocabulary at encoding, even after their vocabulary expanded. The design provides known event content and an opportunity to compare different response formats. It shows how a later verbal interview can underestimate retained information.[ref]
Breaking the barrier? Children fail to translate their preverbal memories into language by Gabrielle Simcock and Harlene Hayne. Psychological Science 13, 225–231; Magic Shrinking Machine, verbal and nonverbal tests
It would still be too strong to infer intact, adult-like episodic memory hidden behind a purely linguistic barrier. Recognition supplies information unavailable in free recall, and reenactment can exploit familiar objects and motor routines. Unequal performance may therefore reflect unequal cue support as well as representational format. The appropriate conclusion is that reporting limitations contribute to apparent amnesia, not that every unreported early event survives unchanged. Prospective tests should separately vary cue reinstatement and response modality rather than interpreting all nonverbal successes as full autobiographical recollection.
Memory dating provides another challenge to a sharp boundary. Qi Wang and Carole Peterson followed a small group of children across an eight-year interval, asking for their earliest memories and their estimated ages at those events. Some of the same events remained reportable but were assigned progressively later ages. This forward telescoping can make an early-life period seem empty when surviving memories have migrated out of it on a retrospective timeline. Repeatedly following individual events is more informative than comparing different people's single earliest-memory reports. However, substantial attrition and uncertain initial dates limit the inference: a change in reported date does not establish the objectively correct date or show that dating error explains all missing memories.[ref]
The fate of childhood memories by Qi Wang and Carole Peterson. Frontiers in Psychology 6, 2038; initial, two-year and eight-year memory dating interviews
The strongest reason to reject the blanket “myth” claim comes from prospective evidence of actual loss of access. Patricia J. Bauer and Marina Larkina documented conversations about specific events when children were three, then interviewed different subgroups at ages five to nine. Five- to seven-year-olds recalled at least sixty per cent of those early events, whereas eight- and nine-year-olds recalled fewer than forty per cent. Thus memories that demonstrably existed in childhood later became unavailable to the interview procedure. Older children's surviving narratives could be richer even while fewer events remained accessible: increasing narrative skill and increasing loss of early memories are compatible.[ref]
The onset of childhood amnesia in childhood by Patricia J. Bauer and Marina Larkina. Memory 22, 907–924; age-three interviews and prospective follow-ups at ages five to nine
That study does not isolate a single neural cause. Longer retention intervals accompany older test ages, parent–child conversations are themselves retrieval practice, and forgotten-at-test does not mean physically erased. Nevertheless, it rules out explaining the entire phenomenon as failure to encode in the first place, and it cannot be dismissed as adults merely misdating every surviving memory. The outcome to explain is a developmental distribution of accessibility produced over time.
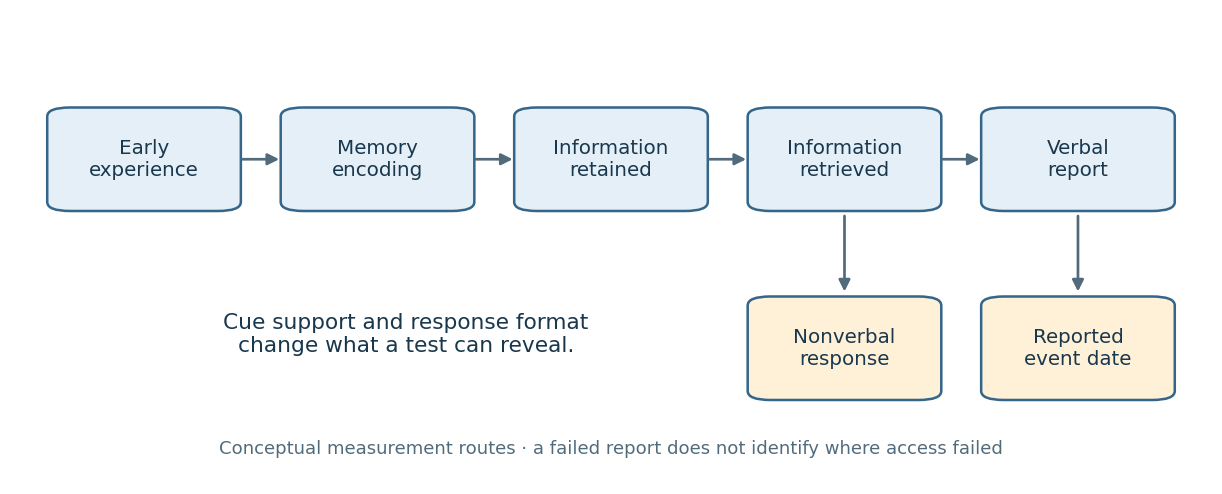
This framework yields clear discriminating predictions. A retrieval account predicts improvement when appropriate cues are reinstated without teaching new event content. A verbal-expression account predicts better nonverbal than verbal performance when language at encoding is limited. A dating account predicts shifts in the age assigned to an otherwise recognisable event. A forgetting account predicts loss of access to prospectively documented events. These mechanisms can coexist, so success for one is not a refutation of all the others.
By the 2022 evidence base, childhood amnesia should therefore be treated as a genuine pattern of sparse later autobiographical access whose boundaries and mechanisms are often oversimplified. The myths are a memoryless infancy, a universal discontinuity at one birthday and the assumption that an unsuccessful verbal report proves no retained information. Rejecting those myths makes the phenomenon more precise; it does not abolish the explanatory problem.
Past exam of the developmental science course of the year 2 of the psychology (experimental) course of the University of Oxford 2022 1 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Executive functions should contribute most when learning or assessment requires keeping several pieces of information active, suppressing an attractive error, coordinating successive operations or changing strategy. This predicts particularly strong links with multistep mathematics, mathematical problem solving and reading comprehension, alongside classroom engagement and following instructions. It predicts a smaller direct contribution to well-practised fact retrieval or fluent decoding once those operations are automated. That is a task-demand hypothesis, not a claim that every mathematics score must correlate more strongly with executive functions than every literacy score.
Working memory maintains goals and intermediate results: a child doing a subtraction with borrowing must retain both the original problem and its updated intermediate state. Inhibitory control helps suppress a larger-number answer that is tempting but irrelevant, or a familiar operation when the problem requires another. Cognitive flexibility supports switching between representations or abandoning an unsuccessful strategy. In reading, maintaining earlier propositions and rejecting an initially plausible interpretation should matter especially for comprehension and inference; knowledge of letter–sound correspondences is not itself an executive function. Repeated practice can change which process is the bottleneck, so developmental stage and familiarity matter.
Historically, the unity-and-diversity framework helped replace an undifferentiated “executive ability” with correlated but distinguishable processes. Akira Miyake and colleagues used several tasks per proposed component and latent variable analysis to separate common executive variance from individual task demands. Their influential study tested adults: its factor structure cannot simply be assumed to describe preschool children. It nevertheless supplies a crucial methodological lesson. A single executive task measures the intended control process together with perception, language, motor speed and task-specific strategies. Treating a raw score as a pure capacity risks attributing the wrong source of variance to school achievement.[ref]
More directly, Clancy Blair and Rachel Peters Razza followed 141 children from low-income homes, measuring preschool self-regulation and later kindergarten mathematics and literacy. Their inhibition measure required children to tap once when the experimenter tapped twice and twice after one tap: the apparatus is simple, but the rule requires suppressing imitation and maintaining an opposite response mapping. Inhibitory control was associated with emerging mathematics and reading after accounting for intelligence. This supports the importance of regulation during early learning, but the design was observational, not random assignment to different inhibitory capacities. Shared language, family circumstances or classroom experience could influence both performances.[ref]
Relating effortful control, executive function, and false belief understanding to emerging math and literacy ability in kindergarten by Clancy Blair and Rachel Peters Razza. Child Development 78, 647–663; Measures and academic-outcome regressions
Lucy Cragg and colleagues provided a more differentiated mathematical analysis. Their sample of 293 participants aged eight to twenty-five completed executive tasks and measures of factual knowledge, procedures and conceptual understanding. Working memory had both an association with overall mathematics and indirect associations through mathematical component skills; inhibition measured in a numerical context was linked to factual and procedural knowledge. This is more informative than treating “mathematics” as one outcome. However, statistical mediation in an age-spanning observational sample does not establish that changing the putative mediator would change attainment. Numerically framed executive tasks can also share content with the achievement measures, increasing the apparent specificity of the association.[ref]
Direct and indirect influences of executive functions on mathematics achievement by Lucy Cragg and others. Cognition 162, 12–26; abstract, executive-function battery and mediation models
Kate Cain and colleagues supply a corresponding literacy result. In assessments at ages eight, nine and eleven, working memory and comprehension components such as inference and monitoring predicted reading comprehension after controls for word reading and verbal ability. Sentence-span and digit-working-memory measures helped avoid defining the entire construct by one task. This supports a contribution beyond decoding, but the reported concurrent relations at successive ages are not an experimental demonstration of causal direction; comprehension itself can affect performance on verbally loaded memory tasks.[ref]
Children's reading comprehension ability: concurrent prediction by working memory, verbal ability, and component skills by Kate Cain and others. Journal of Educational Psychology 96, 31–42; longitudinal assessments at eight, nine and eleven years, concurrent prediction models
Evidence across populations qualifies the temptation to make executive functions the master explanation of achievement. Greg J. Duncan and colleagues compared six longitudinal datasets while controlling earlier child skills and family background. School-entry mathematics and reading were strong predictors of subsequent attainment; attention added prediction, whereas several socioemotional measures did not. Attention ratings are not interchangeable with laboratory inhibition or working memory measures. The result supports a classroom-regulation pathway while showing that already acquired domain knowledge remains central. Learning also exercises executive control, so baseline-adjusted longitudinal associations do not eliminate reciprocal influence or unmeasured confounding.[ref]
School readiness and later achievement by Greg J. Duncan and others. Developmental Psychology 43, 1428–1446; abstract and cross-dataset models; corrected version
Intervention offers a sharper causal test, but its target and outcome must be distinguished. Darren L. Dunning and colleagues randomly allocated seven- to nine-year-olds with low working memory to adaptive computerised training, low-load nonadaptive training or no training. The adaptive condition improved several untrained working memory tests, with some gains maintained over time, but did not produce corresponding academic or classroom-analogue benefits. The active comparison helps separate memory-load effects from attention, computer practice and expectations. Crucially, improvement on an untrained but structurally similar memory test is near transfer; improved reading or mathematics would be far transfer. One does not entail the other.[ref]
Does working memory training lead to generalized improvements in children with low working memory? by Darren L. Dunning and others. Developmental Science 16, 915–925; three-arm randomised trial, Results and Discussion
This trial does not show that working memory is irrelevant to achievement. A resource can constrain performance even when practising isolated tasks fails to change how it is deployed in a classroom. Nor does one intervention test all executive components, age groups or teaching methods. It does undermine the stronger inference from correlation to a promise that generic executive training will raise school attainment. Supporting instruction through shorter directions, external reminders and staged problems can reduce executive demands; whether any particular classroom support improves learning still requires an appropriately controlled outcome study.
The most defensible answer is therefore conditional and specific. Executive differences are especially plausible influences on managing novel, attentionally demanding, multistep learning and demonstrating that learning under load. They operate alongside knowledge, language, motivation and opportunity. Strong evidence would combine reliable multi-task executive measures, differentiated academic outcomes, repeated measurements with comparable meaning across ages, and interventions with active controls and delayed achievement tests. Existing prospective and experimental evidence supports executive functions as contributors to learning, while limiting claims that they are a single cause of educational success.
Past exam of the developing new and effective psychological treatments for anxiety disorders and psychosis course of the University of Oxford 2022 6 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Conditioning explains an important part of reexperiencing: a cue associated with a traumatic event can later trigger fear and involuntary recollection. It does not, by itself, fully explain the content, sensory qualities, sense of present occurrence or persistence of every intrusion. The best answer therefore separates a mechanism for triggering a response from a theory of what is represented and why the representation is retrieved in this particular form.
In a simple conditioning account, an initially neutral cue becomes associated with an aversive event. A similar cue encountered later can evoke defensive arousal even when the danger is absent. Stimulus generalisation explains reactions to reminders that only resemble the original cue, while avoidance can limit opportunities for learning that the present context is safer. Extinction is not necessarily erasure: new learning can compete with an earlier association, and a changed context or delay can allow fear to return.
This account predicts cue-dependent episodes and bodily responses. A particular sound, smell or visual pattern may precipitate a sudden experience before the person identifies its connection to the trauma. Absence of consciously recognising the reminder does not mean that no cue was present. However, a conditioned response could be autonomic arousal or an urge to escape; it need not include a vivid autobiographical image or the feeling that a past event is happening now. Those additional properties require explanation.
Anke Ehlers and colleagues investigated the content and quality of intrusive memories after different traumas. Intrusions often concerned sensory impressions just before the event or before its worst emotional moments. Their warning-signal hypothesis proposes that these impressions acquired predictive significance. This is compatible with associative learning, but also refines a simple replay account: what is reexperienced may be a cue that signalled worsening danger rather than a literal representation of the objectively most injurious moment. The descriptive observations motivate the hypothesis without experimentally proving the original association.[ref]
The nature of intrusive memories after trauma: the warning signal hypothesis by Anke Ehlers and others. Behaviour Research and Therapy 40, 995–1002; descriptions of intrusion content, sensory qualities and moments preceding worst impact
The distinction matters because trauma is an extended, interpreted event. A moment can become especially threatening when its meaning changes—for example, when a previously ambiguous situation is understood as inescapable. The relevant reminder may reflect that subjective transition. A model that treats the whole event as one undifferentiated shock misses the organisation of the remembered experience. Retrospective descriptions, however, can be reconstructed, so prospective or carefully controlled analogue evidence is useful alongside clinical interviews.
Conditioning experiments provide converging but narrower evidence. Mohammed R. Milad and colleagues studied sixteen people with PTSD and fifteen trauma-exposed controls using a two-day fear-conditioning and extinction procedure in a 3-T fMRI scanner. Skin conductance indexed conditioned responding. The groups did not differ significantly in acquisition or immediate extinction, but the PTSD group showed poorer extinction recall the following day, with associated differences in relevant brain activity. This supports altered retention or retrieval of safety learning; it did not directly measure autobiographical flashbacks or establish whether the group difference preceded trauma.[ref]
Neurobiological basis of failure to recall extinction memory in posttraumatic stress disorder by Mohammed R. Milad and others. Biological Psychiatry 66, 1075–1082; 16 PTSD/15 trauma-exposed controls, two-day conditioning, skin conductance and 3-T fMRI
Memory theories address features left underspecified by a reflex account. Chris R. Brewin and colleagues' original dual-representation theory distinguished verbally accessible memories from memories automatically accessible through situational cues. It proposed that cue-triggered sensory representations can produce reliving without ordinary deliberate narrative retrieval. This is a theoretical architecture, not proof of two anatomically discrete stores. Its explanatory value depends on generating predictions that distinguish access, contextual organisation and response processes rather than relabelling the clinical phenomena.[ref]
A dual representation theory of posttraumatic stress disorder by Chris R. Brewin and others. Psychological Review 103, 670–686; original verbally/situationally accessible memory distinction
Anke Ehlers and David M. Clark's cognitive model emphasised a persistent sense of current threat arising from negative appraisals and properties of trauma memory, including difficulty integrating the event into its broader autobiographical context. Avoidance, suppression and other strategies can impede change. On this account, a reminder may retrieve an impression without sufficient information that the danger belongs to the past. Appraisals of an intrusion as evidence of permanent damage or loss of control can then increase distress and monitoring, potentially maintaining the problem beyond the initial cue association.[ref]
A cognitive model of posttraumatic stress disorder by Anke Ehlers and David M. Clark. Behaviour Research and Therapy 38, 319–345; current threat, trauma-memory properties and maintaining strategies
Experimental work on representation also constrains an exclusively fear-response account. Emily A. Holmes and colleagues used a trauma-film analogue and randomly allocated participants, after a thirty-minute interval, to a brief visuospatial game or no task. Intrusions during the next week were reduced in the task condition, while recognition performance did not differ significantly. This suggests that involuntary imagery and deliberate memory performance can be affected differently. The analogue, comparator and limited follow-up do not establish prevention or treatment of clinical PTSD, nor prove that all recognition information was unchanged.[ref]
Reexperiencing should also be distinguished from related events. Rumination about why something happened, a future-oriented image and deliberate recollection are not interchangeable with a sensory flashback. Shame, guilt and grief can accompany intrusions as well as fear. A broad associative model can incorporate links to these meanings and responses, but then it needs explicit representational and contextual assumptions. Saying that every retrieved mental event is a conditioned reaction risks making the account true by definition rather than experimentally informative.
A discriminating experiment could hold reminder exposure constant while varying contextual information or its interpretation, with careful ethical safeguards and an analogue suitable for research. Measure autonomic response, involuntary imagery, deliberate recognition and sense of current occurrence separately. A reduction in bodily fear without a corresponding change in involuntary images would show that the endpoints dissociate; a contextual manipulation reducing reliving at comparable arousal would support a role beyond response magnitude. Predefine manipulation checks and avoid treating absence of a reported image as proof that no memory was activated.
Clinical studies should add prospective sampling of reminders and intrusions where feasible, rather than relying entirely on retrospective questionnaires. Repeated within-person observations can test whether contexts and appraisals precede an episode, though they do not remove all confounding. Treatment effects can provide converging evidence, but improvement after a multicomponent therapy does not determine whether conditioning, appraisal or memory organisation was the necessary pathway.
Conditioning is consequently a useful account of why reminders become potent and why responses can recur after apparent safety learning. A full explanation of reexperiencing also needs the representation retrieved, its contextual accessibility, the sense that it is occurring now and the meaning assigned to the experience. Associative, cognitive and autobiographical memory processes can therefore be complementary, provided their separate predictions remain open to test.
Past exam of the developing new and effective psychological treatments for anxiety disorders and psychosis course of the University of Oxford 2022 5 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Recent innovations offered plausible routes to better outcomes for delusions by replacing a broad, undifferentiated treatment target with specific maintaining processes. Persistent persecutory beliefs may be supported by worry, poor sleep, felt vulnerability, low confidence, reasoning inflexibility and safety behaviors. Changing one of these may create opportunities for a person to reconsider threat without demanding immediate agreement that their belief is wrong. The promise is mechanistic and practical; it does not imply that all delusions share one cause or that every plausible target will improve clinical outcomes.
A contributory-causal approach begins by identifying a potentially modifiable process, experimentally changing it and examining consequences for the clinical problem. Worry is an example: repeated anticipation of danger can generate threatening explanations and keep them mentally available. In the Worry Intervention Trial, Daniel Freeman and colleagues randomised 150 patients with persistent persecutory delusions to six sessions targeting worry alongside standard care, or standard care alone. Worry and delusion outcomes improved, with gains followed to 24 weeks. Because therapist contact was not matched, the result supports the added intervention package more securely than an exclusively worry-mediated effect.[ref]
Effects of cognitive behaviour therapy for worry on persecutory delusions in patients with psychosis (WIT): a parallel, single-blind, randomised controlled trial with a mediation analysis by Daniel Freeman and others. Lancet Psychiatry 2, 305–313; 150 patients, six worry sessions plus usual care versus usual care, eight-/24-week outcomes
Sleep offers a different entry point that may be more acceptable than directly debating a threat belief. The OASIS trial randomised 3755 university students with insomnia to digital CBT for sleep or usual practice. It produced a large sleep benefit and smaller changes in paranoia and hallucinatory experiences. This supports testing sleep as a contributory process, while the nonclinical student sample and usual-practice comparator prevent direct inference that the same intervention treats persistent delusions in patients with psychosis.[ref]
The effects of improving sleep on mental health (OASIS): a randomised controlled trial with mediation analysis by Daniel Freeman and others. Lancet Psychiatry 4, 749–758; 3755 university students with insomnia, digital CBT versus usual practice and population limits
The Feeling Safe Programme combined individually selected modules addressing relevant maintaining factors. Its 2021 trial allocated 130 patients with persistent persecutory delusions to Feeling Safe or same-therapist befriending, with usual care continuing. The six-month adjusted difference in delusional conviction favoured Feeling Safe by about 10.7 points on a 0–100 scale. A categorical recovery comparison was less precise and did not reach conventional significance. The positive continuous primary outcome therefore should not be restated as a definitively superior recovery rate.[ref]
Comparison of a theoretically driven cognitive therapy (the Feeling Safe Programme) with befriending for the treatment of persistent persecutory delusions: a parallel, single-blind, randomised controlled trial by Daniel Freeman and others. Lancet Psychiatry 8, 696–707; 130 patients, same-therapist befriending, six-month continuous conviction and categorical recovery distinction
Reasoning interventions aim to increase flexibility and slow hasty acceptance of threatening explanations. Philippa Garety and colleagues' SlowMo combined eight face-to-face sessions, digital material and a mobile application. In the 361-person analysis, the primary total paranoia score at 24 weeks did not show a statistically significant advantage over usual care, although several secondary and earlier outcomes favoured the intervention. There was no significant effect on jumping to conclusions. This mixed pattern is particularly important: an engaging, mechanistically informed treatment can show promising signals without meeting its prespecified primary test.[ref]
Effects of SlowMo, a Blended Digital Therapy Targeting Reasoning, on Paranoia Among People With Psychosis: A Randomized Clinical Trial by Philippa Garety and others. JAMA Psychiatry 78, 714–725; 361 in analysis, prespecified 24-week GPTS total endpoint and secondary outcomes
These approaches could improve outcomes for several reasons. Targeting common difficulties such as insomnia or worry can give treatment an understandable starting point. Personalised modules can concentrate time on processes actually present instead of requiring every patient to complete the same sequence. Concrete experiments may provide more persuasive evidence than verbal reassurance. Digital support can make an exercise accessible between appointments, while carefully designed measures can show whether the nominated process changed before the belief or distress changed.
However, a target can be associated with delusions without causing them. Poor sleep and worry may partly reflect a common adversity, or lessen when general distress improves. An intervention intended for one process can alter several others, making a statistical mediator an uncertain guide to the active ingredient. Even when a factor contributes causally, changing it may produce only modest benefit because other maintaining processes remain. Necessary theoretical precision includes specifying who has the target, how much it must change and which outcome should follow.
Outcome choice can make an innovation appear more or less successful. Conviction, preoccupation, distress, activity, quality of life and diagnostic status are related but distinct. Greater doubt about a threatening explanation may be valuable without elimination of the belief; conversely, a questionnaire change need not restore work or social participation. The difference between SlowMo's primary and secondary findings illustrates why the endpoint and assessment time should be specified in advance. Multiple favourable secondary results cannot simply replace an unsuccessful primary test.
Clinical heterogeneity also matters. A treatment developed for persistent persecutory delusions is not automatically established for every delusional theme, acute state or diagnostic group. Language requirements, willingness to attend research therapy and referral patterns select who enters a trial. Comorbid depression, cognitive difficulties, substance use or continuing victimisation may alter the usefulness of a module. An unusual belief should be assessed in its cultural and social context; a psychological account must not assume that all reported threats are unreal.
Innovations can fail at implementation even when the trial mechanism is sound. Skilled research therapists, close supervision and protected time may be unavailable in routine services. A mobile application can increase opportunity for practice but also introduce access, privacy or comprehension barriers. Adding modules can increase burden, dilute effective content or delay the experiment that matters most. Patients may prefer a different target from the one selected by a questionnaire. Acceptability, fidelity, reach and cost therefore need direct measurement alongside symptom outcomes.
A strong next study would compare an adapted innovation with a credible active treatment in several services, with adequate power and blinded assessment. Prespecify primary conviction or distress outcomes, patient-prioritised functioning and longer-term maintenance. Measure candidate mechanisms repeatedly, recording which modules are actually received; module choice in a tailored treatment is not random and cannot itself identify the best component. A complementary factorial or sequentially randomised experiment could test specific additions while preserving adequate care for all participants.
By May 2022, the most convincing advance was the shift toward testable mechanisms and more rigorous, symptom-focused clinical comparisons. Worry, sleep, flexible reasoning and personalised threat-learning approaches offered reasons for optimism, with some positive clinical results and important null findings. Better outcomes would depend on genuine target engagement, adequate comparisons, generalisation and feasible delivery, rather than novelty, a digital format or a plausible causal diagram alone.
Past exam of the developing new and effective psychological treatments for anxiety disorders and psychosis course of the University of Oxford 2022 4 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25A psychological treatment has a specific effect only relative to a clearly defined alternative explanation. Benefit beyond waiting is different from benefit beyond credible therapeutic contact, and both differ from evidence that a named technique works through its proposed mechanism. No single research design establishes all three. A persuasive programme combines controlled clinical comparisons with component and process experiments, while keeping patient-relevant outcomes central.
An uncontrolled before-and-after study cannot isolate a treatment effect. People may enter care when symptoms are unusually severe, creating regression toward their longer-term level; difficulties can improve naturally; expectations, concurrent care and repeated assessment can also change outcomes. A waiting-list randomised trial controls some time-related explanations but adds unequal expectations and contact. It can establish benefit from being offered the treatment package compared with waiting under those conditions, without identifying which ingredient produced the difference.
For specificity beyond nonspecific therapy effects, use a randomised comparison with a credible active intervention. Match time, attention, therapist competence and assessment opportunities as far as the question permits. Measure credibility and expected benefit rather than assuming equivalence from similar session counts. Keep relevant usual care available in both arms. Allocation concealment prevents recruitment decisions from anticipating the next assignment, while blinded independent outcome assessment reduces a different source of bias after allocation. Therapists and patients usually cannot be fully blinded to psychological procedures.
Daniel Freeman and colleagues' Feeling Safe trial illustrates this stronger package comparison. Patients with persistent persecutory delusions received the programme or befriending delivered by the same therapists, alongside usual care. At six months, the primary continuous conviction measure favoured Feeling Safe. This supports an effect beyond the particular befriending comparator, but does not establish that each module is necessary or that the whole benefit travelled through one nominated mediator.[ref]
Comparison of a theoretically driven cognitive therapy (the Feeling Safe Programme) with befriending for the treatment of persistent persecutory delusions: a parallel, single-blind, randomised controlled trial by Daniel Freeman and others. Lancet Psychiatry 8, 696–707; 130 patients, same-therapist befriending, six-month continuous conviction and categorical recovery distinction
The comparator should be interpreted fairly. A weak or implausible control can exaggerate apparent specificity, while an active comparator may itself change the proposed mechanism. If befriending improves social confidence, it is not a biologically inert placebo. A null result may mean two useful treatments have similar effects, both are ineffective, or the study is too imprecise. Failure of a superiority test does not demonstrate equivalence; an equivalence or noninferiority question requires prespecified clinically justified margins and appropriate precision.
A dismantling trial varies a specified component while keeping the surrounding treatment adequate and similar. For example, compare the same exposure programme with and without a safety behavior intervention. This estimates a conditional contribution: absence of an additional benefit does not imply that the component is useless in every context, because another part may produce similar learning. A factorial design can independently vary an action and its explanatory rationale, estimating their effects and interaction when the study has adequate power.
The early panic safety behavior experiment provides both an example and a caution. Greater change after brief exposure with precautions reduced supports the combined manipulation. Yet behavioral instructions and the explanation of the exercise were not fully separated. The appropriate next test would vary those elements independently and check actual behavior and expectancy change. Simply renaming the conditions 'cognitive' and 'behavioral' would not remove the confounding.[ref]
An experimental investigation of the role of safety-seeking behaviours in the maintenance of panic disorder with agoraphobia by Paul Salkovskis and others. Behaviour Research and Therapy 37, 559–574; brief exposure manipulation and repeated behavioural test
A mechanistic experiment can provide more direct leverage than a full treatment comparison. Colin MacLeod and colleagues trained attentional bias using a modified dot-probe task and tested later responses to stress. This asked whether experimentally changing information processing altered emotional vulnerability. It remains necessary to establish that the manipulation engaged the intended process rather than only a task-specific strategy, and that any effect transfers to the clinical phenomenon of interest. Laboratory emotional vulnerability is not itself diagnostic remission.[ref]
Selective attention and emotional vulnerability: assessing the causal basis of their association through the experimental manipulation of attentional bias by Colin MacLeod and others. Journal of Abnormal Psychology 111, 107–123; modified dot-probe training and responses to a standardised stress task
Likewise, Daniel Freeman and colleagues used virtual social environments to compare exposure against threat testing with safety behavior reduction. Both groups encountered graded situations, making the content of learning more directly investigable than in a therapy-versus-waiting comparison. The combined manipulation and brief follow-up constrain the mechanism claim. A useful manipulation check, an independent behavioral outcome and later transfer assessment strengthen the design more than a treatment label does.[ref]
Virtual reality in the treatment of persecutory delusions: randomised controlled experimental study testing how to reduce delusional conviction by Daniel Freeman and others. British Journal of Psychiatry 209, 62–67; 30 participants, graded social environments, safety reduction versus exposure and real-world assessment
Mediation analysis is informative but insufficient on its own. Randomising treatment identifies the total effect of assignment under the trial's assumptions; it does not automatically randomise the mediator. Symptom improvement could change reported beliefs, or an unmeasured process could influence both the belief score and the outcome. Measure the proposed mediator before the downstream outcome, assess competing pathways and perform sensitivity analyses. Replication using a different way to alter the same process can provide converging evidence; stronger identification may require experimental manipulation of that process itself.
Clinical trials also need suitable sampling, prespecified outcomes, adequate power, intention-to-treat analysis and transparent missing data handling. Outcomes should include functioning and possible deterioration, with follow-up long enough to distinguish transient reassurance from durable benefit. Treatment fidelity and competence must be assessed in both arms. Therapist allegiance, clustering of patients within therapists and differential dropout can affect interpretation. Statistical significance alone does not establish a meaningful improvement, especially when many outcomes or subgroup comparisons are explored.
Pragmatic implementation trials answer a complementary question: does the intervention add benefit in ordinary care, at acceptable cost and burden? Jaime Delgadillo and colleagues' therapist-cluster trial tested an automated feedback system linked to supervisory review within routine services. Its comparison isolates the added feedback arrangement more closely than an observational association between high-performing services and monitoring. It still tests a specified package of information and response, rather than an abstract effect of measurement divorced from clinical action.[ref]
Feedback-informed treatment versus usual psychological treatment for depression and anxiety: a multisite, open-label, cluster randomised controlled trial by Jaime Delgadillo and others. Lancet Psychiatry 5, 564–572; 77 participating therapists, 2233 patients, cluster allocation and not-on-track outcomes
The strongest conclusion consequently states its level of specificity. A well-conducted active control trial can establish an incremental treatment-package effect. A dismantling or factorial trial can identify a component's contribution within a defined context. An experimental process manipulation, supported by temporally ordered measurements and converging clinical evidence, can constrain the mechanism. Keeping these claims separate prevents a successful therapy from being treated as proof of its entire theory, while preserving the practical importance of improvements patients actually experience.
Past exam of the developing new and effective psychological treatments for anxiety disorders and psychosis course of the University of Oxford 2022 3 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Anxiety disorders centrally involve cognition, but describing them solely as disorders of cognition is too strong unless the term is defined so broadly that it loses explanatory value. Threat appraisal, attention, interpretation and memory can contribute to excessive fear and avoidance. Bodily arousal, learning history, action and the environment also matter. A useful account specifies how these processes interact and asks whether changing a proposed cognitive process changes anxiety, rather than simply observing that anxious people report anxious thoughts.
David M. Clark's cognitive model of panic illustrates the explanatory gain. Ordinary sensations such as a racing heart can be interpreted as evidence of imminent catastrophe. Fear increases arousal, which provides further sensations for threatening interpretation. The account distinguishes the bodily input from its meaning and explains why similar sensations need not produce the same fear in different circumstances. It also predicts that precautions and avoidance can prevent disconfirmation. The 1986 paper supplied a mechanistic model, not by itself proof that every panic episode requires a consciously articulated catastrophic thought.[ref]
A cognitive approach to panic by David M. Clark. Behaviour Research and Therapy 24, 461–470; catastrophic interpretation model, not a new clinical trial
The distinction between cognition and explicit verbal reasoning matters. A person may orient rapidly toward threat, experience an image or respond to a bodily sensation before they can describe a proposition. Absence of a reported sentence does not establish absence of information processing. Equally, a theory should not rescue itself from every negative finding by postulating an inaccessible belief. It must specify observable predictions and measures that can fail, including what would count as successful alteration of the proposed process.
Cross-sectional evidence is insufficient to establish direction. A threat interpretation could increase anxiety, anxiety could bias the interpretation, or a third factor could influence both. Questionnaires can also partly measure the same evaluative content on both sides of the association. Longitudinal prediction improves temporal ordering but leaves confounding possible. Experiments that manipulate interpretation or attention therefore offer a stronger test, especially when changes in the intended process are verified separately from changes in symptoms.
Andrew Mathews and Bundy Mackintosh reported five experiments inducing relatively threatening or benign interpretations of ambiguous material. Interpretative bias could be changed, but parallel effects on state anxiety depended on active processing of personally relevant meanings. This supports a causal contribution under specified conditions and shows that a changed task response need not automatically mean changed emotional experience. These experiments do not establish that an interpretation-training task is a complete treatment for a diagnosed anxiety disorder.[ref]
Induced emotional interpretation bias and anxiety by Andrew Mathews and Bundy Mackintosh. Journal of Abnormal Psychology 109, 602–615; five experiments, ambiguity training, active meaning generation and state anxiety
Colin MacLeod and colleagues manipulated selective attention using a modified dot-probe procedure. The location of a subsequent probe was used to train attention in different directions relative to emotional material, followed by a standardised stress task. Differences in emotional vulnerability support a contribution from attention rather than association alone. Transfer from a laboratory induction to enduring clinical change, however, remains an additional question. Learning a task contingency, altered expectancies and the reliability of the process measure all require consideration.[ref]
Selective attention and emotional vulnerability: assessing the causal basis of their association through the experimental manipulation of attentional bias by Colin MacLeod and others. Journal of Abnormal Psychology 111, 107–123; modified dot-probe training and responses to a standardised stress task
Clinical treatment comparisons provide complementary evidence. David M. Clark and colleagues compared cognitive therapy, applied relaxation and imipramine in panic disorder, with self-exposure homework shared across conditions. The findings supported cognitive therapy as a useful treatment. They do not make the comparison a pure test of thought change against an absence of learning or behavior: treatment packages differ in multiple ways, and a pharmacological treatment can also alter the sensations and experiences from which beliefs are formed.[ref]
A comparison of cognitive therapy, applied relaxation and imipramine in the treatment of panic disorder by David M. Clark and others. British Journal of Psychiatry 164, 759–769; treatment comparison, common self-exposure homework and follow-up
Safety behavior research further shows why a sharp cognition-versus-behavior division can mislead. Paul Salkovskis and colleagues found that changing precautions during exposure altered catastrophic beliefs and anxiety. The behavior may control which evidence is encountered and how success is explained. Conversely, a different explanation may make abandoning the behavior possible. These reciprocal effects favour a specified feedback system over treating observable action and mental representation as competing, self-contained causes.[ref]
An experimental investigation of the role of safety-seeking behaviours in the maintenance of panic disorder with agoraphobia by Paul Salkovskis and others. Behaviour Research and Therapy 37, 559–574; brief exposure manipulation and repeated behavioural test
Learning accounts also need not exclude cognition. An inhibitory learning approach proposes that exposure establishes alternative expectations rather than necessarily erasing the original threat association. Context-dependent retrieval can explain return of fear after apparently successful practice. Michelle G. Craske and colleagues developed a translational framework around this distinction. It offers a way to connect expectation, experience and later retrieval, while its clinical implementation requires direct evaluation rather than assuming that a learning rationale proves a particular protocol optimal.[ref]
Maximizing exposure therapy: An inhibitory learning approach by Michelle G. Craske and others. Behaviour Research and Therapy 58, 10–23; inhibitory-learning framework and illustrative strategies, not a component trial
The broader phrase 'anxiety disorders' also conceals heterogeneity. The feared consequence in social anxiety differs from the interpretation of bodily sensations in panic or persistent worry about many possible outcomes. A common information processing principle can coexist with disorder-relevant mechanisms. Actual danger and social adversity must be assessed: an expectation is not distorted simply because it concerns something distressing. Genetic, developmental and physiological influences can affect sensitivity to threat without fixing the meaning or outcome of every encounter.
Strong evidence for a particular cognitive mechanism would combine an experimental manipulation, a successful process check, subsequent change in fear and transfer to relevant everyday behavior. A factorial design could vary interpretation and a maintaining precaution separately, with matched contact and exposure opportunities. Repeated measurements should establish whether the cognitive change precedes the outcome. Treatment randomisation identifies the package effect, but mediation requires additional assumptions because the mediator itself has not necessarily been randomised.
Evidence against an exclusive account would include effective treatment without the predicted process change, or a precise null effect on anxiety after a successful, sufficiently strong manipulation of that process. Such a result might constrain the population or context in which the mechanism matters rather than rule out all cognitive contributions. Measurement sensitivity and alternative pathways must be considered without making the theory unfalsifiable.
The defensible conclusion is that cognition contributes materially to the persistence and modification of anxiety, with experimental evidence beyond introspective report. It is less defensible to claim that all anxiety disorders are caused only by consciously held false beliefs, or that the success of cognitive therapy establishes that exclusivity. Mechanistic precision and evidence about causal interaction are more informative than choosing between cognition, the body and behavior as if only one could matter.
Past exam of the developing new and effective psychological treatments for anxiety disorders and psychosis course of the University of Oxford 2022 2 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25Routine outcome monitoring has made the results of IAPT services unusually visible and has created opportunities to improve care. Its benefits should be separated into three claims: measurement is more complete, the resulting information supports clinical and organisational decisions, and acting on that information improves patient outcomes. The first two do not automatically prove the third. A service can record a recovery accurately without the act of recording being its cause.
The historical IAPT programme expanded psychological treatment for depression and anxiety, using evidence-based interventions and stepped care where appropriate. Repeated measures allow a trajectory to be examined instead of relying on a clinician's general impression at discharge. Depression, general anxiety and disorder-relevant symptoms can be monitored alongside functioning and the person's own goals. A symptom questionnaire is a useful indicator, but a cutoff-based service definition of recovery is not identical to a blinded diagnostic interview or to complete restoration of everyday life.
David M. Clark and colleagues' evaluation of the Doncaster and Newham demonstration sites showed that session-by-session collection could achieve unusually complete before-and-after information in routine care. Reported recovery was about 55–56% among patients seen at least twice, and a follow-up examined maintenance beyond the last session. These prospective service cohorts demonstrated feasibility and informed implementation, but were not randomised tests of monitoring itself. Their denominator also excluded people who never progressed beyond an initial contact.[ref]
Improving access to psychological therapy: Initial evaluation of two UK demonstration sites by David M. Clark and others. Behaviour Research and Therapy 47, 910–920; Doncaster and Newham prospective service cohorts, sessional monitoring and ten-month follow-up
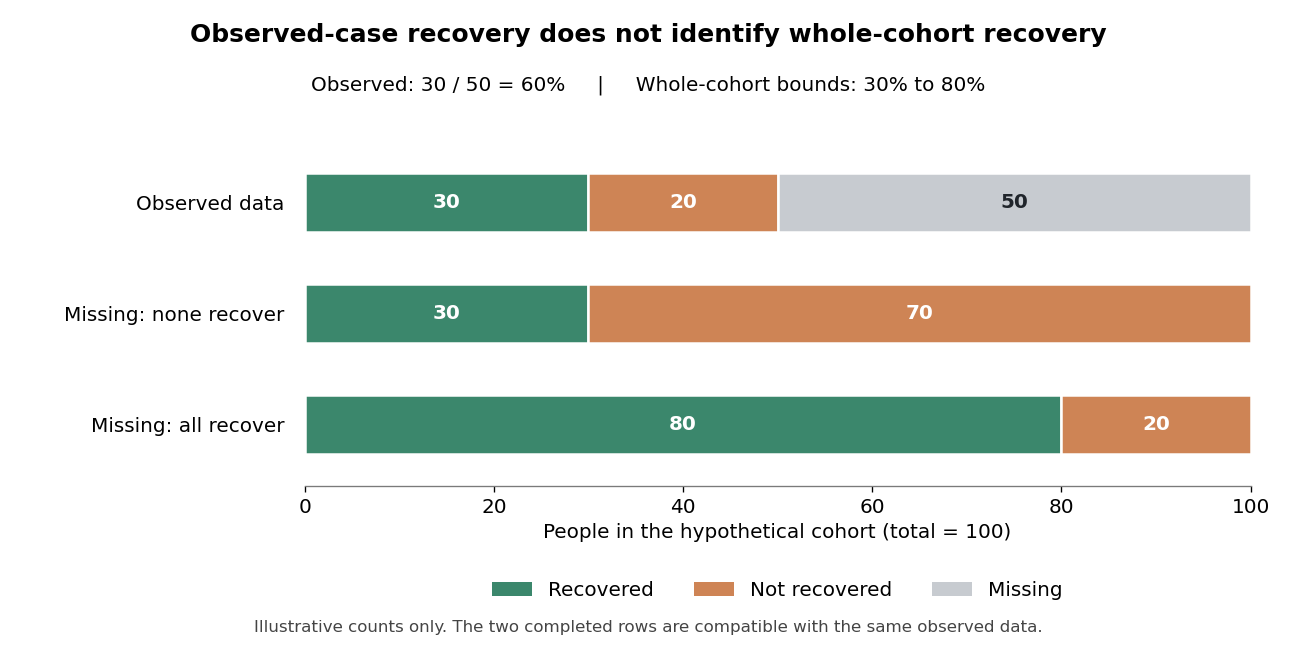
Completeness matters because selective follow-up can substantially distort apparent success. Consider a purely hypothetical cohort of one hundred baseline cases: fifty have an endpoint recorded and thirty of those meet the chosen recovery criterion. The observed-case recovery rate is 60%. If none of the fifty missing cases recovered, the whole-cohort rate is 30%; if all recovered, it is 80%. The missing-outcome bounds for a binary endpoint are sharp: both extremes fit exactly the observed data. Without assumptions or additional measurements, the observations alone cannot identify where within those bounds the cohort lies. This example is not an estimate of any IAPT service.


Sessional collection reduces dependence on a separate final questionnaire: a last available observation often exists even when a planned final appointment is missed. It does not make all missingness harmless. A last attended session can occur earlier for someone who disengages, and is not automatically equivalent to a common long-term endpoint. Outcomes should therefore be reported with clear eligibility, timing, completion and missing data definitions. Monitoring treated patients very thoroughly still does not describe those who were referred but never entered treatment.
David M. Clark and colleagues' 2018 analysis reported approximately 98% before-and-after symptom coverage among treated IAPT patients. It related public service outcomes to organisational characteristics and examined whether those characteristics also predicted changes between years. Waiting, missed appointments and the organisation of treatment were associated with outcomes; deprivation remained relevant. This made variation actionable and generated specific implementation hypotheses. Nevertheless, service-level associations and longitudinal prediction remain vulnerable to case mix, selection and unmeasured organisational differences.[ref]
Transparency about the outcomes of mental health services (IAPT approach): an analysis of public data by David M. Clark and others. Lancet 391, 679–686; 98% outcome coverage among treated patients, organisational predictors and between-year analyses
At the individual level, a visible trajectory can identify deterioration or lack of progress earlier than an end-of-treatment assessment. This provides a reason to review the formulation, barriers, intervention fidelity or level of care. It can make supervision concrete: a supervisor and therapist can examine which patients are not improving and whether the active treatment has actually been delivered. A score should initiate inquiry rather than automatically trigger a uniform decision, since transient distress, measurement error and contextual crises can change a session's result.
There is experimental evidence for an additional feedback system. Jaime Delgadillo and colleagues randomised therapists to automated outcome feedback or usual psychological treatment across eight NHS trusts. Seventy-seven therapists participated and 2233 patients were included. The system flagged people who were not on track and prompted supervisory review. Among those classified as not on track, feedback was associated with modestly better depression and anxiety outcomes, with effect sizes around 0.23 and 0.19 respectively. The trial tested feedback and its linked clinical response within services already collecting measures, not questionnaire collection versus no monitoring.[ref]
Feedback-informed treatment versus usual psychological treatment for depression and anxiety: a multisite, open-label, cluster randomised controlled trial by Jaime Delgadillo and others. Lancet Psychiatry 5, 564–572; 77 participating therapists, 2233 patients, cluster allocation and not-on-track outcomes
This distinction is central to interpreting the benefits. Data make a problem detectable; feedback makes it salient; a feasible clinical action must then address it. An alert that repeatedly identifies nonresponse without available treatment alternatives may add burden without improvement. Cluster allocation appropriately recognises that therapists change their practice across patients, while open-label delivery and quasi-random patient allocation to available therapists still qualify the causal interpretation. The modest subgroup effects should not be presented as proof that monitoring transforms every case.
At service level, routinely available outcomes support accountability, training evaluation and investigation of inequalities. Comparisons can identify where referral pathways, waiting times or treatment delivery need examination. However, unadjusted league tables can penalise services treating more complex or disadvantaged populations. Risk adjustment should be transparent and should not erase the very inequalities that require attention. Process measures, symptom outcomes, functioning and reach together give a fuller picture than one recovery percentage.
Targets can also create incentives to select easier cases, change denominators or emphasise crossing a threshold over a person's priorities. A reliable change index scales change by expected measurement error. Reliable improvement distinguishes such a change from a small numerical movement, while reliable recovery additionally considers caseness; neither removes the need to monitor deterioration and residual disability. Questionnaire accessibility, language and the validity of comparing groups require attention. Patients should understand why information is collected and how it contributes to care.
By May 2022, the clearest benefits were high outcome coverage, a transparent basis for improving implementation and a modest experimentally supported benefit from targeted feedback. Routine data had narrowed the gap between trial evidence and what services actually achieved. Further progress required responding intelligently to trajectories, preserving inclusive denominators and testing organisational changes, rather than treating measurement or a rising aggregate recovery figure as self-validating evidence of effectiveness.
Past exam of the developing new and effective psychological treatments for anxiety disorders and psychosis course of the University of Oxford 2022 1 Solution by Codex 0 2026-10-25
Codex 0 2026-10-25A safety behavior is an action intended to prevent a feared consequence or conceal signs of distress. Its immediate purpose can be understandable even when its longer-term effect maintains a problem. The useful unit of analysis is the action's function in a particular situation: carrying water, seeking reassurance or avoiding eye contact is not inherently pathological. A formulation must distinguish an anxiety-maintaining precaution from protection against genuine danger, ordinary support and a necessary accessibility adjustment.
One maintenance route is failed disconfirmation. A person predicts that ordinary bodily arousal will lead to collapse, completes an activity while gripping a support and then attributes survival to the grip. The feared catastrophe has not happened, but the episode is interpreted as evidence that the precaution was necessary. Immediate relief can negatively reinforce the precaution, increasing its future use. This explains why repeated encounters with a feared situation need not correct the threat belief when the person regards each successful encounter as a narrowly avoided disaster.
Safety behaviors can also change the evidence available. In a conversation, monitoring one's voice and rehearsing every sentence may divert attention from what another person says. Minimal replies can make the interaction less reciprocal; bodily monitoring can make ordinary sensations seem unusually salient. The person then treats this altered experience as confirmation of the original concern. These are testable possibilities, not a claim that every unsuccessful social encounter originates in the patient's cognition. Bullying, exclusion and discrimination can be real.
Paul Salkovskis and colleagues experimentally compared brief situational exposure with safety-seeking behaviors maintained or dropped in patients with panic disorder and agoraphobia. A subsequent behavioral test showed greater reductions in catastrophic beliefs and anxiety after the reduction condition. This supports a maintaining role, beyond the simple association between severe anxiety and frequent precautions. However, the manipulation also involved its therapeutic explanation, so the study does not perfectly isolate motor behavior from changed expectations about the task.[ref]
An experimental investigation of the role of safety-seeking behaviours in the maintenance of panic disorder with agoraphobia by Paul Salkovskis and others. Behaviour Research and Therapy 37, 559–574; brief exposure manipulation and repeated behavioural test
Freda McManus and colleagues obtained complementary social-anxiety evidence. Interviews found greater reported use in highly socially anxious participants, while both high- and low-anxiety groups regarded their strategies as helpful. Their experimental study manipulated safety behaviors together with self-focused attention and found detrimental effects. The combination strengthens the case that perceived helpfulness can differ from observed consequences, but leaves the separate contributions of attention and behavior incompletely identified.[ref]
Why social anxiety persists by Freda McManus and others. Journal of Behavior Therapy and Experimental Psychiatry 39, 147–161; interview and combined safety-behavior/self-focus manipulation
The account extends beyond conventional anxiety diagnoses. Daniel Freeman and colleagues randomised thirty patients with persecutory delusions to virtual-reality exposure or threat testing that included dropping safety behaviors. A head-mounted social environment allowed graded encounters with computer-generated people; the latter condition produced greater reductions in conviction and distress in a real-world assessment. This is a useful causal and translational experiment, but its small sample, brief intervention and combined instructions limit conclusions about durable treatment effects or any single ingredient.[ref]
Virtual reality in the treatment of persecutory delusions: randomised controlled experimental study testing how to reduce delusional conviction by Daniel Freeman and others. British Journal of Psychiatry 209, 62–67; 30 participants, graded social environments, safety reduction versus exposure and real-world assessment
Different clinical presentations can share the functional cycle without sharing an identical disorder. A checking ritual can prevent learning that uncertainty is tolerable; repeated reassurance can make confidence depend on another person's answer; social withdrawal can restrict opportunities to evaluate beliefs about others. These examples identify hypotheses for assessment rather than establish one universal cause of anxiety, obsessive-compulsive problems or psychosis. The onset of a difficulty can involve other processes even when a safety behavior subsequently helps maintain it.
The strongest version of the theory—that any safety behavior necessarily prevents useful learning—is not established. Stanley Rachman and colleagues compared exposure with response prevention against exposure followed by use of a hygienic wipe in eighty undergraduates with contamination fears. Both conditions showed sustained reductions across two sessions separated by two weeks. The analogue sample and short follow-up limit clinical generalisation, but the findings demonstrate why immediate elimination cannot be justified by definition alone.[ref]
Reducing contamination by exposure plus safety behaviour by Stanley Rachman and others. Journal of Behavior Therapy and Experimental Psychiatry 42, 397–404; 80 undergraduates, exposure with or without hygienic wipes, two-session analogue
An inhibitory learning interpretation makes the key question more precise: what does the person learn, and to what do they attribute safety? A precaution could block a decisive test, become a safety signal, or make initial participation feasible while leaving the relevant prediction open to testing. Michelle G. Craske and colleagues' framework emphasises alternative learning and its retrieval across contexts rather than equating exposure success with immediate calm. Its theoretical coherence does not establish the optimal safety behavior policy for every patient or intervention.[ref]
Maximizing exposure therapy: An inhibitory learning approach by Michelle G. Craske and others. Behaviour Research and Therapy 58, 10–23; inhibitory-learning framework and illustrative strategies, not a component trial
Measurement should therefore distinguish the behavior, the feared outcome and the person's explanation. Self-report inventories can indicate frequency but may group together actions with different functions. Observation during an agreed task, ratings of the predicted catastrophe and a review of why it did or did not occur give more specific information. An experiment should verify that the intended behavior actually changed, while monitoring whether a different precaution replaced it. Apparent nonresponse after an unsuccessful manipulation is not a clean falsification of the mechanism.
A stronger research design would randomise the use or reduction of an individually identified precaution while matching exposure opportunities, therapist attention and explanatory credibility. Where feasible, vary the explanation separately from the action, and assess both immediate expectations and later approach without the precaution in a new setting. Record acceptability and dropout as well as fear: an effective learning procedure that few people can engage with may have limited service value. Prespecify the feared mechanism and outcome so improvement is not retrospectively assigned to whichever explanation fits.
Safety behaviors consequently offer a productive transdiagnostic account of persistence and a route to testable treatment innovations. The evidence is strongest for specified actions and maintaining processes under controlled conditions. It supports assessing function and testing predictions collaboratively, while retaining necessary protections and acknowledging that helpful participation, short-term relief and durable threat learning need not move together.
There are unlisted articles, also show them or only show them.