Original volume: Examination papers for the Degree of Bachelor of Medicine by the University of Oxford (1864–1867). Open the original paper in the scanned volume, PDF page 11.
Original questions are transcribed from the public-domain edition. Credit: Wellcome Collection; original supplied by Royal College of Physicians, London. Source and public-domain rights statement.
Original question.
Make a sketch of the walls of the Thorax together with the Viscera they contain ; and state the variations which may and do take place in the relations they hold to each other consistently with health.
The thorax is a mobile osteocartilaginous enclosure with two pleural compartments and a central mediastinum; its visceral boundaries change normally with breathing and posture. The sketch is an anterior projection, with the subject's right on the viewer's left. It distinguishes the lower margin of a lung from the lower reflection of its pleura: those are different boundaries.
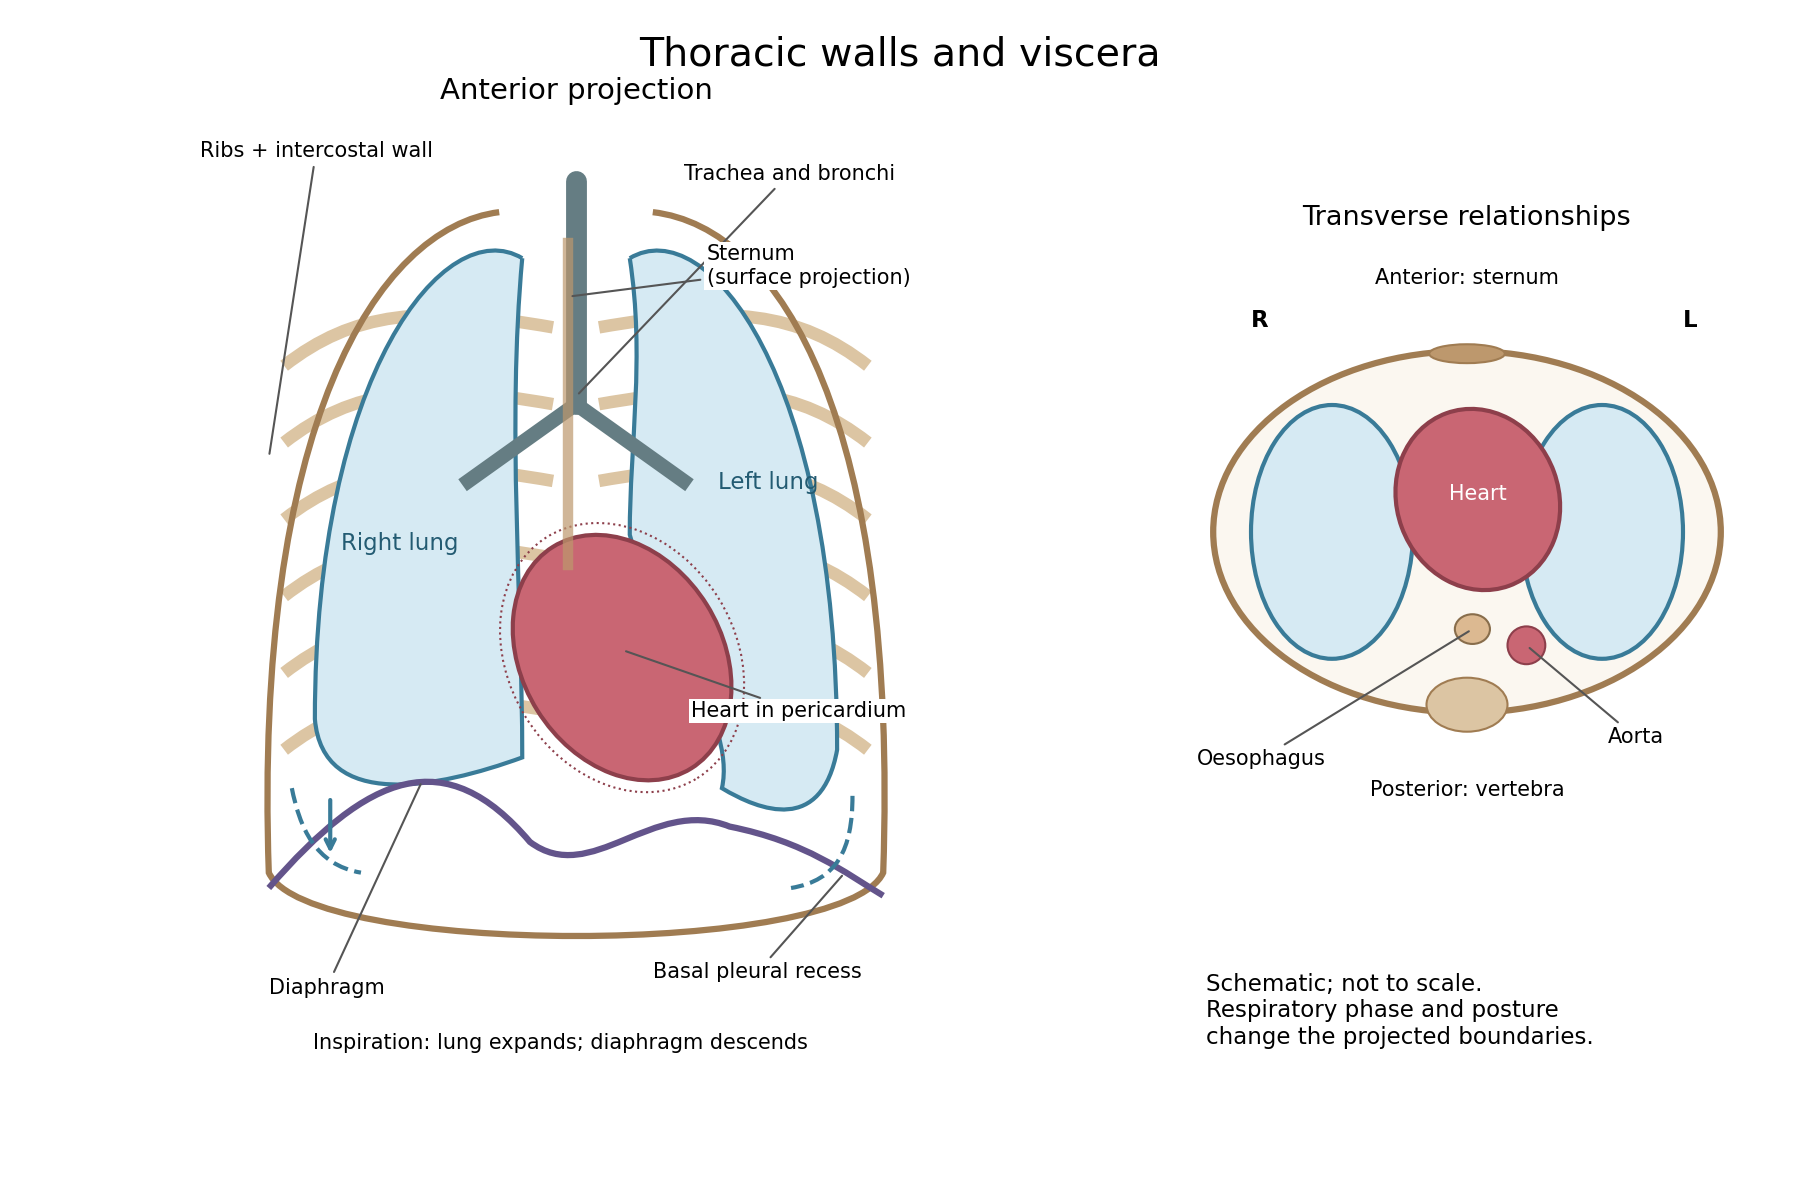
The posterior wall is formed by the twelve thoracic vertebrae and adjacent parts of the ribs; laterally the ribs and intercostal muscles form a flexible wall. Anteriorly lie the sternum, costal cartilages and anterior intercostal structures. The superior aperture communicates with the neck, while the respiratory diaphragm closes the inferior aperture. The lower thoracic wall therefore overlaps upper abdominal organs: not every organ under a lower rib is inside the pleural compartment.
Each lung is covered by visceral pleura. Parietal pleura lines the chest wall, upper surface of the respiratory diaphragm and side of the mediastinum, becoming continuous with visceral pleura at the root. The potential pleural space contains a lubricating fluid film; it is not normally an air-filled gap. The right lung has three lobes, the left two, with the cardiac notch and lingula accommodating the leftward projection of the heart. Each apex projects above the first rib into the root of the neck. The roots carry the bronchi, pulmonary vessels, nerves and lymphatic connections.[ref]
The heart and pericardium occupy chiefly the middle part of the inferior mediastinum, behind the sternum and between the lungs, with most of the cardiac bulk to the left of the median plane. The great vessels approach superiorly. The trachea divides into main bronchi behind the upper central region; the oesophagus descends behind the airway and heart. The descending thoracic aorta lies posteriorly, chiefly left of the vertebral bodies; the azygos venous route lies chiefly on the right. The thoracic duct and sympathetic chains belong to the posterior relations. A frontal projection superposes these structures and must not be mistaken for their order from front to back.
For a conventional quiet-breathing surface description, the lower lung border reaches approximately the sixth rib in the midclavicular line, eighth in the midaxillary line and tenth posteriorly near the scapular line. The pleural reflection descends approximately two ribs farther at corresponding landmarks: eighth, tenth and twelfth. These are orientation points, not immutable lines in every healthy individual. Inferiorly, the extra pleural extent forms the costodiaphragmatic recess. The right diaphragmatic dome usually stands higher, related to the underlying liver; the left is related to the stomach and other abdominal viscera.
In inspiration the respiratory diaphragm descends, the rib cage expands and lower lung margins move into the recesses; in expiration they retreat. The heart also shifts with the diaphragm and changes its surface projection as neighbouring lung expands. Deep inspiration, quiet expiration and forced expiration therefore cannot share a single normal map. The heart's own beat adds smaller cyclic movements.
Posture shifts the diaphragm and mediastinal contents: a supine position generally raises the domes compared with standing, while lateral positioning displaces mobile contents towards the dependent side. Body build, age, abdominal fullness and pregnancy change the available thoracic shape and diaphragmatic level. A distended stomach can raise the left dome and alter the cardiac projection without implying primary cardiac disease. The clinically useful comparison records posture and respiratory phase before judging an apparent difference in organ position.
Original question.
Give an account of the distribution, functions, and connections, of the Glossopharyngeal Nerve.
The glossopharyngeal nerve is a mixed ninth cranial nerve: it carries pharyngeal and lingual sensation, posterior tongue taste, carotid sensory input, motor fibres to stylopharyngeus, and a secretomotor route to the parotid gland. Its connections explain why its name alone understates its functions.
Rootlets leave the lateral medulla oblongata, behind the olive and above those of the vagus nerve. They cross the posterior cranial fossa and leave through the jugular foramen. Superior and inferior sensory ganglia lie at or near that passage. The cervical trunk descends in relation to the internal carotid artery and internal jugular vein, then turns forwards around stylopharyngeus. It reaches the pharyngeal wall between the superior and middle constrictors and divides towards the posterior tongue, tonsillar region and pharynx. Its topographical association with the vagus does not make the two nerves functionally identical.
The tympanic branch returns through the inferior tympanic canaliculus into the middle ear. Its tympanic plexus supplies the mucosa of the tympanic cavity, auditory tube and related air spaces and communicates with carotid sympathetic fibres. Preganglionic parasympathetic fibres continue through the lesser petrosal nerve to the otic ganglion. Postganglionic fibres then reach the parotid gland with the auriculotemporal nerve, a branch of the mandibular division of the trigeminal nerve. This is a useful example of fibres originating in one cranial outflow and travelling for their last segment with another nerve.[ref]
Glossopharyngeal Nerve by Complete Anatomy. Branches; Supplied Structures: tympanic plexus, lesser petrosal and parotid pathway
The branch to stylopharyngeus is motor; contraction elevates and expands the pharynx during swallowing. Pharyngeal branches contribute to the pharyngeal plexus, together with the vagus nerve and sympathetic connections. The principal motor supply of the pharyngeal constrictors is vagal: membership of a mixed plexus does not justify assigning every fibre or every pharyngeal muscle to the ninth nerve. Tonsillar branches supply the palatine tonsil and neighbouring mucosa. Lingual branches carry ordinary sensation and taste from the posterior third of the tongue, including the vallate papillae even though these lie just anterior to the terminal groove.
The carotid sinus nerve carries information from pressure-sensitive endings in the carotid sinus and from the carotid body's chemical sensors. The first contributes to regulation of blood pressure; the second responds especially to arterial oxygen deficiency, with responses also influenced by carbon dioxide and acidity. These are afferent functions, distinct from the motor and secretory branches.[ref]
Neuroanatomy, Cranial Nerve 9 (Glossopharyngeal) (StatPearls). Structure and Function; Nerves: distribution and sensory branches
In the modern central account, branchial motor fibres arise from the nucleus ambiguus, parasympathetic fibres from the inferior salivatory nucleus, visceral and taste afferents project towards the solitary nucleus, and relevant general sensory fibres project to the spinal trigeminal system. These nuclear and reflex distinctions refine the gross anatomical description available in 1864. Pharyngeal touch can initiate swallowing and contributes to the afferent limb of the gag reflex, whose principal motor limb is vagal. Ordinary sensation, taste, pharyngeal movement and secretion therefore need separate observations; the absence of one response does not by itself prove loss of every ninth-nerve function.[ref]
Cranial Nerves IX and X in Clinical Methods. Basic Science; examination of pharyngeal sensation, movement and reflexes
Original question.
What properties must a substance possess to justify you in speaking of it as a “Food ?” Classify such substances.
A food supplies material or usable chemical energy that contributes to the organism's maintenance, growth or normal function after ingestion and physiological processing. It must be usable in the amount and form supplied, without its harmful effects defeating that nutritive role. Mere combustibility, a pleasant taste, or the presence of carbon and nitrogen is insufficient.
An edible material may need digestion before its constituents can be absorbed. A protein need not enter the blood unchanged to nourish: hydrolysis supplies absorbable amino acids. Conversely, a substance can burn in a laboratory yet furnish little accessible energy to human metabolism. The nutritional value of a mixture depends on availability, proportions and the organism consuming it. No requirement says that each separate food must contain every constituent of a complete diet.
A useful nineteenth-century division separates nitrogenous or plastic foods from non-nitrogenous or respiratory foods. The first includes animal and plant proteins, which supply amino acids for tissue renewal. The second includes carbohydrates and fats, whose oxidation supplies much of the body's energy. But the division is functional rather than absolute: proteins can also be oxidized, and lipids and carbohydrates supply material for cellular structures as well as fuel. The modern account follows anabolism and catabolism rather than assigning each class one exclusive destination.[ref]
24.1 Overview of Metabolic Reactions. Anabolic and Catabolic Reactions: synthesis, breakdown and energy transfer
A fuller classification includes proteins; carbohydrates, including sugars and starch; lipids, including fats and essential fatty components; water; and required mineral constituents. Water provides solvent, transport medium and a participant in many reactions. Mineral constituents supply, among other needs, ions for electrical and osmotic functions and material for mineralized tissues. Neither class has to supply combustible energy to be indispensable. Meat, milk, grain and legumes are mixtures spanning several classes, rather than chemically pure examples of just one.
In modern classification, vitamins and other required micronutrients must also be included. Their specific deficiency roles and present classification should not be attributed wholesale to 1864. Dietary fibre is not equivalent to digestible starch; it can have important intestinal functions, and fermentable fractions can contribute metabolites through the microbiota. The adequacy of a diet concerns the whole combination of nutrients and the person's requirements, not a single measure of heat released on burning it.[ref]
24.7 Nutrition and Diet. Macronutrients; Vitamins; Minerals: energy-yielding and non-energy-yielding nutritional requirements
Oxygen is essential to ordinary aerobic life, but in the usual dietary sense it is a respiratory input rather than an ingested food class. Likewise, a drug that changes appetite or stimulates a physiological response is not thereby a substitute for nutritive material. A convincing experiment on food value must distinguish failure to eat, failure to digest or absorb, and a genuine missing dietary constituent; maintaining equal gross food mass alone does not control those differences.
Original question.
Plants generally incorporate combined nitrogen into organic compounds, whereas animals eliminate the surplus nitrogen of metabolized compounds chiefly as Ammonia, urea or uric acid. The two processes connect nitrogen chemistry to the organism's carbon supply, water economy and environment.
Roots take up nitrate and ammonium from their surroundings. Nitrate must be reduced before its nitrogen can be incorporated in the usual amino form: nitrate reductase produces nitrite, and nitrite reductase produces ammonium. The balanced reduction, written without implying a single elementary reaction, isReducing equivalents and energy must be supplied by metabolism; nitrate is not simply deposited unchanged inside every protein.
In the modern biochemical account, glutamine synthetase incorporates ammonium into glutamine, using ATP; glutamate synthase transfers that nitrogen to a carbon skeleton derived from 2-Oxoglutarate, producing glutamate. Further transfer and synthesis distribute nitrogen into other amino acids, proteins, nucleotides and other cell constituents. Carbon metabolism therefore provides both energy and skeletons for nitrogen assimilation. These named enzymes and reactions explain the process today; they were not a completed molecular scheme in 1864.[ref]
Nitrogen uptake, assimilation and remobilization in plants. Nitrogen Assimilation: nitrate reduction and the GS/GOGAT cycle
Ordinary higher-plant cells do not themselves reduce atmospheric molecular nitrogen merely because the gas surrounds the leaves. Biological nitrogen fixation is performed by particular microorganisms; symbiotic associations can supply fixed nitrogen to a host plant. The later elucidation of root-nodule symbiosis should be distinguished from what the examiner could have expected. Organic nitrogen can also be taken up in suitable circumstances, so nitrate and ammonium are important routes rather than an exhaustive prohibition on every other source.[ref]
46.3 Biogeochemical Cycles. The Nitrogen Cycle: fixation, ammonification, nitrification and return to the atmosphere
A useful assimilation experiment grows comparable seedlings in a defined medium containing all required minerals except combined nitrogen, with parallel nitrate- or ammonium-supplied cultures. Initial seed reserves, contaminating nitrogen, water and microbial growth must be allowed for. Growth and final nitrogen content are more informative than green appearance alone. A plant initially growing in a nitrogen-free solution may simply be consuming seed reserves; that observation does not demonstrate fixation of atmospheric nitrogen.
Animals obtain most of their nitrogen from organic food. Amino acid metabolism separates nitrogen handling from oxidation or reuse of the carbon skeleton. Free Ammonia is toxic at high concentrations, and mammals convert much of their waste nitrogen into urea in the liver; the kidneys then eliminate it in urine. Uric acid is also produced from purine breakdown. Renal ammonium excretion has a separate important connection with acid-base balance. Urea formation and urinary excretion are different processes in different organs.[ref]
Many aquatic animals can release Ammonia directly into abundant surrounding water. Birds, many reptiles and many insects eliminate much nitrogen as relatively insoluble uric acid, conserving water; mammals generally depend more on soluble urea. These are broad physiological strategies with exceptions, not a rule that all animals have human urine. Faecal nitrogen includes unabsorbed food as well as endogenous material, while smaller losses can occur through skin and secretions. For a stated interval the accounting identity isPositive retention during growth and negative balance during tissue loss need not be errors of excretion. Nitrogen is redistributed or lost in compounds; it is not simply breathed out as all the atmospheric nitrogen passing through the lungs.
Original question.
What are the microscopic appearances presented by the more common varieties of Starch, and in what do their Chemical reactions differ from those of Dextrin and Inulin ?
Starch granules can often be distinguished by their shape, size distribution, hilum and lamellae; dextrin and inulin are distinguished chiefly by their molecular constitution, solubility and chemical reactions. An isolated particle of uncertain origin cannot always be identified uniquely by one feature.
In a water-mounted preparation of unheated starch, potato granules are usually relatively large, oval or pear-shaped, often with an eccentric hilum near the narrower end and conspicuous curved growth markings. Wheat gives a characteristic mixture of larger flattened lenticular granules and small rounded granules; the hilum and rings are less conspicuous. Rice starch consists of very small angular or polyhedral granules, often still associated into compound groups. These are distributions rather than a guarantee that every potato granule is larger than every wheat granule.[ref]
Starches in The International Pharmacopoeia. Microscopic identification: potato, wheat and rice granule shape, hilum and striations
Maize commonly gives polygonal or rounded granules with a central point or fissured hilum; oats characteristically include aggregates of small angular granules. Arrowroot commonly has oval or elongated granules, sometimes with a transverse fissure towards one end. Preparation, variety and processing change the apparent population. Rotation between crossed polarizers shows the organized granule structure through a characteristic extinction cross in many intact granules. Swelling and loss of birefringence on heating with sufficient water help demonstrate starch gelatinization, although the precise temperature depends on the starch source.
Cold water normally leaves native starch granules as a suspension rather than a clear molecular solution. On heating, granules swell and a paste develops. With iodine in iodide solution, ordinary starch rich in sufficiently long amylose helices produces an intense blue or blue-black complex. Its intensity depends on chain structure and conditions; the response can weaken on heating and return on cooling if the chains remain suitable. Continued acid or enzymatic hydrolysis shortens chains and eventually destroys this characteristic blue response.
Dextrin denotes a range of shorter or modified glucose polymers derived from starch, rather than one pure substance. Many preparations dissolve or disperse in water more readily and no longer show intact native granules. Their iodine reactions vary with chain length: some give violet or reddish-brown colours, while extensively shortened material gives no characteristic colour. It is therefore too absolute to say that every dextrin is chemically identical or that no dextrin can react with iodine. The modern international specifications themselves distinguish starch modifications and their variable iodine colours.[ref]
Dextrins in MeSH. Definition: mixtures of glucose polymers produced by starch or glycogen hydrolysis
[ref]Modified Starches: Specifications by the Joint FAO and WHO Expert Committee on Food Additives. Identification; iodine colours and hydrolysis test in the specifications summary
Inulin is principally a fructose-based fructan, with a different linkage pattern from glucose-based starch. It occurs, for example, in chicory and related storage organs. It does not give starch's blue iodine complex. It dissolves more readily in hot water, and may separate as deposits on cooling or precipitation, but such deposits are not the characteristic native starch granules. Hydrolysis yields mainly fructose, whereas complete starch or dextrin hydrolysis yields glucose. A copper-reduction test after hydrolysis detects reducing products in both cases and is therefore insufficient by itself to distinguish them. Their different hydrolysis products, interpreted with iodine reaction and microscopy, give a more specific comparison.[ref]
A sound comparison uses separately labelled reference preparations, equal iodine conditions and separate unheated and heated mounts. Inspecting an unknown mixture only after boiling destroys much of the morphological evidence. The combined observations distinguish source-related morphology from the effects of processing.
Original question.
A seven-month fetus is recognizably human in its formed organs and external parts but remains immature in fat stores, respiratory function, temperature control and feeding coordination. The month count must be stated: calendar months, four-week obstetric months and time since conception are not interchangeable.
A useful modern benchmark is around 28 completed gestational weeks, counted from the last menstrual period, about two weeks more than the usual time since fertilization. At that stage a typical crown-to-heel length is about 38 cm and mass about 1 kg, with substantial normal variation. Those are illustrative modern averages, not measurements of a particular fetus or exact historical thresholds for a seventh month. A historical count from conception would place the same numerical week count later in modern gestational dating.[ref]
Week 28 of Pregnancy by the NHS. What does my baby look like? Crown-to-heel length at 28 gestational weeks
[ref]Week 28 of Pregnancy by HealthLink BC. How your baby is changing: approximate mass, eyelid opening and developing fat
The body is slender compared with a term newborn because subcutaneous fat is still limited. The skin is relatively thin and reddish, with wrinkles, lanugo and a variable covering of vernix caseosa. Hair and nails are present but their growth and the firmness of the ear cartilage remain immature. The eyelids have separated and can open around this period; this should not be confused with adult visual acuity or fully mature pupillary responses. Limb movements occur, but sustained flexor posture and coordinated behaviour are less developed than at term.[ref]
Developmental Care Guideline by NHS Greater Glasgow and Clyde. Developmental characteristics at 23–27, 28–31 and 32–35 weeks: skin, posture, movement and eye responses
The major organs are present, yet their organization and functional reserve continue to mature. The brain is growing rapidly and its surface folding increases. The lungs are developing gas-exchanging regions and pulmonary surfactant production, but an early birth can still entail serious respiratory difficulty. Fetal respiratory movements do not demonstrate that the lungs are already performing ordinary air breathing: before birth the placenta supplies gas exchange. Fetal circulation still includes its characteristic shunts. Genital appearance and testicular descent, when relevant, can contribute to maturity assessment but do not provide a precise independent calendar.
Survival after birth is possible, especially with current neonatal support, but viability is a probability conditioned by maturity, circumstances and available care, not a switch thrown on one date. Modern intensive-care results must not be represented as outcomes achievable in 1864. Nor is there a physiological rule that a healthy eight-month fetus is intrinsically less viable than a seven-month fetus. A description of several concordant maturity features is more defensible than assigning an exact age or prognosis from size alone.
Original question.
Give a short account of the several substances known as Hæmatocrystallin, Hæmatoidin, Hæmatin, Chlorophyll, Biliverdin, Taurin, Excretin, Glycogen, Gluten, Legumin.
These names refer to several unrelated chemical classes: blood and bile pigments, a photosynthetic pigment family, an amino sulfonic acid, a disputed historical faecal extract, and storage polysaccharides or proteins. Similar colour or a historical name does not establish chemical identity.
Haematocrystallin denotes the crystallizable colouring substance of red blood, now identified with hemoglobin. It combines a globin protein with iron-containing haem groups. Within intact red cells it reversibly binds oxygen; oxygenated and deoxygenated forms have different absorption spectra. Crystals obtained from blood differ with species and preparation. This is not the same thing as a crystal formed from an old tissue haemorrhage. The word does not mean that all circulating blood normally consists of free pigment crystals.[ref]
Haematoidin is the yellow-orange to reddish pigment characteristically encountered in old extravasated blood, sometimes as rhomboidal crystals or radiating clusters. It is associated with bilirubin and lacks the iron retained in haemosiderin. The historical inference that any reddish blood-derived crystal must be the same substance as haematocrystallin is therefore wrong. In a tissue preparation the local matrix and other constituents can complicate an exact chemical identification from appearance alone.[ref]
Hematoidin crystals in sputum smears: Cytopathology and clinical associations. Results; Discussion: crystal morphology, bilirubin association and absence of iron
Haematin is a dark iron-containing derivative of haem, obtained when the globin association and the iron's chemical environment are altered. In modern chemical usage, hematin is the ferric hydroxide form of the haem pigment; hemin is the corresponding chloride form. Historical preparations and terminology were less consistently separated. Neither should be equated with iron-free bilirubin, and a haem-derived crystal test is not the crystallization of intact hemoglobin.[ref]
Hematin in PubChem. Identity and chemical description: hydroxyl ferric protoporphyrin
[ref]Chlorophyll is the green pigment system of photosynthetic organisms, present in organized pigment-protein assemblies in chloroplasts in green plants. Modern chemistry distinguishes several chlorophylls: chlorophyll a, for example, has a magnesium-containing tetrapyrrolic ring system and a hydrophobic side chain. It absorbs light used in photosynthetic energy conversion. Extraction into alcohol can reveal the green pigment, but a leaf extract is a mixture rather than a chemically pure universal chlorophyll. Its green colour must not be attributed to iron in the same way as haem.[ref]
Biliverdin is a green, open-chain tetrapyrrolic pigment. In modern haem catabolism, ring cleavage by haem oxygenase releases iron and forms biliverdin; reduction then produces bilirubin. The pigments contribute to changing colours of some resolving haemorrhages and to bile-pigment chemistry. This sequence concerns degradation of the haem group, not conversion of the entire globin protein directly into one green molecule.[ref]
Taurin, now taurine, is a colourless crystalline amino sulfonic acid with the structure . It contains sulfur and nitrogen and can form conjugates with bile acids, including taurocholic acid. It is not itself a green bile pigment, an ordinary carboxylic amino acid, or a standard amino acid directly inserted into proteins by translation. The chemical classification and formula distinguish it from neighbouring names in the list.[ref]
Excretin was the name William Marcet gave to a crystalline material extracted from human faeces. His contemporary account describes treatment with hot alcohol, removal of material with lime, extraction with ether, and formation of silky needle-like crystals; the material was insoluble in water, soluble in ether and hot alcohol, and melted in the low-to-mid 90s Celsius. His 1859 account reports carbon, hydrogen, oxygen and sulfur and gives an equivalent-weight formula based on an assumed sulfur content. These are historical analytical claims, not a modern authenticated molecular specification. Later work questioned the purity and chemical individuality of excretin, so that old name alone does not establish a definite modern structure.[ref]
Excretin in A Text-book of Physiological Chemistry (1914). p. 523: later doubts about identity and possible impure sterol material
[ref]Glycogen is an animal glucose-storage polysaccharide, particularly important in the liver and skeletal muscles. Its highly branched chains contain alpha-(1→4) links with alpha-(1→6) branch points. Preparations form opalescent dispersions and commonly show a reddish-brown iodine reaction rather than the intense blue associated with long amylose chains. Hydrolysis yields glucose. Liver glycogen can support the regulation of circulating glucose, whereas muscle glycogen mainly supports local muscle metabolism; a modern account must distinguish those physiological destinations.[ref]
Biochemistry, Glycogen (StatPearls). Introduction; Cellular Level: glucose storage, branching and distinct liver/muscle roles
Gluten is the cohesive protein-rich material left when wheat dough is washed to remove much of its starch. It is not a single small molecule: modern analysis distinguishes gliadin and glutenin families whose associations contribute extensibility and elasticity. It is poorly soluble in water as a dough network, contains nitrogen, and on full hydrolysis supplies amino acids. Its nutritive role is that of a plant protein mixture, not a nitrogen-free carbohydrate.[ref]
Changes in the rheology and aggregation behavior of wheat glutenin and gliadin mediated by low-sodium salt. Introduction; experimental comparison of the rheology of the two protein fractions
Legumin is a seed storage globulin associated particularly with peas and related legumes. A classical preparation extracts protein into suitable dilute salt solution and precipitates it under changed conditions. Modern legumins are 11S globulin assemblies, often hexamers formed from processed subunits. They are nitrogen-containing proteins, chemically distinct from starch despite occurring beside it in a seed. The older name vegetable casein indicates an analogy of precipitation or nutritive role; it does not establish identity with milk casein.[ref]
Pea Legumin Overexpressed in Wheat Endosperm Assembles into an Ordered Paracrystalline Matrix. Abstract; results on precursor processing and 11S hexamer assembly
Original question.
Both the aorta and a vena cava have an endothelial lining and three broadly corresponding tunics; the aorta is dominated by an elastic muscular media, whereas a caval vein has a relatively thin media and a prominent collagenous adventitia. Their appearance reflects their different mechanical conditions, not simply the oxygen content of their blood.
The tunica intima of each begins with a continuous endothelium on its basement membrane, supported by subendothelial connective tissue. A normal section must be distinguished from age-related or pathological thickening. In the aorta, the intima merges towards a very thick tunica media. Unlike a typical muscular artery with one conspicuous internal elastic boundary, an elastic artery contains so many elastic lamellae that selecting one line as the uniquely dominant elastic membrane is less useful.
The aortic media contains repeated, approximately concentric fenestrated elastic lamellae, with smooth muscle cells, collagen and other matrix components between them. The elastic elements extend during ventricular ejection and recoil between beats; smooth muscle participates in matrix maintenance and regulation of wall properties. The outer tunica adventitia contains collagen, elastic fibres, nerves and vasa vasorum. Those small vessels serve the outer wall, which is too thick to be supplied entirely by diffusion from luminal blood.[ref]
Blood Vessels in the Histology Guide. Slides MH 065 and MH 066, aorta: elastic lamellae, smooth muscle and outer wall
A vena cava has a wide lumen relative to its wall and is easily distorted or collapsed in a fixed empty preparation. Its intima is relatively thin. The media contains fewer circular smooth-muscle and elastic elements than the aortic media and is much less dominant. Its adventitia is often the thickest coat, with substantial collagen, elastic tissue and conspicuous longitudinal bundles of smooth muscle, particularly in the inferior vena cava. The relative amount varies with the sampled caval region; a thin-walled vein must not be described as a vessel without any muscle. Vasa vasorum and nerves occur in its outer wall too.[ref]
20.1 Structure and Function of Blood Vessels. Shared Structures; Arteries; Veins: tunics, elastic arteries and venous wall proportions
Ordinary peripheral venous valves are folds of intima, but a valve is not a necessary feature of every large vein or every caval section. The aorta likewise has no series of valves distributed down its wall; the aortic valve is at its cardiac origin. Thus two circular profiles alone should be compared by wall organization, not diagnosed by assuming the vein must display a valve.
An elastic-fibre stain makes the aortic lamellae conspicuous, while ordinary stained sections show nuclei and the relative distribution of muscle and connective tissue. A transverse section cuts longitudinal caval muscle bundles across, whereas a longitudinal section displays their length; recognizing orientation prevents confusing those bundles with glands or isolated cellular nodules. The low-pressure, highly compliant venous reservoir and the pressure-bearing elastic arterial conduit are consequently different uses of the same broad tissue classes.
Original question.
What conditions necessarily follow, what are known to modify powerfully the working of Apnæa ?
Sustained failure of respiratory gas exchange progressively depletes usable oxygen and impairs elimination of carbon dioxide; its rate and visible effects depend strongly on the cause, initial stores, metabolism and remaining circulation. Here the historical apnæa is best read in its broad sense of suspended respiration and resulting asphyxial danger, rather than as one precisely defined modern sleep disorder.
Contemporary usage supports that reading: an 1858 review of Marshall Hall's work explicitly joins drowning with other forms of apnoea or suspended respiration. An airway obstruction, drowning, absence of respiratory drive and failure of the respiratory apparatus can all interrupt effective ventilation, although they add different injuries. The historical label does not prove a single mechanism in every case.[ref]
Prone and Postural Respiration in Drowning, and Other Forms of Apnoea (review, 1858). Opening title and pp. 289–293: suspended respiration, airway obstruction and postural experiments
When ventilation stops while ordinary blood circulation and metabolism continue, alveolar oxygen is consumed and arterial oxygenation falls. Carbon dioxide usually accumulates, with rising acidity; falling oxygen delivery then impairs ATP production and especially threatens the brain and heart. A conscious person may develop air hunger and vigorous respiratory efforts, followed in severe progression by impaired consciousness, gasping and loss of effective circulation. The sequence and colour changes are variable: cyanosis, convulsions or a particular pulse pattern are not individually necessary in every cause of oxygen deprivation. If circulation has already stopped, simple arterial-gas descriptions no longer capture tissue delivery.
The distinction between hypoxia and hypercapnia is important. Oxygen-free inspired gas can cause profound hypoxia while carbon dioxide is still exhaled; complete airway obstruction commonly produces both. Modern experimental comparisons show that oxygen deficiency and raised carbon dioxide interact in stimulating ventilation. One cannot assign all consequences to a single poisonous property of retained carbon dioxide.[ref]
Chemical Control of Breathing. Asphyxia; interactions of oxygen, carbon dioxide and acidity in ventilatory drive
The time course changes with the initial oxygen store in the lungs and blood, the amount of oxygenated blood still reaching tissues, and the rate at which tissues consume it. Exercise, fever and struggling can accelerate depletion; a lower metabolic rate can slow it. Temperature has several competing effects, so cold exposure is not a general guarantee of protection. Pulmonary volume, haemoglobin concentration, existing lung disease, airway patency and circulatory failure all change the relation between an interruption and tissue injury. Duration matters, but the same duration is not physiologically equivalent in every person and every mechanism.
A rough explanatory relation isIt is an accounting guide, not a safe breath-holding limit or a formula for predicting irreversible injury. A modern laboratory analysis could record gas concentrations, respiratory movement, flow and circulation separately; visible chest movement alone does not demonstrate airflow through an obstructed airway.
Modern apnoea can also mean a temporary absence of respiratory effort, for example after a fall in arterial carbon dioxide following hyperventilation. That narrower phenomenon must not be confused with every use of the historical word. Hyperventilation does not reliably create a large extra oxygen reserve in an already oxygenated person, and delayed air hunger is not proof that oxygen supply remains adequate. Historical postural resuscitation experiments illustrate why airway patency and actual ventilation were distinguished; their methods should not be presented as current clinical instructions.
Original question.
Rigor mortis is a temporary postmortem loss of muscular extensibility caused principally by depletion of ATP and persistent actin–myosin attachment. Its onset, intensity and disappearance depend on the previous state of the muscle and its environment; it is not a fixed clock.
After an initial period of relaxation, surviving muscle metabolism briefly maintains some ATP. When supplies and regeneration fail, cross-bridges cannot detach normally, while disturbed calcium handling facilitates attachment and tension. The resulting stiffness is a local physicochemical change in muscle, not a continuing voluntary contraction and not evidence that its motor nerves remain alive. Later degradation of muscle structures removes the rigidity. This ATP-dependent explanation is modern; an 1864 answer could describe observations and their dependence on muscular condition without possessing the present cross-bridge model.[ref]
Postmortem Changes (StatPearls). Rigor mortis: ATP depletion, calcium disturbance and eventual secondary relaxation
Prior exertion, prolonged convulsive activity, fever or exhausting disease can leave smaller energy reserves and alter the interval before stiffness becomes evident. Starvation, wasting, age and muscle mass can influence how pronounced it appears. A well-nourished resting muscle and an exhausted muscle need not behave alike after death. Cause of death matters through such conditions, through temperature, and through injury or chemicals affecting muscle metabolism; a named cause alone does not impose one universal timetable.
Warm conditions generally hasten biochemical changes, often bringing earlier rigor and faster subsequent loss through decomposition. Cooling generally slows the overall sequence and can prolong its persistence. There are qualifications: muscle shortening caused by low temperature before rigor, freezing of tissue, and heat-induced protein coagulation are not interchangeable with ordinary rigor. Controlled muscle experiments measuring extensibility, pH, temperature and ATP demonstrate that shortening and completed rigor need not occur at the same stage.[ref]
The influence of temperature on shortening and rigor onset in beef muscle. Abstract: controlled temperature, pH, ATP and separation of shortening from loss of extensibility
The stiffness becomes noticeable unevenly because muscles differ in size, condition and the way their resistance is tested. The customary progression from small facial and jaw muscles to larger limb groups is a practical generalization, not a biological wave proving that all other muscles were chemically unchanged until reached. Mechanical movement can break established resistance in a region, and the later appearance depends on how far the underlying process had progressed. Repeated manipulation therefore changes what the observer is trying to use as evidence.
A defensible observation records the environment, body condition, which anatomical joints resist passive movement, whether the resistance is local or widespread, and evidence of decomposition. It is interpreted alongside other observations rather than converted into an exact elapsed time. Rigor alone cannot establish an exact elapsed time.
Original question.
The ciliary muscle forms a ring within the anterior ciliary body, deep to the sclera and outside the zonular attachment system of the crystalline lens. Its arrangement connects an anterior scleral attachment to posterior and inward parts of the uveal tissues, allowing contraction to alter zonular tension.
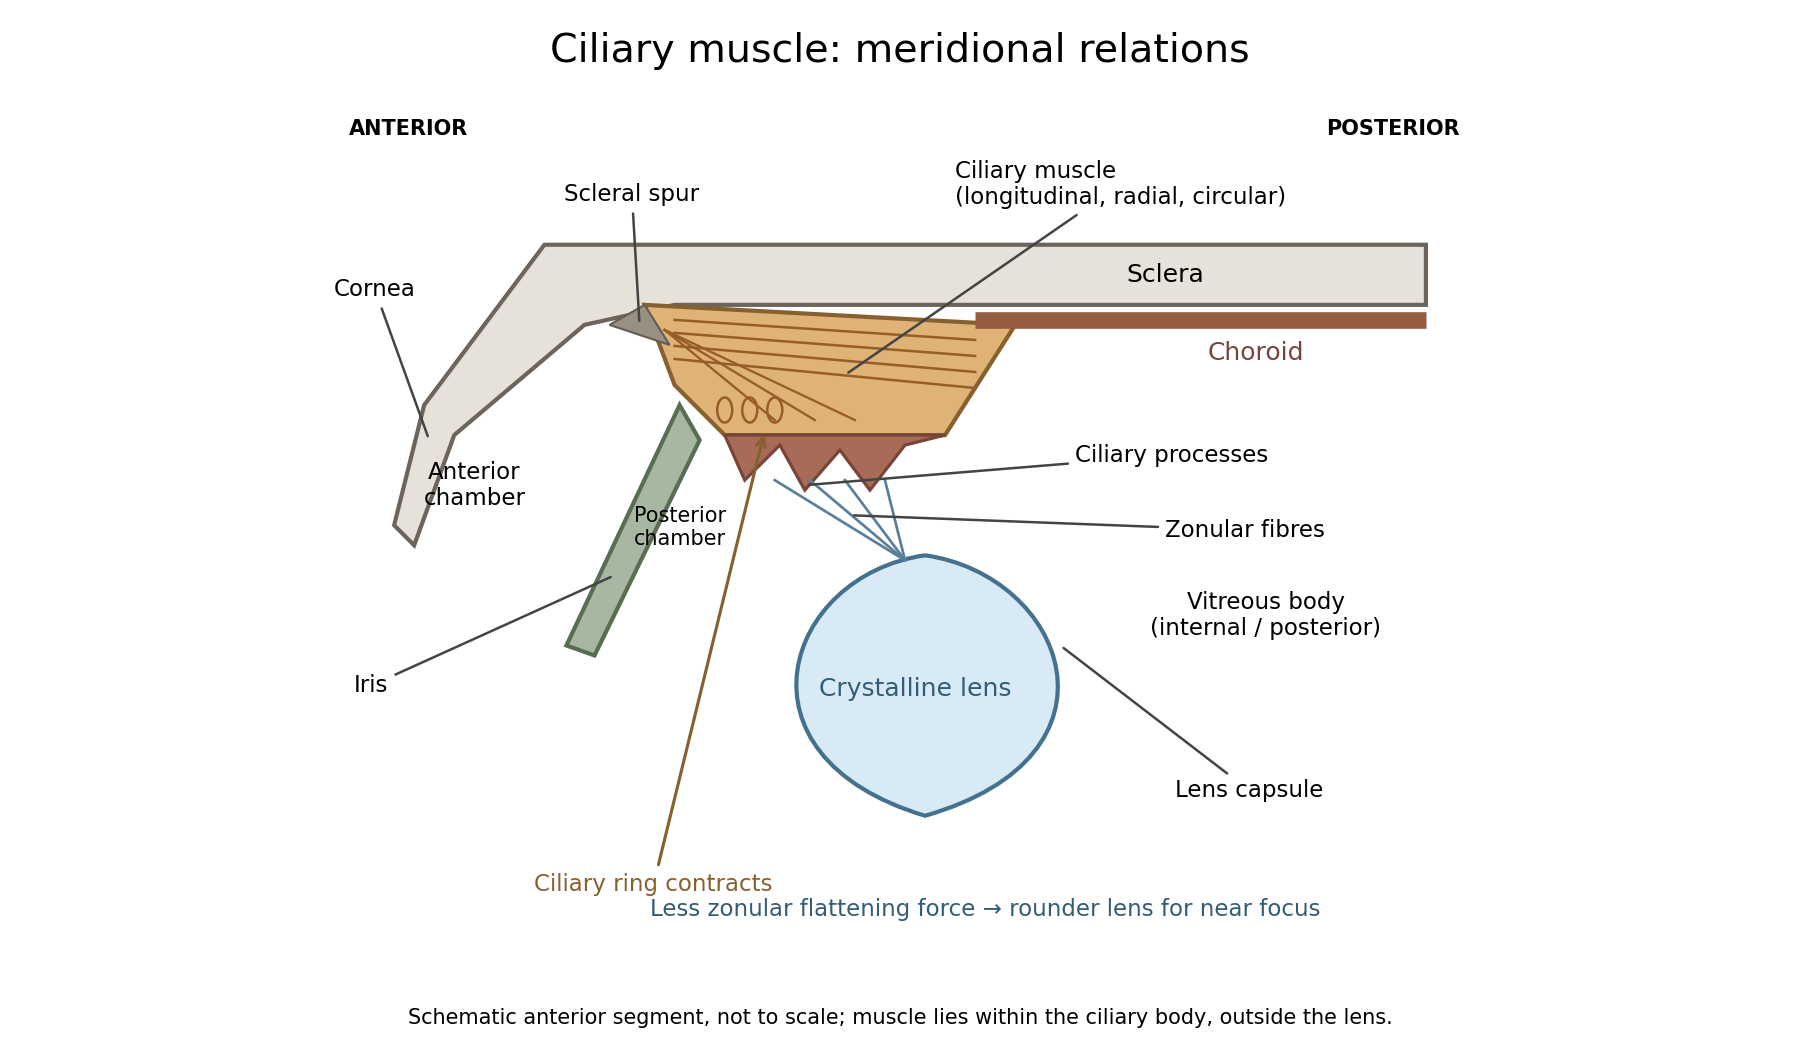


In a meridional section, the anterior ciliary region lies just behind the corneoscleral junction. The scleral spur gives attachment to anterior longitudinal muscle fibres. Posteriorly these fibres extend towards the choroid and its supporting tissues. Between the sclera outside and the ciliary processes inside, oblique or radial and circularly oriented smooth-muscle bundles complete the muscular mass. These fibre directions are regions of one coordinated smooth muscle, not three independently attached external ocular muscles.[ref]
Anatomy of the Angle by the American Academy of Ophthalmology. Scleral Spur: longitudinal ciliary-muscle attachment and relation to trabecular tissues
The ciliary processes project inward from the anterior folded part of the ciliary body, behind the root of the iris and peripheral to the lens equator. Ciliary epithelium covers them; their vascular core and epithelial functions are distinct from the smooth-muscle bundles. The posterior, flatter ciliary region continues towards the ora serrata, where the sensory retina ends. The ciliary body is therefore continuous with choroid posteriorly and related to iris anteriorly, while remaining a separately describable region.
Zonular fibres pass from the ciliary region to the capsule around the equator of the crystalline lens. They cross the circumlental space; the ciliary muscle does not insert directly into the transparent lens substance. The posterior chamber lies behind the iris and in front of the lens and zonular apparatus, and communicates with the anterior chamber through the pupil. The vitreous body lies behind the lens and has its own relation to the posterior zonular region. These spaces must not be drawn as one cavity containing the muscle freely suspended in aqueous fluid.
For near ocular accommodation, contraction reduces the effective diameter of the ciliary ring and changes its position, reducing the zonular forces that flatten the lens. The elastic capsule and lens substance then permit a rounder lens with greater optical power. For distant viewing, relaxation restores greater flattening tension and lower power. Thus ciliary contraction increases lens curvature by relieving a restraint; it does not pull the lens flatter. The conventional mechanism is supported by observations of lens shape and optical changes during accommodation.[ref]
Physiology, Accommodation (StatPearls). Cellular Level; Mechanism: contraction, zonular tension and lens thickening
Parasympathetic motor fibres reach the muscle through the oculomotor nerve, ciliary ganglion and short ciliary nerves. This motor pathway is distinct from the sensory visual input that initiates a near response. Changes in pupil size and convergence often accompany accommodation, but neither should be substituted for an observed change of lens power. With age, reduced lens deformability can impair near focus even though ciliary contraction still occurs. The sketch shows spatial relationships and the direction of the conventional mechanism, rather than a scale drawing or a claim that every historical theory of accommodation was correct.
Original question.
Give the Natural History of some venomous animal, or of some parasite, to the attacks of which our own species is subject.
Ascaris lumbricoides provides an example of a human parasite: the adult is an intestinal roundworm, while its infective stage is an embryonated egg acquired from a contaminated environment. The account below gives the established modern life cycle; its full migratory detail should not be assumed to have been demonstrated by December 1864.
The adult is elongated, cylindrical and unsegmented, with a tapering body, a tough cuticle and a mouth bordered by three prominent lips. Sexes are separate. The female is generally larger; the male has a characteristically curved posterior end. Their form distinguishes them from segmented tapeworms and from an earthworm, despite superficial resemblance at a distance. Adults occupy the lumen of the small intestine, obtaining nourishment in the host's intestinal environment.
Females pass large numbers of eggs into the intestinal contents, and the eggs leave in faeces. Fertilized eggs have a thick shell, commonly with an outer mammillated coat; the coat may be absent in a decorticated egg. Unfertilized eggs have a different appearance and do not develop into the infective stage. Warmth, moisture, shade and time permit larval development inside suitable fertilized eggs. Freshly passed eggs are therefore not equivalent to fully developed infective eggs.[ref]
DPDx: Ascariasis. Causal Agents; Life Cycle; fertilized, unfertilized and decorticated egg descriptions
After an infective egg is swallowed, a larva hatches, crosses the intestinal mucosa and reaches the liver and then the lungs through the circulation. It enters the pulmonary air spaces, ascends the bronchial tree to the throat, and is swallowed. Back in the small intestine, it develops into an adult and completes the cycle. No intermediate insect, fish or mammal is required for this human roundworm cycle.[ref]
Ascariasis in MedlinePlus. Causes: intestinal hatching, pulmonary migration, swallowing and adult development
Development in the outside environment helps explain why ordinary immediate contact with newly passed faeces is not the same exposure as swallowing mature eggs from contaminated soil.The migrating larva and the adult affect different tissues. Many light intestinal infections are asymptomatic, whereas heavy burdens can impair nutrition or obstruct the intestine; wandering adults can enter biliary passages. Larval migration can produce respiratory inflammation. These effects arise from particular stages and burdens, not from venom injected by a biting organ. Eggs in a suitable stool preparation and the morphology of an expelled adult provide different kinds of identifying evidence; an early migratory infection need not yet supply eggs in stool.[ref]
About Ascariasis by the Centers for Disease Control and Prevention. Overview; Symptoms; Causes: intestinal adults, environmental transmission and pulmonary manifestations
The natural history explains prevention: separating human waste from food and water and limiting contaminated-soil ingestion interrupt transfer of eggs. It also explains why a household observation of a worm does not establish spontaneous generation inside the intestine. The absence of an intermediate host is compatible with a complex larval migration within the definitive host.
Articles by others on the same topic
There are currently no matching articles.