A hormone is a chemical messenger released by biological cells that regulates target biological cells bearing suitable receptors. In endocrine signaling, hormones travel to distant targets through the bloodstream. The extract-transfer experiment under second messenger isolates part of this signal transduction from intact biological cells. [ref]
https://openstax.org/books/biology-2e/pages/9-1-signaling-molecules-and-cellular-receptors. Clark, Douglas and Choi, Biology 2e, 9.1: hormonal signaling
A positive test for this hormone does not establish the location or continuing viability of a pregnancy.
An endogenous chemical regulator coordinating plant growth, development or environmental responses. Its effect depends on concentration, tissue and the receiving signal transduction network.
A class of plant signals with developmental roles and functions in the rhizosphere, including stimulation of arbuscular mycorrhizal fungal branching.
A family of growth-regulatory proteins whose degradation is promoted by gibberellin signaling. Direct interactions with phytochrome-interacting factors connect hormone status to light-regulated growth.
A class of plant growth regulators. Gibberellin perception can promote degradation of DELLA proteins, releasing constraints on selected growth responses.
A class of growth regulators whose synthesis, directional transport and perception help organize plant growth. A change in auxin abundance and a change in auxin sensitivity are distinct mechanisms.
Directional cell-to-cell transport of auxin. Transporter abundance, polarity and activity influence local hormone distribution.
A plant hormone involved in water-stress responses, seed dormancy and other processes. In guard cells, ABA-dependent receptor inhibition of phosphatases permits kinase activation and stomatal closure.
A hormone based on a steroid scaffold. Many act through an intracellular nuclear receptor to regulate gene expression.
A steroid hormone involved in physiological regulation and psychological stress responses. Interpretation depends on sampling time, baseline and the challenge being studied; a lower concentration is not automatically a measure of better psychological adaptation.
Adrenaline, also called epinephrine, is an endogenous catecholamine messenger: the body makes it and can release it into blood as a hormone. The adrenal medulla, the inner region of an adrenal gland, secretes adrenaline in response to sympathetic nervous system stimulation. A circulating hormone broadcasts a signal, but each receiving biological cell interprets it through its own receptors and intracellular machinery. Adrenaline activates both alpha-adrenergic receptors and beta-adrenergic receptors; it does not command one identical response everywhere.[ref]
Adrenal Gland by National Cancer Institute. Hormones of the Adrenal Medulla: secretion in response to sympathetic stimulation
[ref]Epinephrine MeSH descriptor by National Library of Medicine. Epinephrine, D004837: Scope Note, entry term Adrenaline and Catecholamines tree placement
Fuel mobilization is a useful example. A beta-adrenergic receptor can increase adenylyl cyclase activity through a stimulatory G protein, increasing the intracellular second messenger cAMP. Protein kinase A responds to cAMP; a phosphorylation relay through phosphorylase kinase activates glycogen phosphorylase, favoring glycogenolysis. Here adrenaline is the extracellular message, cAMP is the intracellular message, and glycogen is the reserve being mobilized. These are three different roles.[ref]
The regulatory component of adenylate cyclase. Purification and properties by P. C. Sternweis and others. Abstract, properties 2-4: purified guanine-nucleotide regulatory component reconstitutes hormone-stimulated adenylyl cyclase
[ref]An adenosine 3′,5′-monophosphate-dependant protein kinase from rabbit skeletal muscle by D. A. Walsh and others. Walsh, Perkins and Krebs, 1968, printed p. 3763 Summary and introductory paragraphs: cAMP-dependent kinase and phosphorylase kinase activation
[ref]Pharmacological Characterizations of Adrenergic Receptors in Human Adipocytes by Thomas W. Burns and others. Abstract, second paragraph: positive beta-receptor coupling to adenylyl cyclase
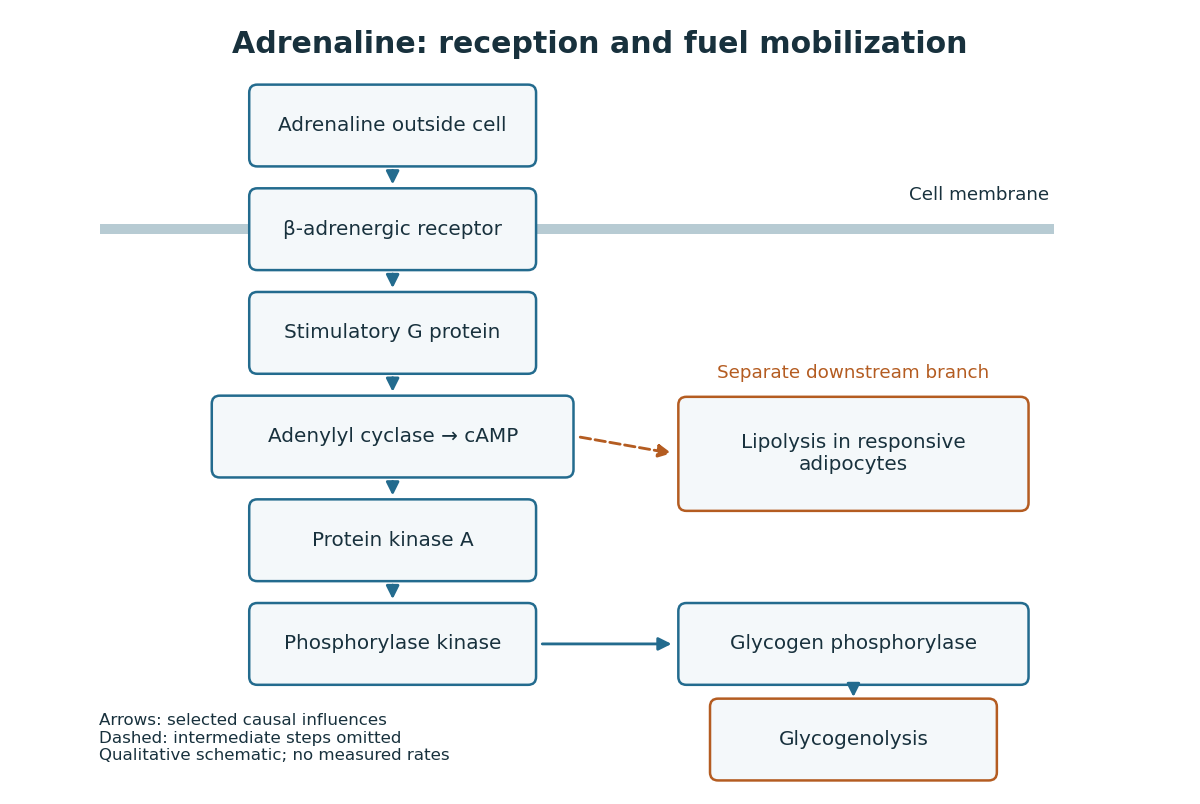
Adrenaline reception and cAMP-dependent fuel mobilization
. Original pathway schematic. Solid arrows show a selected activating relay to glycogenolysis; the dashed branch summarizes promotion of lipolysis in responsive adipocytes, omitting its intermediate steps. Arrows denote causal influences, not transport of adrenaline into the biological cell, reaction rates or measured yields. Details.
The two reserves provide different material. Glycogenolysis draws on glycogen; lipolysis breaks down stored triglycerides, releasing fatty acids and glycerol. A skeletal muscle biological cell's own reserve and fuel released by adipose tissue are different supplies. Increasing a signal cannot mobilize an empty reserve: receptor activation changes the use of available material rather than creating fuel. The adrenergic adipocyte assay below gives direct human evidence for the lipolysis branch.[ref]
Pharmacological Characterizations of Adrenergic Receptors in Human Adipocytes by Thomas W. Burns and others. Abstract: epinephrine-stimulated glycerol release as an index of lipolysis
Receptor context can even oppose this branch. In the human adipocyte preparation below, beta-adrenergic receptors promoted cAMP accumulation, whereas alpha-2 adrenergic receptors opposed it. Alpha-1 adrenergic receptors were associated with a different phospholipid readout. The balance of these responses matters more than the name of the messenger alone.[ref]
Pharmacological Characterizations of Adrenergic Receptors in Human Adipocytes by Thomas W. Burns and others. Abstract: opposing beta and alpha-2 coupling; separate alpha-1 phospholipid response
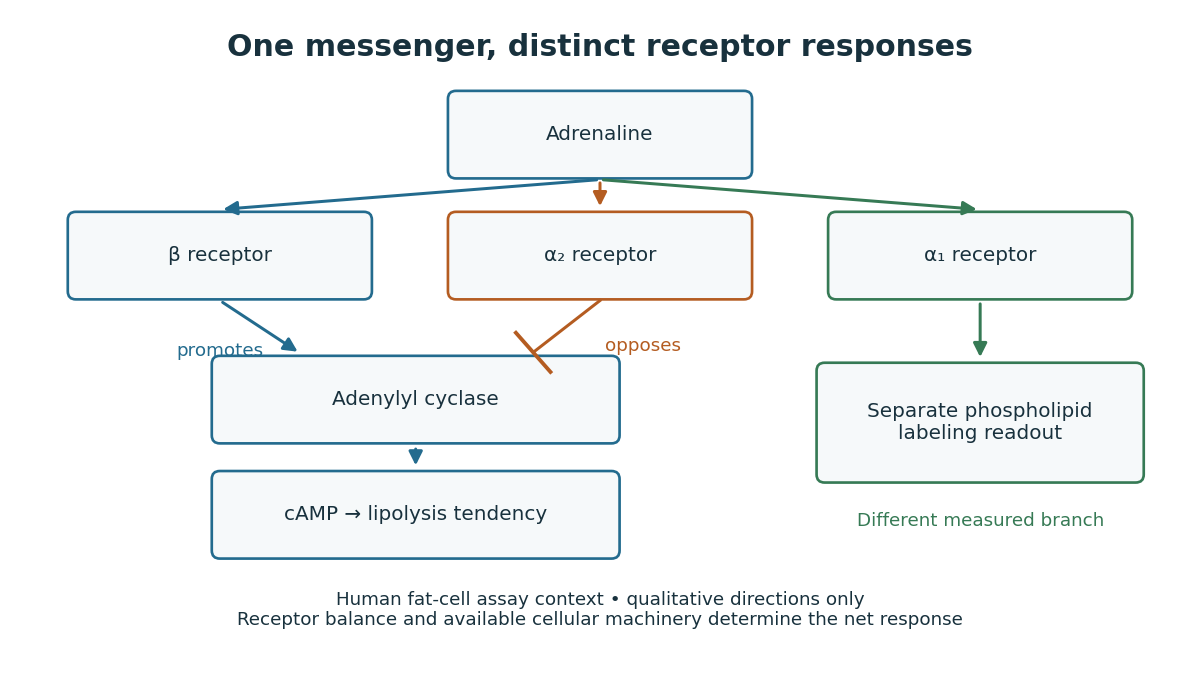

This separation is useful when explaining signal transduction: ask which receptor is present, which relay it controls, which reserve or target is available, and which response was actually measured. Receptor binding occupancy, second messenger production and final fuel release are distinct observations. A stronger cAMP signal need not imply an equally large change in every downstream process; substrate availability and the rest of the receiving biological cell still matter.
The extract-transfer experiment under second messenger supplies the earlier experimental separation between hormone reception and an intracellular intermediary. Its existing account includes the preparations and controls. The complementary adrenergic adipocyte assay asks a different question: can the same adrenaline stimulus engage opposing receptors within a human preparation?
In the 1981 study, investigators incubated human adipocytes or their cell membranes from fat near the abdominal lining with epinephrine. They combined detection of bound ligands by radioactive decay with biochemical readouts: adenylyl cyclase activity, cAMP and released glycerol. Blocking alpha-2 adrenergic receptors increased the epinephrine response; blocking alpha-1 adrenergic receptors did not. A separate labeled-phosphate incorporation readout in a phospholipid showed the reverse blocker sensitivity. Thus the comparisons separated response branches.[ref]
Pharmacological Characterizations of Adrenergic Receptors in Human Adipocytes by Thomas W. Burns and others. Abstract, first through fourth paragraphs: human properitoneal preparations, radioligand binding, biochemical readouts; yohimbine versus prazosin comparisons
The glycerol readout indicates lipolysis, rather than directly measuring whole-body fuel use. Isolated adipocytes omit circulation and nervous input; blocker selectivity also limits the inference. These comparisons support receptor-specific responses in that preparation, not identical behavior in all biological cells.
Glucagon is a peptide hormone made by alpha cells in the pancreatic islets. Its mature polypeptide has 29 amino acid residues. Alpha cells store glucagon in secretory granules and release it by exocytosis. Glucagon is a message about fuel availability; glucose is the sugar whose supply it helps regulate. A falling blood glucose concentration favors glucagon release, whereas a rise usually suppresses it. Amino acids can also stimulate release, so a meal containing protein need not produce the same hormone pattern as a meal dominated by carbohydrates. [ref]
The principal blood glucose-raising target is the liver. In a hepatocyte, the glucagon receptor is a G protein-coupled receptor: activation of a stimulatory G protein drives adenylyl cyclase, increasing the second messenger cAMP and activating protein kinase A. Downstream phosphorylation, including the phosphorylase kinase relay to glycogen phosphorylase, favors glycogenolysis. Glucagon also supports gluconeogenesis. These are different supplies: glycogenolysis draws on a finite glycogen reserve, whereas gluconeogenesis makes glucose from other substrates and depends on their availability. Longer fasting depletes the glycogen reserve; a stronger hormone signal cannot release material that is no longer there. [ref] [ref]
Do not copy the liver pathway into every target of insulin. Skeletal muscle uses its own glycogen reserve locally; its glucose uptake and the liver's glucose output are different flows. Nor is direct glucagon-stimulated lipolysis in human adipose tissue as firmly established as its action in the liver. Glucagon action depends on the tissue, other hormones, and available substrates. [ref]
There is a useful surprise inside the pancreatic islets: local glucagon can support insulin release from neighboring beta cells. The islet perifusion experiment distinguishes that interaction from glucagon's action on the liver. Thus the two hormones can oppose each other's effects on blood glucose while cooperating locally. Delta cells supply another local brake through somatostatin. [ref] [ref]
Intraislet glucagon signaling is critical for maintaining glucose homeostasis by Lu Zhu and others tested whether local glucagon supports insulin release. For human pancreatic islets, a computer-controlled flow system delivered a buffer solution at through a chamber holding 500 pancreatic islets on a nylon filter at . A fraction collector sampled the outgoing fluid. With an amino acid mixture present, the experiment changed glucose from to and compared GLP-1 receptor blockade with fluid lacking the blocker. The readout was released insulin and glucagon: blockade reduced glucose-stimulated insulin release without significantly changing glucagon release. [ref]
Complementary mouse experiments suppressed alpha cell activity using an engineered G protein-coupled receptor. ELISA assays of minute-by-minute effluent samples measured insulin and glucagon concentrations, providing the hormone release readout. Drug-treated control pancreatic islets lacking that engineered receptor checked for drug effects; adding glucagon restored insulin release in the suppressed preparation. Together, blockade and rescue support local signal transduction from alpha cells to beta cells. Isolated pancreatic islets omit intact circulation and nervous input; the human preparation came from five donors, and blocker specificity and donor variation limit generalization. A chamber response does not directly measure whole-body blood glucose control. [ref]
Articles by others on the same topic
There are currently no matching articles.