The investigation, prevention and treatment of human disease and injury. Clinical observations connect an individual’s condition with biological explanations and evidence about possible interventions; naming a disease and establishing its cause are distinct tasks.
The initial table of content was limited to the first level because it is larger than 1000 articles. There are 1509 articles in total. Expand a branch to load its children.
Classification of a presentation using specified diagnostic criteria. A diagnosis groups observed features; it does not, by itself, identify the causal processes maintaining a particular person's difficulties.
Arterial blood gas analysis applies blood gas analysis to a sample taken from an artery, providing a time-specific observation of systemic arterial gas tensions and acid-base state. Arterial oxygen partial pressure concerns oxygen tension, while arterial carbon-dioxide partial pressure and pH provide different information. The arterial qualifier is a sampling condition, not merely a label attached to any blood result.[ref]
Arterial Blood Gas (ABG) Test by MedlinePlus. What is an arterial blood gas test? measured quantities
The measurement chain includes obtaining an identified sample, preserving its gas composition and analyzing it with a checked instrument. Air contamination, fluid contamination and analysis delay can change the specimen after it leaves the circulation. A reproducible analyzer reading cannot repair a specimen that no longer represents the intended physiological state.[ref]
Equal oxygen tension need not mean equal arterial oxygen content. An original illustrative carrier model writeswhere is hemoglobin concentration, its oxygen-bound fraction and the carrier capacity per gram. Choose mL/g, mL/(dL·mmHg), and mmHg. Samples with and g/dL then contain about 20.00 and 10.15 mL O/dL, respectively. They have identical stipulated tension and saturation but very different oxygen content. The constants define the illustration; these are not patient results or diagnostic thresholds.
Interpretation also depends on the conditions when the sample was obtained. Inspired oxygen fraction, ventilator settings when applicable and sampling time help distinguish a changed respiratory state from a changed measurement condition. A later pulse oximetry reading is neither a simultaneous sample nor a measurement of carbon-dioxide tension.
Arterial blood gas analysis supplies evidence about gas transport and acid-base balance, but no individual number alone identifies the entire cause of an abnormal result. Measured co-oximetry and calculated oxygen saturation should also be distinguished when unusual hemoglobin species matter.[ref]
Pulse oximetry estimates arterial oxygen saturation noninvasively from wavelength-dependent optical signals that vary with the arterial pulse. A typical sensor combines red and infrared light-emitting diodes with a photodetector. The pulsatile component helps distinguish changing arterial blood contribution from relatively steady tissue and blood contributions; it is not a direct measurement of arterial oxygen partial pressure.
A primary instrument-design note implements 660 nm and 940 nm illumination, a shared photodetector and alternating channel acquisition. It separates pulsatile and steady components before estimating saturation.[ref]
Pulse Oximeter Fundamentals and Design by Santiago Lopez. Sections 2.2 and 3.1.2, printed pp. 3–5 and 7, optical channels and acquisition
These wavelengths and electronics describe that implementation rather than every possible sensor.Writing pulsatile and steady signal magnitudes as AC and DC, a common normalized optical quantity isFor original channel values AC, DC, AC and DC, this ratio is 0.5. Halving both red-channel magnitudes leaves the ratio unchanged. This illustrates intensity normalization; it does not determine a saturation without a validated relation between and saturation.
That relation is experimentally checked against an independent reference. The FDA's technical guidance describes comparing oximeter readings with simultaneous co-oximetry of arterial samples during controlled inspired-oxygen changes in volunteers, and reporting an accuracy statistic.[ref]
Pulse Oximeters: Premarket Notification Submissions by the FDA. Clinical Performance, SpO2 Accuracy: reference arterial sampling, inspired mixtures and paired readings
Such comparisons test the whole sensor–algorithm measurement chain, rather than only the arithmetic of a two-channel ratio.One summary is the root mean square differenceFor invented paired errors percentage points, percentage points even though mean error is zero. A small mean bias does not guarantee small individual errors.
Motion, weak pulsatile signals and additional absorbing hemoglobin species can invalidate assumptions behind a simple estimate. Pulse oximetry does not measure pH, carbon-dioxide tension or hemoglobin concentration. A stable displayed percentage therefore cannot establish every aspect of ventilation, oxygen content or gas exchange.
Palpation is examination by touch with the hands or fingers. It uses physical contact to assess features such as an organ's apparent size, position, consistency and tenderness. The observed feature and the resulting clinical diagnosis are separate: feeling a moving or resistant region does not by itself identify the complete underlying anatomy or disease.[ref]
The force applied during palpation is part of the measurement. In an original simplified indentation example, suppose a probe produces of displacement under a load. The secant stiffness for that observation isA second specimen requiring at the same displacement has twice this apparent stiffness. That ratio is not automatically a ratio of intrinsic elastic modulus values: contact geometry, specimen thickness, support and deformation rate can alter the force-displacement curve. Touch supplies a mechanical observation whose interpretation requires an appropriate model.
A clinical measurement study makes the distinction concrete. S. D. Eilen and colleagues compared precordial palpation with two-dimensional echocardiography in 41 patients. They compared the location and palpable diameter of the apical impulse with left ventricle end-diastolic volume. A lateral impulse location was sensitive but not specific for enlargement. Within the reported subgroup without ventricular hypertrophy, an impulse diameter above in the left-lateral position had reported diagnostic sensitivity and diagnostic specificity . Those are results for that study's condition and subgroup, rather than universal performance figures for touch.[ref]
Accuracy of precordial palpation for detecting increased left ventricular volume by S. D. Eilen and others. Abstract, Annals of Internal Medicine99 (1983), pp.628–630: cohort, location result and subgroup diameter result
A small probability example explains why both attributes matter. In a stipulated set with 20 enlarged and 80 non-enlarged hearts, a rule detecting 18 enlarged hearts but also flagging 24 non-enlarged hearts has diagnostic sensitivity and diagnostic specificity . Only of its positive results identify enlargement. These invented counts are not a reconstruction of the 41-patient study. They show why a palpable feature must be tested against an independent reference and interpreted with the population being examined.
Repeating a specified observation can assess reproducibility, while comparison with echocardiography assesses a different question: correspondence with the chosen anatomical reference. Holding body position and observation method consistent helps distinguish those sources of variation. A reliable description of what was felt is necessary evidence, but reproducibility alone does not establish the causal explanation.
Dysphagia means difficulty swallowing. It can involve preparation and transfer of material in the mouth, passage through the pharynx or movement down the oesophagus. These stages require coordinated muscle activity, sensation and neural control. Dysphagia names a functional difficulty rather than one unique disease or anatomical lesion. [ref]
Dysphagia by NIDCD. Fact sheet, What is dysphagia?, How do we swallow? and How does dysphagia occur?
Swallowing also protects the airway: food transport and temporary closure of the breathing passage must be coordinated. A delay in initiating the response and a mechanical obstruction can both disrupt swallowing through different mechanisms. Difficulty moving a bolus, pain during swallowing and entry into the airway are related observations but should not be treated as identical definitions.
A reference range is an interval derived from measurements in a specified reference population under specified analytical conditions. It gives context for a laboratory result; it is not automatically a boundary separating disease from health. Different methods, ages and reference populations can lead to different intervals. [ref]
How to Understand Your Lab Results by MedlinePlus. Reference ranges: laboratory differences, healthy people outside the interval and illness within it
For an illustrative central 95% interval, about 5% of measurements from the defining population lie outside by construction. If 20 independent tests each have a 5% outside probability, the probability of at least one outside result is . Independence is an assumption, but the calculation shows why many tests increase incidental flags. A clinical decision threshold can instead be chosen for a particular diagnostic or treatment purpose.
Population conditioning of ventricular reference ranges describes how the comparison interval for a ventricular measurement depends on the population and measurement conditions used to define it. A reference interval for a specified age, body size and imaging protocol is a different statistical object from an interval pooled across an arbitrary mixture of groups.
Let be a ventricular measurement and the recorded conditioning variables. A conditional central interval iswhere is a quantile. It describes a reference distribution under those conditions; it is not automatically a disease-decision boundary or a confidence interval for a patient's true value.
A primary cardiac-MRI study used 120 healthy participants, 60 men and 60 women aged 20–80, with steady-state free-precession cine imaging and three-dimensional right-ventricular modelling. Age, body surface area and sex predicted several measurements; some age associations remained after size normalization.[ref]
Reference right ventricular systolic and diastolic function normalized to age, gender and body surface area from steady-state free precession cardiovascular magnetic resonance by Alicia M. Maceira and others. Abstract, Methods and results and Conclusion
Dividing a volume by body surface area therefore need not remove every population association.An original example separates conditioning from pooling. Suppose hypothetical groups have volume distributions and in millilitres. Their central normal intervals are approximately – and –. A value is three standard deviations above the first group's mean but one below the second's. The groups are mathematical examples, not assigned clinical categories or published thresholds.
For a population mixture, . Its quantiles depend on the mixing proportions and generally are not averages of group quantiles. Changing the sampled proportions can change the pooled reference interval even if every within-group distribution stays fixed.
A transferable reference description therefore states participant selection, conditioning variables, acquisition method and segmentation conventions. Associations with recorded categories do not by themselves identify causal biological mechanisms. Interpretation additionally needs measurement uncertainty and the clinical question; membership outside a reference interval alone does not establish a diagnosis.
A core needle biopsy removes a small cylinder of biological tissue through a hollow needle for examination, commonly by microscopy. Retaining a piece of tissue permits assessment of cellular arrangement as well as individual cells. It differs from merely imaging the region or sampling dissolved substances in blood. The specimen supplies evidence from the sampled location; its interpretation also depends on sampling adequacy and the surrounding clinical question. [ref]
A liver function test measures selected substances in blood to investigate aspects of liver activity or injury. Common panels include albumin, bilirubin and enzymes associated with liver cells.
The components reflect different processes: protein production, handling of breakdown products and release of enzymes need not change together. Consequently the panel's name does not make every component a direct measurement of one overall liver function. The pattern and its clinical context contribute to clinical diagnosis; an abnormal value alone does not identify a unique disease.[ref]
Liver Function Tests by MedlinePlus. What are liver function tests?: component list and the distinction between impaired function, injury and diagnosis
A Wood's lamp supplies ultraviolet radiation for examining skin, making some differences in fluorescence or pigmentation easier to observe. Emitted visible light under illumination and ordinary surface appearance are different kinds of optical evidence. Some organisms or substances fluoresce while others do not, and surface materials can also contribute a signal. The observation therefore supplements clinical diagnosis rather than identifying every infection from color alone. [ref]
Wood lamp examination by MedlinePlus. Medical Encyclopedia: ultraviolet illumination, clinical uses and interfering materials
A heart murmur is an additional or prolonged sound associated with blood flow through the heart or nearby vessels, heard during auscultation. It differs from the usual brief heart sounds associated with valve closure. Some murmurs accompany structural or flow abnormalities, while others occur without significant structural disease. The sound is an observation contributing to clinical diagnosis, rather than a diagnosis uniquely identifying its cause. [ref]
A neurological sign is an observed finding about the function of the nervous system, such as an altered reflex, asymmetrical movement or a sensory deficit. It differs from a symptom, which is an experience reported by the person. A neurological examination combines several observations because one finding can have several explanations. The pattern and its context help distinguish a possible mechanism or location of dysfunction. [ref]
Neurological Exam by MedlinePlus. What happens during a neurological exam?: mental status, sensory, motor and reflex examination
Echocardiography uses ultrasonography to form moving images of the heart. Returning sound waves reveal the dimensions and motion of its chambers and heart valves, making structure and pumping visible during the same examination.
In the common transthoracic approach, an acoustic transducer transmits pulses through the chest and receives reflected signals. A computer reconstructs their spatial and temporal pattern into images. The resulting measurements contribute to clinical diagnosis alongside the clinical history and other observations; an image and its interpretation are distinct stages of the assessment.[ref]
Echocardiography by MedlinePlus. What is echocardiography?: moving images, structures assessed and the transthoracic transducer
Doppler echocardiography combines echocardiography with Doppler ultrasound to examine motion, particularly blood flow, in and around the heart. The image locates anatomical structures, while frequency shifts in returning ultrasound provide information about motion along the beam. It supplies a velocity measurement rather than a direct measurement of cardiac output.
For a moving scatterer with speed , beam-to-flow angle , transmitted frequency and sound speed , the leading approximation isThe two-way factor arises because the outgoing and returning wave both interact with the moving scatterer. For stipulated , , and , the shift is about . At the same flow gives half that shift. Interpreting the latter as perfectly aligned flow would underestimate the speed by a factor of two.
Pulsed-wave Doppler echocardiography uses timing to select a sampling region, whereas continuous-wave Doppler echocardiography receives signals continuously along the beam. The acquired velocity spectrum and the selected anatomical region must therefore be interpreted together. A moving tissue signal and a blood-flow signal are different observations even if both produce a Doppler effect.
A motivating primary validation by Halfdan Ihlen and colleagues compared Doppler-derived cardiac output with independent thermodilution and Fick measurements. The protocol included changes in flow during dobutamine infusion, testing correspondence over changing conditions rather than only one resting observation.[ref]
Determination of cardiac output by Doppler echocardiography by Halfdan Ihlen and others. Abstract: ten thermodilution comparisons and eleven Fick-method comparisons
Turning a velocity record into transported volume additionally requires an appropriate flow area and representative velocity distribution. The velocity-time integral makes that connection explicit. A large peak velocity alone neither determines the volume moved per beat nor identifies a unique clinical diagnosis.
Color Doppler overlays spatially localized estimates of motion on an ultrasound image. In blood-flow imaging, the estimated quantity is related to the Doppler ultrasound shift of echoes from moving red blood cells. The color scale encodes motion relative to the beam, not the blood's oxygen content. The displayed legend and sign convention must be read with the image.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. General Principles, printed p. 167, multiple gates and color velocity estimates
An important implementation estimates the phase change between repeated echoes using autocorrelation. Chihiro Kasai and coauthors demonstrated an autocorrelator combined with pulsed acquisition, testing scanners with phantoms as well as examining hearts. This made many localized estimates available fast enough for a changing two-dimensional image; it did not make each colored pixel an independent direct measurement of transported blood volume.[ref]
Real-Time Two-Dimensional Blood Flow Imaging Using an Autocorrelation Technique by Chihiro Kasai and others. Abstract and Sections II–III, mean Doppler frequency, system and phantom experiments
For an original single-frequency example, let successive complex echo samples be . Thenwhere is the Doppler ultrasound frequency shift and the pulse repetition frequency. The measured phase is unchanged when increases by any integer multiple of . This is aliasing even for a noiseless signal.
With Hz and transmitted frequency MHz, assume speed of sound m/s and motion parallel to the beam. True velocity 0.80 m/s gives Hz. Its principal sampled value is approximately Hz, corresponding to displayed beam velocity m/s under the same conversion. A color sign change can therefore occur without physical reversal of fluid flow.
The example isolates sampling. Mixed moving scatterers, finite spatial resolution and signal processing add further limitations. A color image is useful for locating a jet or a changing flow pattern, while a stroke volume requires an appropriate spatial and temporal integration of velocity, not the apparent size or brightness of a colored patch.
Continuous-wave Doppler echocardiography measures the Doppler frequency distribution of continuously transmitted and received ultrasound through the heart. It can record high flow velocities without the pulse-repetition-frequency aliasing limit of pulsed-wave Doppler echocardiography, but it does not select one depth along the beam. Signals from different contributing locations can overlap.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. General Principles, printed p.167; CW Doppler, p.169
For an aligned flow at speed , the leading Doppler ultrasound relation isWith stipulated transmitted frequency , sound speed and , the shift is approximately . A pulsed measurement with pulse repetition frequency would have a Doppler Nyquist frequency of only . Continuous-wave acquisition avoids that particular pulse-rate restriction. Its receiving electronics and digital sampling still have finite bandwidth; continuous transmission does not imply unlimited measurable frequency.
The price is Doppler range ambiguity. If a beam intersects two moving regions, a peak in the spectrum does not by itself label which depth produced it. The anatomical image, direction, timing and waveform context supply additional evidence. The outer spectral envelope describes the fastest detected motion along the beam, rather than a direct spatial average over one known vessel opening.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. CW Doppler, p.169, outer envelope and anatomical localization
This matters when estimating stroke volume. Multiplying a continuous-wave peak-velocity integral by an arbitrarily selected area can combine measurements from different sites or different parts of a velocity distribution. Flow-profile mismatch in Doppler stroke-volume estimation explains the separate requirement that the chosen velocity represent the area used in the volume calculation.
Doppler range ambiguity means that a measured Doppler ultrasound signal does not uniquely identify the depth of the scatterers producing it. In continuous-wave Doppler echocardiography, simultaneous transmission and reception collect motion signals along the beam without a unique pulse travel time. A high-speed spectral component therefore does not, by itself, label an anatomical site.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. General Principles, printed p. 167, and CW Doppler, p. 169
Repeated pulses can introduce a different range ambiguity. Let the pulse period be , with pulse repetition frequency . If reception is associated only with its delay within a pulse period, the possible round-trip travel times include . The corresponding depths arewhere is speed of sound. Identifying which transmitted pulse generated an echo requires additional information or a restriction on the possible depth.
For an original example, Hz gives microseconds. With m/s and observed within-period delay microseconds, possible depths are 7.7, 23.1 and 38.5 cm. Successive possibilities are separated by 15.4 cm. An anatomical restriction to depths below 15.4 cm would identify the first value; the echo timing alone would not.
Range ambiguity and aliasing of the Doppler ultrasound frequency are distinct. The first confuses position along the beam; the second confuses motion frequencies sampled at a given pulse rate. Increasing the pulse rate can improve the unaliased motion range while reducing unique depth coverage, producing the pulsed Doppler depth-velocity tradeoff. High-pulse-rate methods deliberately accept multiple possible sampling depths.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. General Principles, pp. 167–168, high-PRF modification
Anatomical imaging and acquisition geometry supply constraints; a plausible waveform is not itself a unique range label.Pulsed-wave Doppler echocardiography uses timed ultrasound transmissions and returns to measure motion within a selected sampling region of the heart or nearby vessels. An echo's round-trip delay provides depth information, so a time window can select a location. The resulting Doppler spectrum describes a finite sample volume rather than an exact point.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. General Principles, p.167; PW Doppler, pp.168–169
For sound speed and round-trip delay , the ideal depth is . Avoiding ambiguity between successive pulses in a simple single-depth system requires waiting at least before the next pulse. If is the pulse repetition frequency, this givesThe Doppler signal is sampled once per pulse, so unaliased shifts obey . For aligned flow and transmitted frequency ,This is the pulsed Doppler depth-velocity tradeoff in the stated idealization. With , and , the highest ideal pulse rate is and the corresponding speed limit is about . Doubling the depth halves both limits. Practical timing margins can reduce them further.
Aliasing is an ambiguity of the sampled signal, not proof that blood reverses direction. For example, sinusoidal Doppler shifts of and have identical complex samples at a pulse rate, because their frequencies differ by exactly one sampling rate. The example concerns the Doppler signal, not direct sampling of the megahertz acoustic carrier.
High-pulse-rate variants can trade unique range localization for a larger velocity range. Continuous-wave Doppler echocardiography instead transmits and receives continuously, accepting depth ambiguity. The choice of acquisition method therefore changes what information the measured spectrum contains.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. General Principles and high-PRF discussion, pp.167–168
The pulsed Doppler depth-velocity tradeoff is the restriction linking uniquely localized depth and unaliased beam velocity in a simple repeated-pulse Doppler ultrasound acquisition. Deeper echoes take longer to return, leaving fewer distinct pulse observations per second. Fewer observations reduce the unaliased Doppler ultrasound frequency interval.
For maximum depth , speed of sound and pulse repetition frequency , the ideal nonoverlapping timing restriction is . The Nyquist frequency is . Combining this with givesThe strict inequality excludes the ambiguous Nyquist endpoint. For beam-parallel motion, . At a right angle there is no first-order Doppler sensitivity to the motion; the apparent divergence of the formula does not provide unlimited useful velocity measurement.
For an original calculation, let m/s and MHz. A 15 cm depth allows at most approximately 5133 pulses/s in this idealization, with axial Nyquist speed about 0.791 m/s. At 30 cm these bounds fall to approximately 2567 pulses/s and 0.395 m/s. Doubling the transmitted frequency to 5 MHz halves the axial velocity limits at either depth.
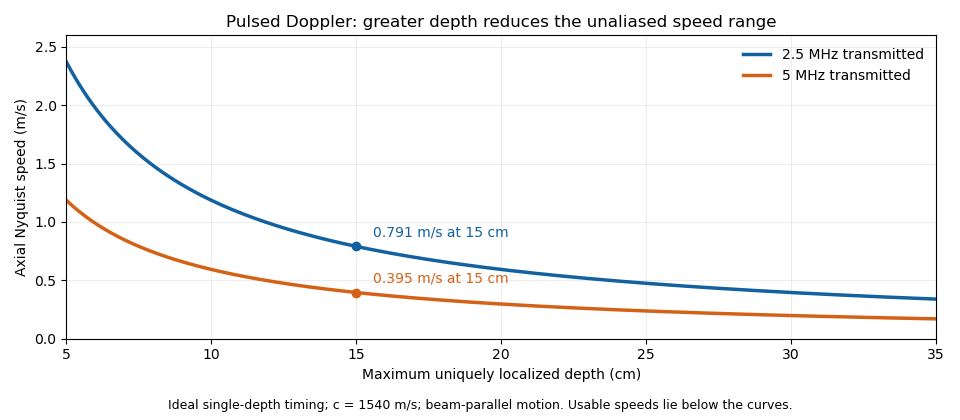
These are timing and sampling bounds, not a specification for a particular instrument. Pulse duration, scheduling and processing can lower the usable limit. Moving a spectral baseline changes the displayed signed interval but does not increase its total sampled-frequency width. Continuous-wave Doppler echocardiography avoids this pulse-rate restriction while sacrificing unique depth selection; high-pulse-rate acquisition instead accepts Doppler range ambiguity.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. General Principles, pp. 167–168, PW/CW and high-PRF distinctions
The acquisition choice determines which ambiguity remains.The velocity-time integral is the area under a velocity-versus-time curve over a specified interval:It has units of length. In Doppler echocardiography, a systolic flow-velocity trace can be integrated to estimate the distance associated with that measured waveform. The interval, sampling site and method of tracing the spectrum are part of the measurement.
The exact volume transported through an opening isFor constant area and a representative area-mean normal velocity , this reduces to . Approximating the left ventricular outflow tract as circular then giveswhere is the measured diameter, SV is stroke volume, HR is heart rate and CO is cardiac output. The primary Doppler study relates integrated velocity and anatomical area to cardiac output and compares the result with independent methods.[ref]
Determination of cardiac output by Doppler echocardiography by Halfdan Ihlen and others. Theory and Abstract: velocity integration, aortic size and method comparison
For stipulated and VTI , the estimated stroke volume is . At 75 beats per minute, cardiac output is approximately . A triangular waveform with peak and duration has that same integral. A trapezoidal waveform with the same peak and duration, but 0.10-second rise and fall, has integral instead.
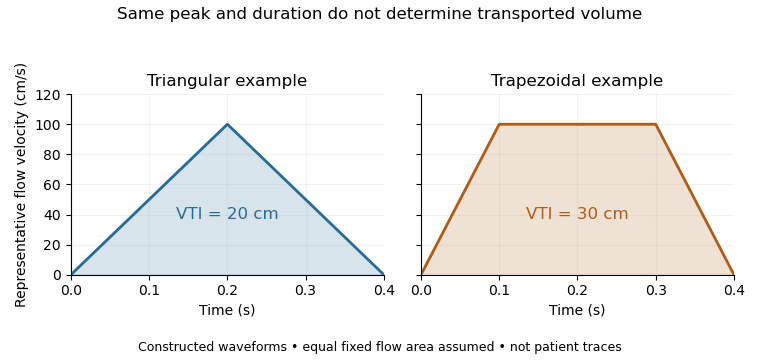
Equal peak flow velocities with different velocity-time integrals
. Details. The calculation depends quadratically on diameter: a 5% diameter overestimate produces a 10.25% area overestimate at fixed VTI. Flow-profile mismatch in Doppler stroke-volume estimation is a different error: a peak spectral envelope need not equal the area-mean velocity required by the volume integral. A VTI is also not automatically the path length travelled by one identifiable blood cell, since a fixed sampling region can observe different cells over time.
Flow-profile mismatch in Doppler stroke-volume estimation occurs when the velocity used in a stroke volume calculation does not represent the spatial average over the measured opening. The exact instantaneous volumetric flow rate isfor fixed area . Consequently . Replacing by a centerline velocity or fastest spectral envelope requires an additional profile assumption. The ASE report distinguishes the modal part of a pulsed Doppler spectrum from the outer continuous-wave envelope representing the fastest detected cells.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. PW Doppler and CW Doppler, printed p.169
An original family of axisymmetric profiles makes the missing factor explicit. Within a circular opening of radius , supposeHere is the centerline velocity. Integrating concentric annuli givesThe Doppler profile correction factor is therefore for this stipulated family. A parabolic profile has ; a blunter profile has . Both have the same centerline velocity and vanish at the wall. These shapes are examples, not fitted cardiac profiles.
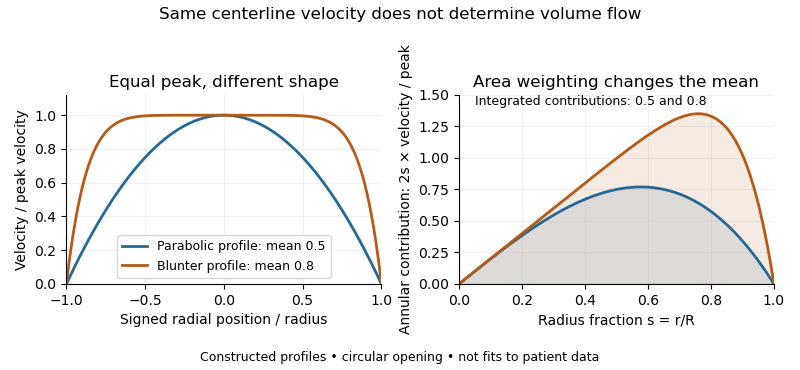
For and a centerline velocity-time integral of , uncorrected multiplication by gives . The two model profiles instead transport approximately and . Identical peak data can therefore support different transported volumes when the profile differs.
Real Doppler measurements also involve beam direction, sample-volume extent and signal processing. Their spectral envelope need not coincide with the literal centerline trace used in this example. The illustration isolates the averaging issue; it is not a universal factor-of-two correction for clinical measurements. The sampling site and anatomical area must be matched as well.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. PW Doppler, p.168, matched velocity and area locations
A Doppler profile correction factor converts a specified sampled velocity into the area-mean normal velocity needed to calculate volumetric flow rate. For a fixed opening of cross-sectional area and nonzero sampled trace , defineThe definition depends on both the spatial flow profile and what the instrument's sampled trace represents. A centerline trace, spectral mode and fastest detected envelope need not have the same correction. The primary ASE report distinguishes these spectral quantities and requires matched locations for velocity and area measurements.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. PW Doppler and CW Doppler, printed pp. 168–169
Even if each instantaneous correction is known, the appropriate correction for a whole velocity-time integral is generally not its ordinary time average. Provided the denominator is nonzero,This velocity-weighted Doppler profile correction gives greater influence to intervals carrying more of the sampled velocity-time integral.
In an original two-interval calculation, each interval lasts one second. Let sampled velocities be 10 and 30 cm/s and instantaneous corrections 0.5 and 1.0. The sampled velocity-time integral is 40 cm, while its corrected counterpart is cm. Thus , whereas the ordinary average correction is 0.75. For , the latter would predict 30 mL instead of the model's 35 mL.
When the sampled velocity is nonnegative, this is a weighted mean and lies between the instantaneous corrections. Reversing fluid flow can create cancellation in the denominator, so that conclusion need not hold. A factor measured in a steady tube also cannot be assigned to a changing cardiac profile without evidence. The calculation explains an averaging requirement; it supplies no universal clinical correction.
A velocity-weighted Doppler profile correction converts an integrated sampled velocity into an integrated area-mean velocity by weighting each instantaneous correction according to the sampled velocity at that time. For a fixed opening of cross-sectional area , suppose its area-mean normal velocity is . Thenprovided the denominator is nonzero. Applying the time average of to a velocity-time integral generally answers a different question.
The error has an exact covariance form. Define and time covariance . ThenConsequently an unweighted correction is exact if that covariance vanishes, even when the correction varies in time. Its failure is about how profile changes align with transport, not merely whether either trace varies.
In an original two-second example, equal one-second intervals have sampled velocities 10 and 40 cm/s and corrections 1.0 and 0.5. The unweighted mean correction is 0.75, but . With , actual modeled transport is 60 mL; unweighted correction predicts 75 mL, a 25% overestimate. Here time covariance is cm/s and mean sampled velocity is 25 cm/s, recovering .
If is nonnegative, normalized velocity weights are nonnegative and lies between the instantaneous corrections. For reversing fluid flow, the denominator can instead approach zero through cancellation. Forward and reverse transported volumes can then be more informative than a single unstable ratio. If opening area changes, the integral must also retain ; this fixed-area correction does not remove that additional dependence.
The primary Doppler report requires appropriate matching of sampled velocity and anatomical area and distinguishes modal spectral velocities from the fastest envelope.[ref]
Recommendations for Quantification of Doppler Echocardiography by Miguel A. Quiñones and others. PW Doppler and CW Doppler, printed pp. 168–169
The covariance calculation is an original integration identity, not a universal clinical profile correction.Endoscopy examines an internal space using an instrument that carries illumination and a viewing system into that space. A flexible instrument can transmit images from the digestive tract, while other forms examine different anatomical regions. Direct visualization and a biopsy answer different questions: a visible change describes appearance, whereas a tissue sample can support microscopy or molecular analysis. Some examinations combine both kinds of evidence. [ref]
A pregnancy test detects or measures human chorionic gonadotropin in urine or blood. The placenta produces this hormone after implantation, giving the measurement its biological connection to pregnancy.
A qualitative result applies a detection rule, while a quantitative blood test estimates the hormone level. The sampling time and the test's detection capability therefore affect what a negative result can establish. Detection of a biochemical signal is one observation within clinical diagnosis, rather than a complete description of the pregnancy's development.[ref]
Pregnancy Test by MedlinePlus. What is a pregnancy test?: hCG production, specimens and qualitative versus quantitative tests
A blood test measures a property of a blood sample. Different tests answer different questions: a blood count quantifies cellular components, whereas a liver function test measures selected substances associated with the liver.
A result requires a named measured quantity, units and an appropriate reference interval. Changes in cell counts and changes in a dissolved substance are different observations, even when both come from the same sample. Their contribution to clinical diagnosis depends on the question and accompanying findings.[ref][ref]
Liver Function Tests by MedlinePlus. What are liver function tests?: substances measured in a blood sample
A blood count quantifies one or more cell populations in a blood sample. Counts of red blood cells, white blood cells and platelets describe different populations, usually reported per unit volume rather than as a total number throughout the body.
A complete blood count combines several measurements, including cell counts and indices of cell size or composition. A differential count further separates types of white blood cells. These distinctions matter because two reported numbers may describe different components of the same specimen.[ref]
Complete Blood Count (CBC) by MedlinePlus. What is a Complete Blood Count?: counted populations, differential counts and cell indices
Clinical percussion produces vibrations by tapping the body surface and evaluates the resulting sound or movement. The response depends partly on the material and boundaries beneath the surface: air-rich, fluid-filled and solid regions can transmit different acoustic patterns. Percussion is therefore an indirect physical measurement used alongside other observations. A sound difference alone does not uniquely identify the underlying disease. [ref]
Auscultation listens to sounds generated within the body, commonly with a stethoscope. Cardiac and respiratory activity produce different acoustic patterns that can supply information about timing and flow. Unlike percussion, the examiner usually listens to sounds generated by the body rather than producing the initial sound by tapping. The observation and the inference about its cause are separate steps in clinical diagnosis. [ref]
A stethoscope couples sounds at the body surface to a listener or recording system for auscultation. In an acoustic instrument, the chestpiece and air-filled tubing transmit sound waves toward the ears; electronic designs instead use a sensor and amplification. The instrument changes access to an acoustic signal, but interpreting the source still requires timing, anatomical context and comparison with other findings. [ref]
Radiology is the medical specialty that uses imaging to investigate disease and guide treatment. It encompasses interpretation of acquired images and procedures in which imaging guides an intervention. Its tools include radiography, computed tomography, magnetic resonance imaging and ultrasound; the specialty is not limited to techniques using ionizing radiation.[ref]
What does a radiologist do? by RadiologyInfo.org. Professional description of imaging methods and diagnostic/interventional roles.
The physical motivation is illustrated by Wilhelm Conrad Röntgen's experiments. An energized discharge tube enclosed in light-blocking paper caused a nearby fluorescent screen to glow. Materials between the tube and screen transmitted the new radiation differently; a hand showed darker bone shadows against fainter surrounding tissue. Photographic recording turned such transmission differences into persistent images.[ref]
On a New Kind of Rays by Wilhelm Conrad Röntgen. 1895 communication, English translation 1896; sections 1–2 and 14: screen, intervening objects and photographic shadow images.
An invented measurement example makes the contrast explicit: if identical incident signals of 1,000 counts give 500 and 100 transmitted counts along two paths, their transmissions are 50% and 10%. The measurement distinguishes paths, but does not by itself name a disease. Anatomy, projection geometry, technique and other evidence are needed for interpretation.
A radiologist connects such physical measurements to clinical questions. Interventional radiology additionally uses images to guide instruments or treatment. Image acquisition, interpretation and intervention are related activities, but each requires its own evidence and expertise.[ref]
What does a radiologist do? by RadiologyInfo.org. Physician interpretation and image-guided therapeutic procedures.
Coronary angiography images the coronary arteries using a contrast medium and X-rays. In conventional invasive coronary angiography, a catheter delivers contrast to the coronary circulation while the imaging system records the contrast-filled vessel paths. The contrast improves visibility of the blood-filled lumen against surrounding tissue.[ref]
Heart Tests by the National Heart, Lung, and Blood Institute. Coronary angiography subsection, contrast and X-ray images
The apparatus connects fluid delivery to imaging geometry. An X-ray source and detector record the contrast signal during its passage through the vessels; changing viewing angle changes how overlapping arterial segments project into the image. The result is primarily a description of the contrast-filled lumen. It is not a direct measurement of every feature of the arterial wall or of how much oxygen reaches the myocardium.
An original geometric example shows why one apparent width can be incomplete evidence. Suppose a local lumen has an elliptical area with diameters and . Its area ishalf that of a circular lumen. One viewing direction can nevertheless show the same projected width as that circle, while an orthogonal view shows . A projected width does not uniquely determine lumen area without a shape and viewing model. These chosen dimensions are not a diagnostic threshold.
Timing and motion matter too: a moving vessel and changing contrast concentration can alter the recorded signal. A geometric narrowing, a pressure difference and downstream blood delivery are related observations but are not interchangeable. A physiological assessment needs evidence beyond one static projection.
Coronary CT angiography uses a different acquisition geometry: many X-ray views are reconstructed into a volume, commonly after contrast administration through a peripheral vein. The NHLBI account distinguishes cardiac computed tomography from the catheter-based angiographic description.[ref]
Heart Tests by the National Heart, Lung, and Blood Institute. Cardiac CT scan and Coronary angiography subsections
Naming the method makes clear whether a claim concerns a projection sequence or a reconstructed three-dimensional image.Fluoroscopy produces a sequence of X-ray projection images displayed during an examination or procedure. An X-ray beam passes through the body and a detector records the transmitted pattern, allowing motion of anatomy, a catheter or an introduced contrast agent to be followed. This temporal information makes fluoroscopy useful in interventional radiology, where the position of an instrument must be checked as it moves.[ref]
Fluoroscopy by the US Food and Drug Administration. Description and Benefits/Risks: dynamic display, instrument/contrast tracking and catheter/stent applications.
A simple sampling example shows both the benefit and the limit. If a hypothetical system displays 15 distinct frames per second, successive frames are separated by seconds. An instrument moving at a constant travels about 2 mm between frames. The image sequence can therefore reveal movement that a single radiograph cannot, while still leaving motion between samples unobserved. These numbers describe an invented measurement, not a recommended operating setting.
Each projection also collapses depth: a needle and a target may overlap on the screen while remaining separated inside the body. Choosing another view or another imaging method can address that ambiguity. More frames alone do not restore the missing depth coordinate.
Because fluoroscopy uses ionizing X-rays, exposure duration and technique affect delivered radiation. Holding every other setting fixed while doubling the time doubles the accumulated exposure in a constant-rate model; actual procedures need their own dose measurements. The originating FDA description emphasizes that prolonged, complex image-guided procedures can deliver substantial doses.[ref]
Fluoroscopy by the US Food and Drug Administration. Benefits/Risks and Information for the imaging team.
A radiologic technologist is a healthcare professional who carries out medical imaging procedures and helps obtain images suitable for interpretation. Responsibilities include positioning the patient, operating imaging equipment, checking image quality and recording acquisition details. Depending on specialization, the equipment can use X-rays, computed tomography, magnetic resonance imaging or ultrasound. The professional role connects the physical measurement to a usable clinical image.[ref]
What does a Radiologic Technologist do? by RadiologyInfo.org. Operating Equipment and Patient Care, reviewed1June2026.
Consider a radiography examination intended to show an anatomical boundary. A technically sharp image can still be inadequate if positioning superimposes the structure on another one or excludes it from the recorded field. The radiologic technologist therefore needs both knowledge of anatomy and control of the acquisition geometry. In an X-ray examination, restricting the beam to the required region also helps limit unnecessary exposure and scattered radiation.[ref]
What does a Radiologic Technologist do? by RadiologyInfo.org. Patient Care and Radiation Safety: positioning, quality checks and beam adjustment.
Acquiring an image and deciding what its findings mean are related responsibilities within a team. The radiologist interprets the study in its clinical context; a radiologic technologist helps ensure that the acquired evidence can answer the intended question. For example, motion blur can conceal a small feature without establishing that the feature is absent. Recognizing an acquisition limitation prevents a technical defect from being mistaken for biological evidence. Specific professional titles and permitted duties depend on training and jurisdiction.
Interventional radiology uses medical imaging to guide instruments into the body for diagnosis or treatment. A biopsy can obtain material for diagnosis; a catheter can provide access for a therapeutic procedure. Guidance may use fluoroscopy, ultrasound, computed tomography or magnetic resonance imaging, depending on the instrument, target and procedure.[ref]
Professions in Interventional Radiology by RadiologyInfo.org. Interventional Radiologist: imaging modalities, needles/catheters and diagnostic/therapeutic procedures.
The central measurement problem is localization. In an image-guided biopsy, seeing a suspicious region and seeing a needle separately is insufficient: the operator needs evidence that the sampling part of the needle reaches the intended region. A single X-ray projection collapses depth, so two objects can overlap on the image while remaining separated in the body. Choosing imaging views and following instrument motion addresses that geometric uncertainty. This explains why image guidance is more than taking a picture before an intervention.
An early therapeutic motivation was to use the access already provided by arterial catheters to treat obstructed vessels. Charles T. Dotter and Melvin P. Judkins's 1965 report described a percutaneous transluminal approach to arterial obstruction. Its developmental discussion connected contrast examinations and observed catheter pathways with the possibility of opening a passage through an obstructed region.[ref]
Percutaneous Transluminal Treatment of Arteriosclerotic Obstruction by Charles T. Dotter and Melvin P. Judkins. Abstract and Developmental Background, Figures1–2.
The example connects anatomical imaging to mechanical action: identifying a narrowed path and changing that path are different tasks, but the same image-guided access can support both. The historical report motivates the method; it is not a procedure-selection rule for an individual patient.
A radiologist is a physician specializing in diagnosis and treatment using medical imaging. The role includes choosing or advising on suitable imaging methods, interpreting measurements in anatomical and clinical context, and communicating their significance. Some radiologists also perform procedures under imaging guidance through interventional radiology.[ref]
What does a radiologist do? by RadiologyInfo.org. Professional-society account of physician interpretation, collaboration and minimally invasive procedures.
The distinction from image acquisition matters. A radiologic technologist often operates the acquisition equipment, while a radiologist interprets the resulting images and relates them to the question being investigated. The work is collaborative; neither the instrument's output nor a single visual feature automatically supplies a diagnosis.[ref]
What does a radiologist do? by RadiologyInfo.org. Your Radiologist and the description of the healthcare team.
A scientific example is phase-encoded imaging of cerebrospinal fluid. D. R. Enzmann and collaborators used a sequence synchronized to the cardiac cycle to distinguish motion in different fluid spaces. Interpretation required more than recognizing their outlines: opposite flow directions and different timing provided information about fluid dynamics.[ref]
This illustrates the role's technical content: understand which physical quantity an image encodes, separate acquisition artifacts from biological structure or motion, and state what the evidence supports. A bright pixel can have different meanings in different imaging sequences.
Melvin P. Judkins was a radiologist who developed preshaped catheters and a percutaneous transfemoral method for selective coronary angiography. His work connected catheter geometry, vascular anatomy and X-ray recording: the instrument had to reach a particular arterial opening, while the imaging system had to record the contrast-filled vessels.[ref]
https://www.scai.org/melvin-p-judkins-md-1922-85. SCAI professional-society account: preshaped Judkins catheters and selective coronary technique
His 1967 report Selective Coronary Arteriography: Part I: A Percutaneous Transfemoral Technic by Melvin P. Judkins described 100 consecutive patients examined for suspected coronary disease. Both coronary arteries were selectively catheterized from femoral access, and contrast injections were recorded by direct serial radiography and cine imaging. The methods describe forming catheter shapes over preformed bending wires, showing that the instrument's geometry was an engineered part of the measurement rather than an incidental tube.[ref]
Selective Coronary Arteriography: Part I: A Percutaneous Transfemoral Technic by Melvin P. Judkins. Abstract, Material and Technic, including original catheter-shaping description.
For an illustrative contrast experiment, imagine comparing a broad injection upstream with a small injection at the opening of one branch. The latter changes where contrast first enters and can make the selected branch easier to distinguish. That qualitative comparison explains the word selective; it does not specify a safe injection protocol or claim equal performance in every anatomical arrangement.
Judkins also collaborated with Charles T. Dotter on transluminal treatment of arterial obstruction, linking diagnostic access to the possibility of treatment through a catheter.[ref]
Percutaneous Transluminal Treatment of Arteriosclerotic Obstruction by Charles T. Dotter and Melvin P. Judkins. Originating 1965 byline, abstract and developmental discussion.
His preshaped coronary instruments and the joint obstruction work are related contributions, but they address different immediate tasks: delineating a vessel and changing an obstructed passage.Charles T. Dotter was a radiologist whose work helped establish interventional radiology: using imaging-guided vascular access to treat disease as well as visualize it. His Oregon institution credits his 1964 percutaneous transluminal angioplasty with launching that approach. With Melvin P. Judkins, he reported the development of catheter-based treatment for arterial obstruction.[ref]
https://www.ohsu.edu/dotter-interventional-institute. OHSU, Dotter's legacy of innovation:1964 image-guided transluminal angioplasty
[ref]Percutaneous Transluminal Treatment of Arteriosclerotic Obstruction by Charles T. Dotter and Melvin P. Judkins. Radiology 84(1965),631–643, originating byline and abstract.
The motivating observation was mechanical as well as radiological. Their 1965 report discussed catheter pathways through or alongside obstructed arterial material and illustrated contrast visualization of such passages. An event that could complicate diagnostic catheterization suggested that a new flow path might also be deliberately useful. The report framed the approach as a treatment for obstruction, rather than merely a way to obtain a sharper radiograph.[ref]
Percutaneous Transluminal Treatment of Arteriosclerotic Obstruction by Charles T. Dotter and Melvin P. Judkins. Developmental Background and Figures 1–2; stated therapeutic purpose.
A separate idealized flow calculation explains why lumen size matters. For a long circular tube carrying steady laminar flow of a Newtonian fluid, with fixed pressure difference, length and viscosity, flow is proportional to the fourth power of the radius. Increasing the radius by a factor of two would increase this model's flow by . Real blood vessels are compliant, flow can be pulsatile and lesions have complicated shapes; the calculation is an explanatory limit, not an outcome predicted for a particular patient.
Dotter's contribution illustrates a scientific change of question: imaging can measure where a passage is obstructed, while an instrument introduced under imaging guidance can alter that passage. Demonstrating instrument passage, restoring flow and establishing durable clinical benefit are distinct evidential steps. The historical report motivates this sequence without making them equivalent.
N. J. Pelc is a coauthor with D. R. Enzmann of a 1991 study that used phase-contrast magnetic resonance imaging to measure cerebrospinal fluid motion through the cardiac cycle. The work illustrates how magnetic resonance imaging can provide a time-dependent physiological measurement rather than only an anatomical picture.[ref]
Normal flow patterns of intracranial and spinal cerebrospinal fluid defined with phase-contrast cine MR imaging by D. R. Enzmann and others. Radiology178,467–474(1991), originating byline and abstract.
The investigators studied ten healthy volunteers and four patients whose conventional magnetic-resonance images were normal. Peripheral cardiac gating divided the measurement into 16 flow-encoded images per cycle. The flow encoding distinguished opposite directions of cerebrospinal fluid motion, and measurements at several locations showed that the timing of the motion differed between the ventricular system and surrounding spaces.[ref]
Normal flow patterns of intracranial and spinal cerebrospinal fluid defined with phase-contrast cine MR imaging by D. R. Enzmann and others. Abstract: participant groups,16 cardiac phases, directional encoding and regional timing.
For an illustrative one-second cycle, 16 equally spaced phases would separate samples by seconds. The paper's number of cardiac phases therefore matters: an average over the entire cycle could hide changes of direction within it. Conversely, sixteen phases are a temporal sampling scheme, not evidence of sixteen independent subjects. This example explains the measurement design without assigning an unreported individual contribution to either coauthor.
D. R. Enzmann is the radiologist credited under that byline as first author of Normal flow patterns of intracranial and spinal cerebrospinal fluid defined with phase-contrast cine MR imaging by D. R. Enzmann and others. With N. J. Pelc, Enzmann reported measurements of moving cerebrospinal fluid, using magnetic resonance imaging to investigate physiology as well as anatomical appearance.[ref]
Normal flow patterns of intracranial and spinal cerebrospinal fluid defined with phase-contrast cine MR imaging by D. R. Enzmann and others. Radiology 178 (1991), 467–474; verified byline and abstract.
The study examined ten healthy volunteers and four patients whose conventional MR images were normal. Peripheral gating produced sixteen quantitative flow-encoded images over the cardiac cycle. Measurements distinguished the timing of fluid motion in ventricular and subarachnoid spaces, demonstrating why static anatomy alone does not describe pulsatile movement.[ref]
Normal flow patterns of intracranial and spinal cerebrospinal fluid defined with phase-contrast cine MR imaging by D. R. Enzmann and others. Abstract: participant groups, peripheral gating and regional flow timing.
The methodological contribution is an example of turning image contrast into a physiological measurement. Direction-sensitive signals and repeated sampling across a heartbeat distinguish oscillatory motion from a compartment that simply looks fluid-filled. The reported display convention assigned opposite intensities to opposite craniocaudal directions; that convention belongs to the acquisition and is not a universal rule for brightness in every MR image.
The initials are retained as verified in the original research record. The paper establishes authorship and the reported results; it does not separately document which apparatus component or analysis step each coauthor personally performed.
Emergency support of blood circulation and breathing during cardiac arrest. Chest compression supplies limited blood flow while other interventions address oxygenation and the cause of arrest; resuscitation is a process, not evidence that normal blood circulation has already returned.
Restriction of bodily movement by physical means. Its clinical indication and legal justification must be distinguished from authority for institutional admission.
An instrument or apparatus intended for medical investigation or treatment.
A medical device that holds an opening or cavity accessible for examination. Its shape depends on the site: a vaginal speculum and an ear speculum serve the same broad purpose through different designs.
Device that disperses a liquid into droplets. Reservoir concentration, emitted quantity and absorbed dose are different quantities.
Investigation of health and disease through measurements on biological samples. A result depends on sampling, analytical performance and biological context; a value outside a reference interval does not by itself establish one diagnosis.
Cultivation of microorganisms from urine. Growth can support investigation of urinary infection, but contamination, sampling method and clinical context affect interpretation of the organisms and quantities recovered.
Cultivation of microorganisms from blood. Recovery can provide evidence of bloodstream infection, while organisms introduced during sampling can produce contamination; identifying growth and determining its clinical meaning are separate tasks.
Treatment intended to increase urine output. Current guidance uses monitored diuretic therapy for acute heart failure; it is distinct from loss of blood through venesection. [ref]
Introduction of fluid into the lower intestine for a specified diagnostic or therapeutic purpose. Mechanical evacuation of selected faecal impaction differs from a systemic treatment of the underlying cause of constipation.[ref]
Constipation by the NHS. Complications of long-term constipation
The branch of medicine concerned with disorders of the ear, nose, throat and related head-and-neck structures. Its problems connect sensory function, breathing, swallowing and communication with local anatomy.
Inflammation of the larynx.
Inflammation of the pharynx.
Reduced ability to detect or interpret sound. Conductive impairment affects transmission through the outer or middle ear, while sensorineural hearing loss involves the inner ear or auditory neural pathway; mixed forms combine mechanisms.
Hearing loss arising from inner-ear sensory structures or auditory neural pathways. It differs from failure to conduct sound through the outer or middle ear, although both mechanisms can coexist.
An abnormally low concentration of calcium in blood. Total and ionized calcium are different measurements; changes in protein binding can alter total calcium without an equivalent change in its physiologically active fraction.
The branch of medicine concerned with the female reproductive system outside the direct management of pregnancy and childbirth. It connects symptoms such as abnormal bleeding with anatomical, endocrine and cellular explanations.
Menstrual blood loss that interferes with physical, social or emotional life. It is a clinical description with several possible causes, including uterine fibroids and ovulatory disturbances, rather than one pathological diagnosis.[ref]
Heavy menstrual bleeding by NICE. Definition and investigation
Examination of the uterine cavity with an optical instrument passed through the cervix. It provides direct visualization of the cavity’s surface and can guide investigation of focal lesions that a whole-organ measurement may miss.
A cancer arising in the lining of the uterus. It is distinct from a uterine smooth-muscle tumor or a cervical cancer, making the tissue of origin important to classification.
Presence of endometrial glands and stroma within the muscular wall of the uterus. It differs from endometriosis, in which endometrial-like tissue occurs outside the ordinary uterine lining at other sites.
A localized projection of endometrial tissue into the uterine cavity. It can contribute to abnormal bleeding, but a structural finding and the cause of a particular symptom still require clinical correlation.
A benign smooth muscle tumour of the uterus, also called a leiomyoma. Effects depend partly on location: a small cavity-distorting lesion can have different consequences from a larger outward-growing one.[ref]
A uterine fibroid attached by a stalk. The term describes its attachment, while submucosal or subserosal describes its relation to uterine layers; these descriptors can therefore apply to the same lesion.[ref]
A uterine fibroid growing toward or beyond the outer surface of the uterus. Its location makes pressure on surrounding structures more relevant than direct distortion of the uterine cavity.[ref]
A uterine fibroid contacting or projecting into the uterine cavity beneath the endometrial surface. Cavity distortion distinguishes this location from a purely outward-growing lesion.[ref]
Uterine Fibroids by Merck Manual Professional Edition. Anatomic locations and classification table
A uterine fibroid situated within the muscular wall of the uterus. The term locates the lesion anatomically; it does not alone specify symptoms or biological behavior.[ref]
Disturbance in the occurrence or timing of ovulation. Altered ovarian cycling can change menstrual bleeding patterns, connecting endocrine regulation with a symptom that is not necessarily caused by an anatomical lesion.
Inflammation of the cervix. Infection is one possible cause, but the anatomical diagnosis does not by itself identify an organism or a route of transmission.
Surgical removal of an ovarian cyst while attempting to preserve surrounding ovarian tissue. It differs from removal of the whole ovary, and the operative name alone does not identify the cyst’s pathology.
A hymenal membrane without an opening. It can obstruct outflow of menstrual material after puberty, connecting a congenital anatomical variant with later apparent absence of external menstruation.
A device placed in the vagina for a local mechanical purpose, commonly support of prolapsed pelvic organs. The word can also occur in older pharmaceutical usage, so an historical text’s intended meaning requires context.
Backward bending of the uterine body relative to the cervix. It describes the angle within the organ, whereas uterine retroversion describes the orientation of the uterus more broadly.
A backward orientation of the uterus within the pelvis. It is an anatomical position rather than a diagnosis of disease in itself and should be distinguished from uterine retroflexion.
Presence of endometrial-like tissue outside its usual uterine location, associated with an inflammatory response. Location and biological activity help explain symptoms; the amount visible and the severity of symptoms need not correspond directly.
Reduced ovarian activity before the usual age of menopause. Intermittent function can remain, making it different from assuming that every ovarian follicle is permanently absent.
Failure of ovulation during an ovarian cycle. Menstrual-like bleeding can still occur, so bleeding alone does not demonstrate that an oocyte was released.
Absence of menstruation; it describes a sign with physiological, endocrine and anatomical explanations, rather than one disease.
Absence of menstruation after periods were previously established. It describes a change in menstrual history whose explanations include pregnancy and disturbances of reproductive endocrine regulation.[ref]
Amenorrhea: Absence of Periods by ACOG. Primary and secondary amenorrhea
Failure of menstruation to begin by the age or developmental stage at which assessment is indicated. Anatomical outflow problems and endocrine or gonadal causes are different possible explanations.[ref]
Amenorrhea: Absence of Periods by ACOG. Primary and secondary amenorrhea
A feeling of impending loss of consciousness. The word should not automatically be substituted for a demonstrated episode of syncope.
Removal or sampling of tissue for examination, often by microscopy. A biopsy can establish features of the sampled area; its ability to represent a larger lesion depends on where and how the sample was obtained.
A biopsy of the skin. The depth and site of the sample determine which layers and processes are represented, so a surface sample and a full-thickness sample can answer different questions.
The branch of medicine concerned with inflammatory, autoimmune and other disorders of joints and connective tissues. Similar patterns of pain can arise through different mechanisms, making anatomical distribution and systemic findings important.
Historical umbrella for painful musculoskeletal disorders, including conditions now separated as acute rheumatic fever, rheumatoid arthritis and osteoarthritis. It is not a single modern pathological diagnosis.
An inflammatory arthritis associated with deposition of urate crystals in anatomical joints. Historical descriptions of podagra require interpretation rather than automatic assignment of every ancient patient to this modern category. [ref]
A crystalline urate deposit involved in the inflammatory mechanism of gout. A historical description of pain does not by itself demonstrate such deposits. [ref]
Gout by the NHS. Causes and diagnostic testing
Gout affecting the foot, particularly its big toe. The ancient word is retained in historical accounts of gout.
A deposit of urate crystals surrounded by a tissue reaction in gout. A tophus represents accumulated material and chronic local responses rather than merely the transient swelling of an acute attack.[ref]
Gouty Tophus by Weill Cornell Medicine. Diagnostic description
Articles were limited to the first 100 out of 1509 total.